Related Experiment Video
Updated: Oct 23, 2025
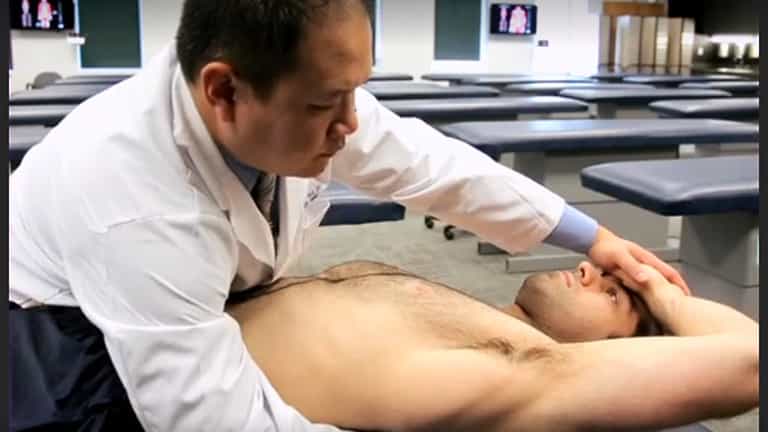

Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Low-dose oestrogen-progestin associated pulmonary infarction mimicking pneumonia and pleurisy
Kyoko Gocho1, Shinnosuke Kitazawa1, Shinya Matsushita1
1Department of Respiratory Medicine Saiseikai Yokohamashi Tobu Hospital Yokohama Japan.

A 28-year-old woman with a history of treatment with a low-dose oestrogen-progestin (LEP) formulation presented to our hospital due to right chest pain. She had just been discharged from another hospital for pneumonia and pleurisy which had improved with antibiotics. Contrast-enhanced computed tomography (CT) revealed bilateral pulmonary emboli corresponding to the peripheral consolidations. The pulmonary emboli indicated that the peripheral consolidation was due to pulmonary infarction (PI). No aetiological factors were identified except for the history of LEP therapy. Although the typical CT images of PI are consolidations in the peripheral area, these finding are non-specific for PI. This case of PI was misdiagnosed as infection because of response to antibiotics and similar CT findings. Therefore, careful evaluation of the patient history and clinical findings are imperative for accurate diagnosis. Venous thromboembolism can occur frequently around 3 months after the start of LEP treatment.
A 28-year-old woman with a history of treatment with a low-dose oestrogen-progestin (LEP) formulation presented to our hospital due to right chest pain. She had just been discharged from another hospital for pneumonia and pleurisy which had improved with antibiotics. Contrast-enhanced computed tomography (CT) revealed bilateral pulmonary emboli corresponding to the peripheral consolidations. The pulmonary emboli indicated that the peripheral consolidation was due to pulmonary infarction (PI). No aetiological factors were identified except for the history of LEP therapy. Although the typical CT images of PI are consolidations in the peripheral area, these finding are non-specific for PI. This case of PI was misdiagnosed as infection because of response to antibiotics and similar CT findings. Therefore, careful evaluation of the patient history and clinical findings are imperative for accurate diagnosis. Venous thromboembolism can occur frequently around 3 months after the start of LEP treatment.


Related Concept Videos
 01:29
Pneumonia II: Pathophysiology
 01:29
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations: