Related Experiment Video
Updated: Oct 21, 2025
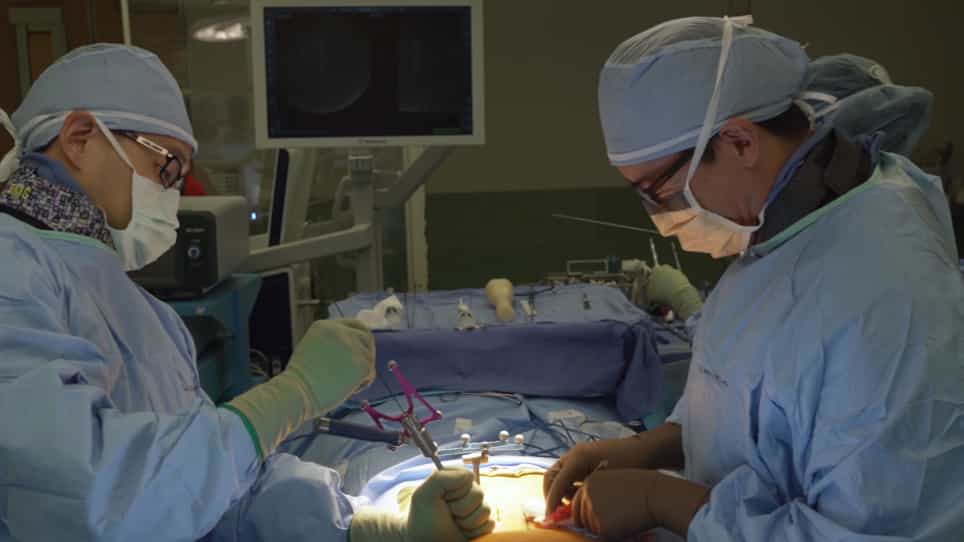
Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Freehand screw insertion technique without image guidance for the cortical bone trajectory screw in posterior lumbar

Objective:
Cortical bone trajectory (CBT) screw insertion using a freehand technique is considered less feasible than guided techniques, due to the lack of readily identifiable visual landmarks. However, in posterior lumbar interbody fusion (PLIF), after resection of the posterior anatomy, the pedicles themselves, into which implantation is performed, are palpable from the spinal canal and neural foramen. With the help of pedicle wall probing, the authors have placed CBT screws using a freehand technique without image guidance in PLIF. This technique has advantages of no radiation exposure and no requirement for expensive devices, but the disadvantage of reduced accuracy in screw placement. To address the problem of symptomatic breaches with this freehand technique, variables related to unacceptable screw positioning and need for revisions were investigated.
Methods:
From 2014 to 2020, 182 of 426 patients with single-level PLIF were enrolled according to the combined criteria of L4-5 level, excluding cases of revision and isthmic spondylolisthesis; using screws 5.5 mm in diameter; and operated by right-handed surgeons. We studied the number of misplaced screws found and replaced during initial surgeries. Using multiplanar reconstruction CT postoperatively, 692 screw positions on images were classified using previously reported grading criteria. Details of pedicle breaches requiring revisions were studied. We conducted a statistical analysis of the relationship between unacceptable (perforations > 2 mm) misplacements and four variables: level, laterality, spinal deformity, and experiences of surgeons.
Results:
Three screws in L4 and another in L5 were revised during initial surgeries. The total rate of unacceptable screws on CT examinations was 3.3%. Three screws in L4 and another in L5 breached inferomedial pedicle walls in grade 3 and required revisions. The revision rate was 2.2%. The percentage of unacceptable screws was 5.2% in L4 and 1.7% in L5 (p < 0.05), whereas other variables showed no significant differences.
Conclusions:
A freehand technique can be feasible for CBT screw insertion in PLIF, balancing the risks of 3.3% unacceptable misplacements and 2.2% revisions with the benefits of no radiation exposure and no need for expensive devices. Pedicle palpation in L4 is the key to safety, even though it requires deeper and more difficult probing. In the initial surgeries and revisions, 75% of revised screws were observed in L4, and unacceptable screw positions were more likely to be found in L4 than in L5.
More Related Videos
 12:25
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024