Related Experiment Video
Updated: Oct 21, 2025
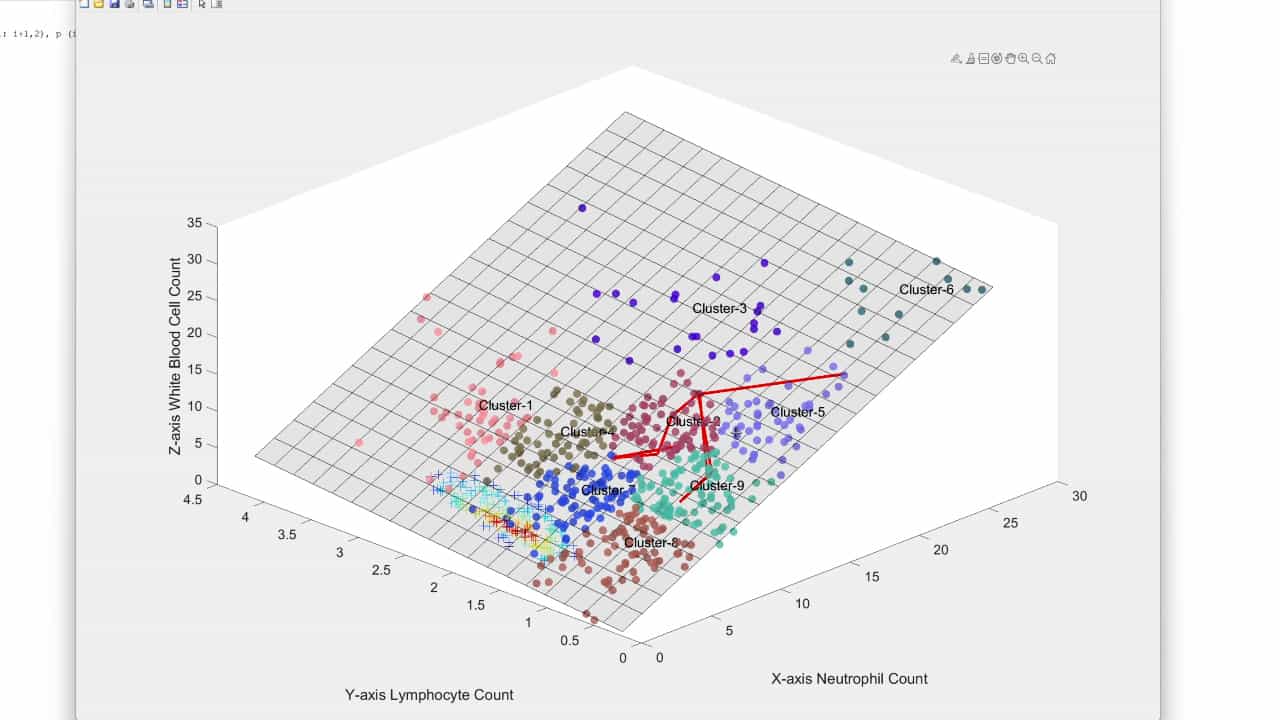

A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Data-driven clustering identifies features distinguishing multisystem inflammatory syndrome from acute COVID-19 in
Alon Geva1,2,3, Manish M Patel4,5, Margaret M Newhams1
1Department of Anesthesiology, Critical Care, and Pain Medicine, Boston Children's Hospital, Boston,1These authors contributed equally to this work.2A complete list of members and affiliations is provided in the Supplementary Appendix. MA, USA.

Insights
This study used data clustering to identify distinct patient groups, revealing that some children diagnosed with Multisystem Inflammatory Syndrome in Children (MIS-C) may actually have severe COVID-19 pneumonia.
Area of Science:
- Pediatric infectious diseases
- Critical care medicine
- Epidemiology
Background:
- Current consensus criteria for Multisystem Inflammatory Syndrome in Children (MIS-C) prioritize sensitivity, potentially including cases of acute COVID-19 pneumonia.
- Accurate differentiation between MIS-C and severe COVID-19 is crucial for appropriate patient management.
Purpose of the Study:
- To apply an unsupervised clustering approach to identify distinct phenotypes within hospitalized children with COVID-19-related illness.
- To evaluate the accuracy of clinical labels for MIS-C and identify potential misclassifications.
Main Methods:
- Unsupervised clustering was performed on data from 1,526 pediatric patients hospitalized with COVID-19-related illness.
- Clinical features and diagnostic labels were analyzed to identify distinct patient clusters.
- Recursive feature elimination was used to pinpoint characteristics differentiating potentially misclassified cases.
Main Results:
- Three distinct patient clusters emerged based on 46 clinical features.
- Cluster 1 (92% labeled MIS-C) predominantly comprised previously healthy children with cardiovascular/mucocutaneous involvement and negative SARS-CoV-2 PCR.
- Cluster 2 (27% labeled MIS-C) frequently had pre-existing conditions, respiratory involvement, positive PCR, and chest radiograph infiltrates, distinguishing them from Cluster 1.
- Cluster 3 represented younger, PCR-positive patients with less inflammation.
Conclusions:
- Data-driven clustering successfully identified a phenotype highly likely to be MIS-C.
- A separate cluster of patients, characterized by pulmonary infiltrates and positive PCR, was more likely to represent acute severe COVID-19 pneumonia.
- Clinician-labeled MIS-C cases within this latter group may represent misclassifications, suggesting a need to refine MIS-C diagnostic criteria.
Background:
Multisystem inflammatory syndrome in children (MIS-C) consensus criteria were designed for maximal sensitivity and therefore capture patients with acute COVID-19 pneumonia.
Methods:
We performed unsupervised clustering on data from 1,526 patients (684 labeled MIS-C by clinicians) <21 years old hospitalized with COVID-19-related illness admitted between 15 March 2020 and 31 December 2020. We compared prevalence of assigned MIS-C labels and clinical features among clusters, followed by recursive feature elimination to identify characteristics of potentially misclassified MIS-C-labeled patients.
Findings:
Of 94 clinical features tested, 46 were retained for clustering. Cluster 1 patients (N = 498; 92% labeled MIS-C) were mostly previously healthy (71%), with mean age 7·2 ± 0·4 years, predominant cardiovascular (77%) and/or mucocutaneous (82%) involvement, high inflammatory biomarkers, and mostly SARS-CoV-2 PCR negative (60%). Cluster 2 patients (N = 445; 27% labeled MIS-C) frequently had pre-existing conditions (79%, with 39% respiratory), were similarly 7·4 ± 2·1 years old, and commonly had chest radiograph infiltrates (79%) and positive PCR testing (90%). Cluster 3 patients (N = 583; 19% labeled MIS-C) were younger (2·8 ± 2·0 y), PCR positive (86%), with less inflammation. Radiographic findings of pulmonary infiltrates and positive SARS-CoV-2 PCR accurately distinguished cluster 2 MIS-C labeled patients from cluster 1 patients.
Interpretation:
Using a data driven, unsupervised approach, we identified features that cluster patients into a group with high likelihood of having MIS-C. Other features identified a cluster of patients more likely to have acute severe COVID-19 pulmonary disease, and patients in this cluster labeled by clinicians as MIS-C may be misclassified. These data driven phenotypes may help refine the diagnosis of MIS-C.
More Related Videos
 08:51
Author Spotlight: Integrated Multi-Omics Analysis for Unveiling Multicellular Immune Signatures in Clinical Heart Attack Cohorts
Published on: September 20, 2024
 08:44
Separation of Immune Cell Subpopulations in Peripheral Blood Samples from Children with Infectious Mononucleosis
Published on: September 7, 2022
Related Concept Videos
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include: