Related Experiment Video
Updated: Oct 21, 2025


Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
Quantification of airway conductance from noninvasive ventilatory drive in patients with sleep apnea
Thomas M Tolbert1, Ankit Parekh1, Scott A Sands2,3
1Division of Pulmonary, Critical Care, and Sleep Medicine, Icahn School of Medicine at Mount Sinai, New York, New York.

Abstract:
Upper airway conductance, the ratio of inspiratory airflow to inspiratory effort, quantifies the degree of airway obstruction in hypopneas observed in sleep apnea. We evaluated the ratio of ventilation to noninvasive ventilatory drive as a surrogate of conductance. Furthermore, we developed and tested a refinement of noninvasive drive to incorporate the interactions of inspiratory flow, pressure, and drive to better estimate conductance. Hypopneas were compiled from existing polysomnography studies with esophageal catheterization in 18 patients with known or suspected sleep apnea, totaling 1,517 hypopneas during NREM sleep. For each hypopnea, reference standard conductance was calculated as the ratio of peak inspiratory flow to esophageal pressure change during inspiration. Ventilatory drive was calculated using the algorithm developed by Terrill et al. and then mathematically modified according to the presence or absence of flow limitation to noninvasively estimate esophageal pressure. The ratio of ventilation to ventilatory drive and the ratio of peak inspiratory flow to estimated esophageal pressure were each compared with the reference standard for all hypopneas and for median values from individual patients. Hypopnea ventilation to drive ratios were of limited correlation with the reference standard (R2 = 0.17, individual hypopneas; R2 = 0.03, median patient values). Modification of drive to estimated pressure yielded estimated conductance, which strongly correlated with reference standard conductance (R2 = 0.49, individual hypopneas; R2 = 0.77, median patient values). We conclude that the severity of airway obstruction during hypopneas may be estimated from noninvasive drive by accounting for mechanical effects of flow on pressure. NEW & NOTEWORTHY Classification of hypopneas as obstructive (decreased upper airway conductance) or central (decreased inspiratory flow commensurate with decreased effort) is complicated by the requirement of invasive methods, such as esophageal manometry. Here, we demonstrate that using a few esophageal pressure measurements to account for the interactions between inspiratory flow, pressure, and noninvasive ventilatory drive allows estimation of upper airway conductance. Further studies may use these findings to quantify airway obstruction completely noninvasively.

Related Concept Videos
 01:22
Respiratory Volumes and Capacities
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:15
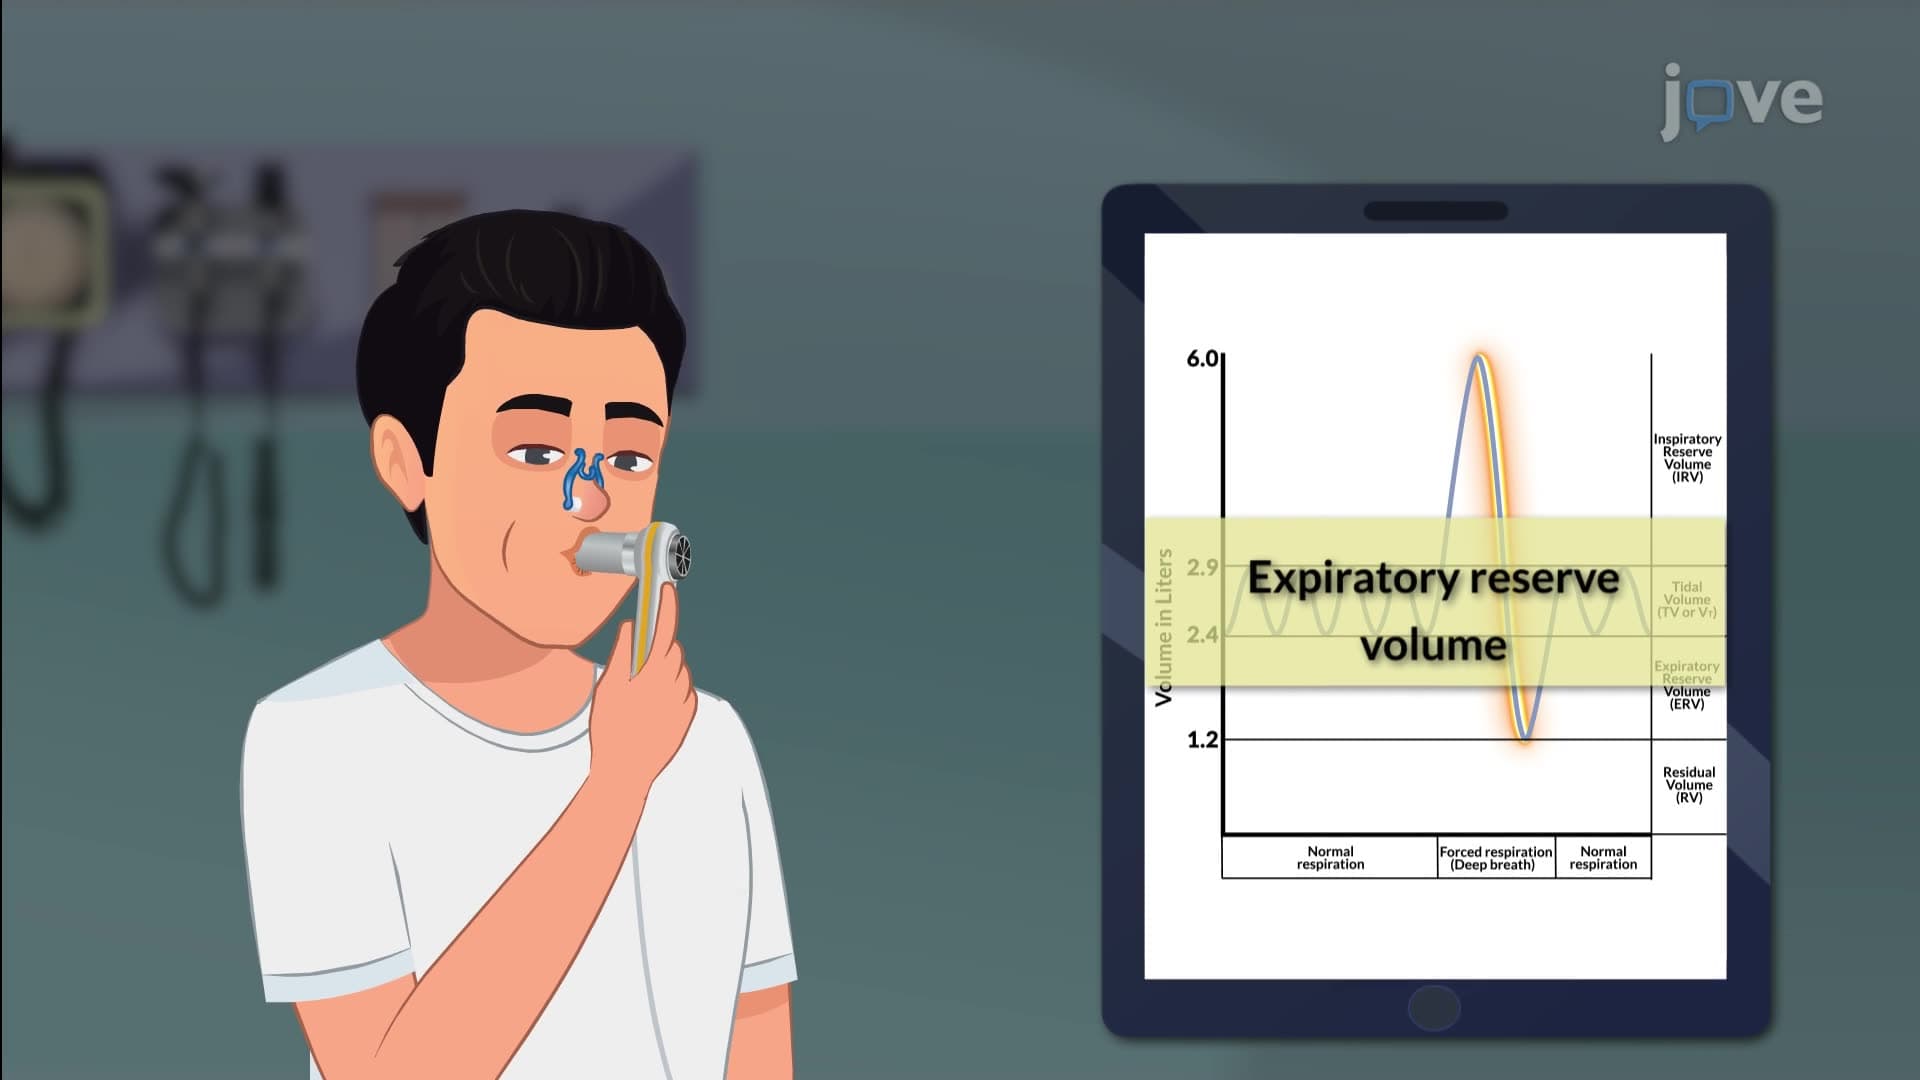
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: