Related Experiment Video
Updated: Oct 19, 2025


Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
Readmission for pleural space complications after chest wall injury: Who is at risk?
Annika B Kay1, David S Morris, Scott Gardner
1From the Division of Trauma Services and Surgical Critical Care, Intermountain Medical Center, Murray, Utah.

Background:
Little is known about patient characteristics predicting postdischarge pleural space complications (PDPSCs) after thoracic trauma. We sought to analyze the patient population who required unplanned hospital readmission for PDPSC.
Methods:
Retrospective review of adult patients admitted to a Level I Trauma Center with a chest Abbreviated Injury Scale (AIS) score of 2 or greater between January 2015 and August 2020. Those readmitted within 30 days of index hospitalization discharge for PDPSC were compared with those not readmitted. Demographics, injury characteristics, surgical procedures, imaging, and readmission data were retrieved.
Results:
Out of 17,192 trauma evaluations, 3,412 (19.8%) suffered a chest AIS score of 2 or greater injury and 155 experienced an unplanned 30-day hospital readmission. Of those, 49 (1.4%) were readmitted for the management of PDPSC (readmit PDPSC) and were compared with patients who were not readmitted (no readmit, n = 3,257). The readmit PDPSC group was significantly older age, heavier, comprised of fewer men, and suffered a higher mean chest AIS score. The readmit PDPSC group had a significantly higher incidence of rib fractures, flail chest, pneumothorax, hemothorax, scapula fractures, and a higher rate of tube thoracostomy placement during index admission. The discharge chest X-ray in the readmit PDPSC group demonstrated a pleural space abnormality in 36 (73%) of patients. Mean time to readmission was 10.2 (7.2) days, and hospital length of stay on readmission was 5.8 (3.7) days. Pleural effusion was the most common readmission diagnosis (44 [90%]), and 42 (86%) required tube thoracostomy.
Conclusion:
We describe the subset of chest wall injury patients who require hospital readmission for PDPSC. Characteristics from index hospitalization associated with PDPSC include older age, female sex, heavier weight, presence of rib fractures, pleural space abnormality, scapular fracture, and chest tube placement. Further studies are needed to characterize this at-risk chest wall injury population, and to determine what interventions can facilitate outpatient management of postdischarge pleural space complications and mitigate readmission risk.
Level Of Evidence:
Prognostic and epidemiologic, Level IV; Care management, Level V.

Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:13
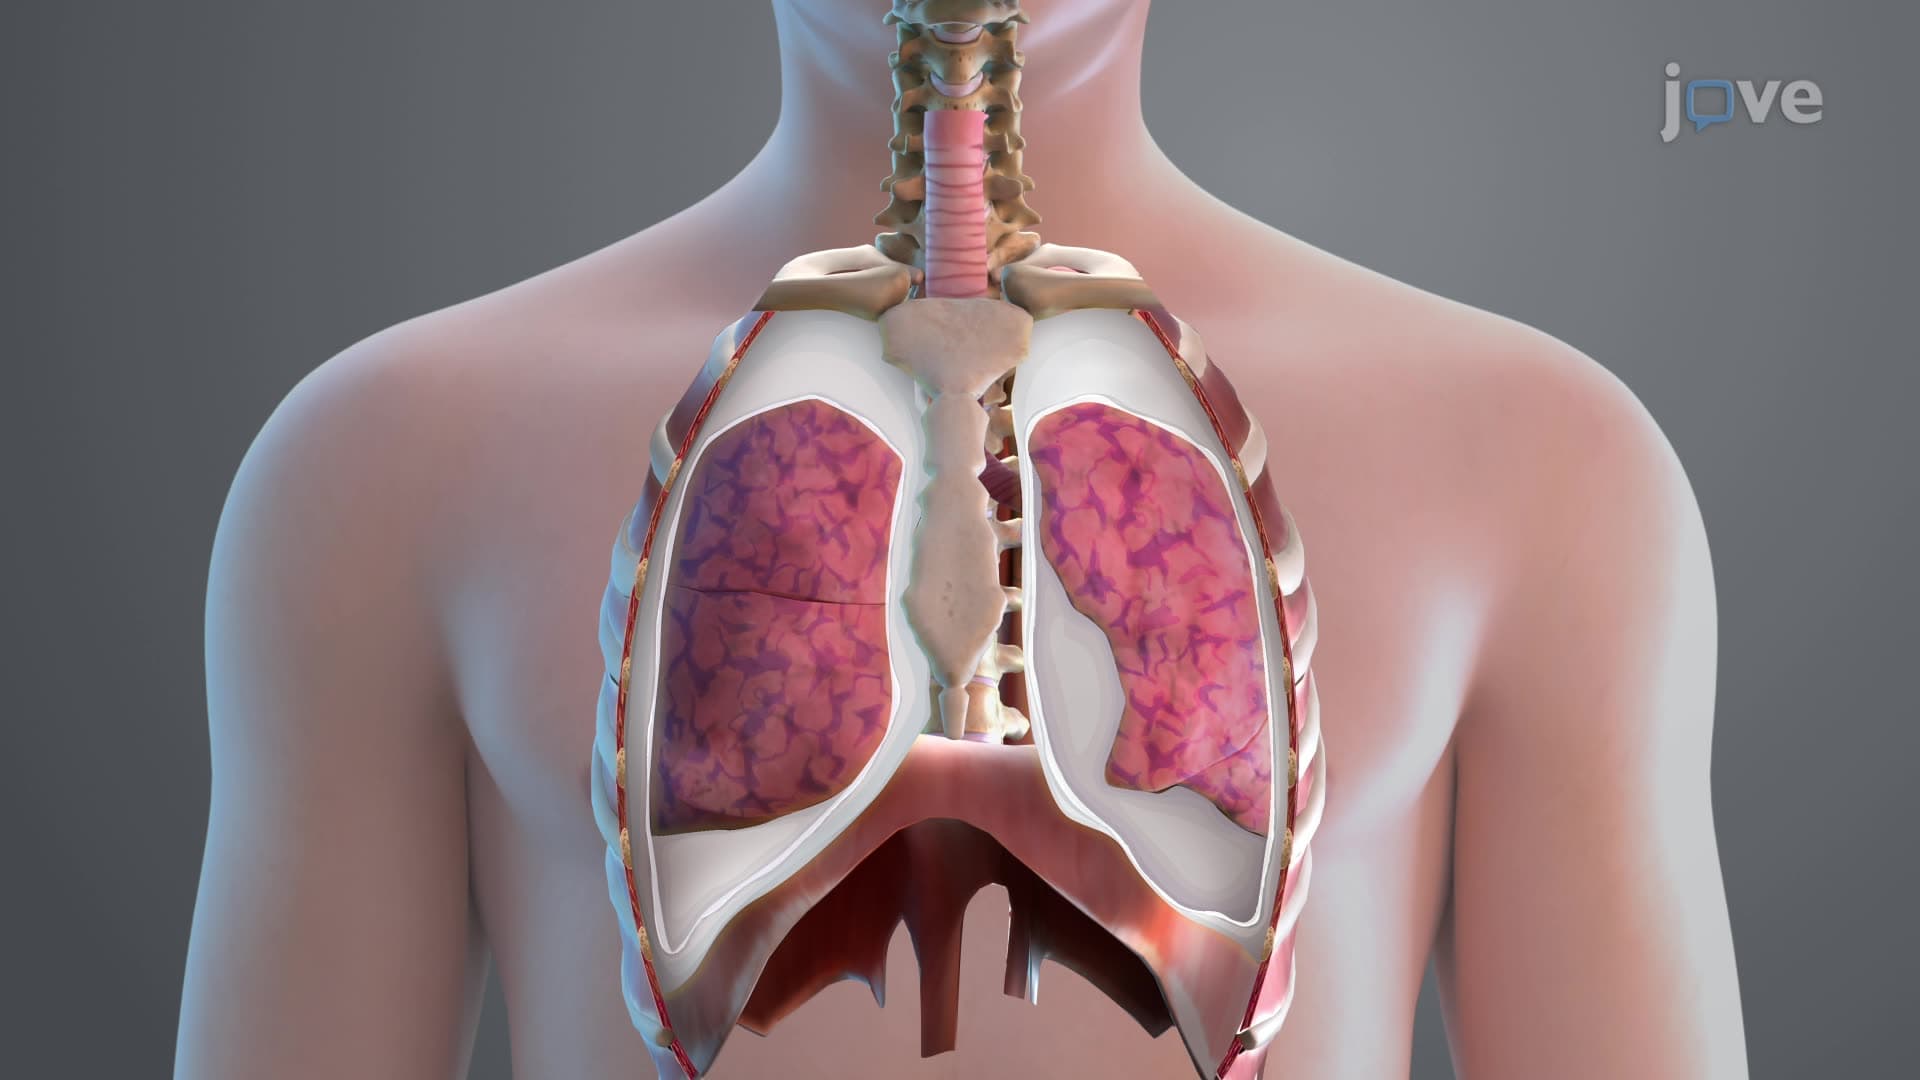
Pleura of the Lungs
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: