
Distinctive characteristics of His bundle potentials in patients with atrioventricular nodal reentrant tachycardia
Fu Guan1,2, Ardan M Saguner3, Daniel Hofer3
1Arrhythmia and Electrophysiology Division, Department of Cardiology, University Heart Center, Zurich, Switzerland. fu.guan@usz.ch.

Insights
Maximal His bundle (HB) potential amplitude and duration are significantly higher in patients with atrioventricular nodal reentrant tachycardia (AVNRT) compared to atrioventricular reentrant tachycardia (AVRT). These HB characteristics can help identify slow pathways (SP) in AVNRT.
Area of Science:
- Electrophysiology
- Cardiac Arrhythmias
- Cardiology
Background:
- His bundle (HB) potentials exhibit variable amplitude and duration in patients with and without slow pathways (SP).
- Understanding HB potential characteristics may aid in identifying SPs.
Purpose of the Study:
- To characterize His bundle potentials in patients with atrioventricular nodal reentrant tachycardia (AVNRT) and atrioventricular reentrant tachycardia (AVRT).
- To determine if HB potential characteristics can identify slow pathways (SP) in AVNRT.
Main Methods:
- Prospective electrophysiological study of 162 patients with symptomatic AVNRT or AVRT.
- Recorded maximal His bundle potential (HBmax) amplitude and duration.
- Measured AH interval (A2H2) and distances from HBmax to ablation site (HBmax-ABL) and coronary sinus ostium (HBmax-CSO) in AVNRT patients.
Main Results:
- HBmax amplitude (0.29 ± 0.10 mV vs 0.17 ± 0.05 mV) and duration (22 ± 5 ms vs 16 ± 3 ms) were significantly higher in AVNRT than AVRT patients (p < 0.0001).
- Optimal HBmax amplitude cutoff (≥ 0.22 mV) predicted AVNRT with 78% sensitivity and 84% specificity (AUC 0.86).
- HBmax-ABL positively correlated with A2H2 and HBmax-CSO, indicating HBmax proximity to SP and coronary sinus.
Conclusions:
- Higher HBmax amplitude and duration distinguish AVNRT from AVRT.
- HBmax characteristics, particularly its distance to the ablation site and coronary sinus, correlate with slow pathway conduction time, aiding SP identification.
Background:
His bundle (HB) potentials vary in amplitude and duration in patients with and without slow pathways. The aim of this study was to determine the characteristics of HB potentials and to elucidate whether they can provide clues for identification of slow pathway (SP).
Methods:
The present research prospectively studied the electrophysiological findings of 162 patients with symptomatic atrioventricular nodal reentrant tachycardia (AVNRT) due to slow-fast or fast-slow type and atrioventricular reentrant tachycardia (AVRT). Maximal HB potential (HBmax, HB with the highest amplitude) among HB cloud was recorded in both groups. For AVNRT patients, the following were measured: (1) AH interval at the "jump" during programmed atrial stimulation (A2H2, taken as a reflection of SP conduction time); (2) Distance from HBmax to the successful SP ablation site (HBmax-ABL) and from HBmax to the ostium of coronary sinus (HBmax-CSO).
Results:
HBmax was 0.29 ± 0.10 mV in AVNRT patients, whereas it was 0.17 ± 0.05 mV in AVRT group (p < 0.0001). Likewise, the HBmax duration was 22 ± 5 ms in AVNRT group and 16 ± 3 ms in AVRT group (p < 0.0001). The area under the receiver operating characteristic curve of HBmax amplitude in AVNRT patients was 0.86 and the optimal HBmax cut-off to predict AVNRT was ≥ 0.22 mV with a sensitivity of 0.78 and specificity of 0.84. HBmax-CSO was positively correlated with HBmax-ABL, and HBmax-ABL was positively correlated with A2H2.
Conclusions:
HBmax amplitudes were higher and durations longer in patients with AVNRT, as compared to those with AVRT. Moreover, the distance between HBmax and successful ablation site was positively correlated with the SP conduction time and with the distance from HBmax to the CSO.


Related Concept Videos
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
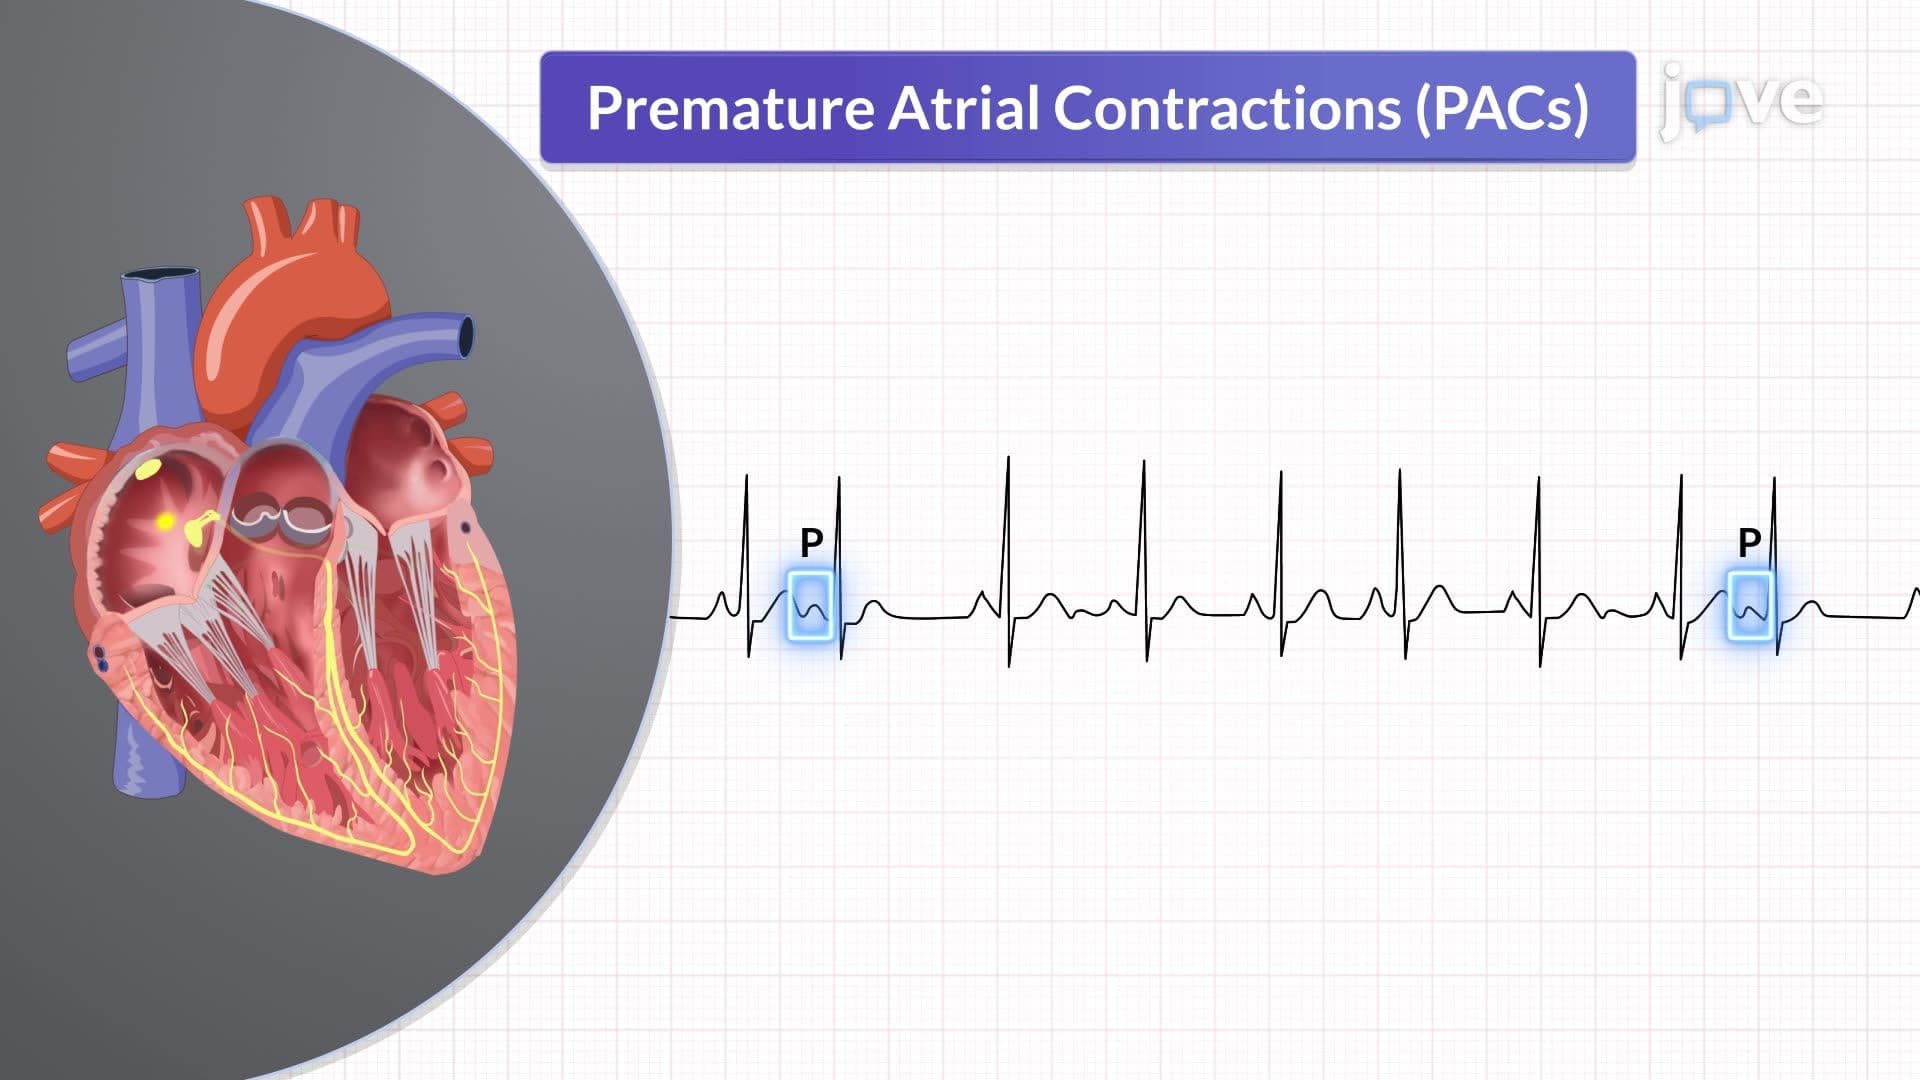
Dysrhythmias III: Characteristics of Dysrhythmias
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:19
Conduction System of the Heart
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:28
Mechanism of Cardiac Arrhythmias