

Perineural spread of peripheral neurolymphomatosis to the cauda equina
Nikhil K Murthy1, Kimberly K Amrami2, Stephen M Broski2
11Department of Neurosurgery, Mayo Clinic, Rochester.

Objective:
Neurolymphomatosis (NL) is a rare manifestation of lymphoma confined to the peripheral nervous system that is poorly understood. It can be found in the cauda equina, but extraspinal disease can be underappreciated. The authors describe how extraspinal NL progresses to the cauda equina by perineural spread and the implications of this on timely and safe diagnostic options.
Methods:
The authors used the Mayo Clinic medical records database to find cases of cauda equina NL with sufficient imaging to characterize the lumbosacral plexus diagnosed from tissue biopsy. Demographics (sex, age), clinical data (initial symptoms, cerebrospinal fluid, evidence of CNS involvement, biopsy location, primary or secondary disease), and imaging findings were reviewed.
Results:
Ten patients met inclusion and exclusion criteria, and only 2 of 10 patients presented with cauda equina symptoms at the time of biopsy, with 1 patient undergoing a cauda equina biopsy. Eight patients were diagnosed with diffuse large B-cell lymphoma, 1 with low-grade B-cell lymphoma, and 1 with mantle cell lymphoma. Isolated spinal nerve involvement was identified in 5 of 10 cases, providing compelling evidence regarding the pathophysiology of NL. The conus medullaris was not radiologically involved in any case. Lumbosacral plexus MRI was able to identify extraspinal disease and offered diagnostically useful biopsy targets. FDG PET/CT was relatively insensitive for detecting disease in the cauda equina but was helpful in identifying extraspinal NL.
Conclusions:
The authors propose that perineural spread of extraspinal NL to infiltrate the cauda equina occurs in two phases. 1) There is proximal and distal spread along a peripheral nerve, with eventual spread to anatomically connected nerves via junction and branch points. 2) The tumor cells enter the spinal canal through corresponding neural foramina and propagate along the spinal nerves composing the cauda equina. To diffusely infiltrate the cauda equina, a third phase occurs in which tumor cells can spread circumdurally to the opposite side of the spinal canal and enter contralateral nerve roots extending proximally and distally. This spread of disease can lead to diffuse bilateral spinal nerve disease without diffuse leptomeningeal spread. Recognition of this phasic mechanism can lead to identification of safer extraspinal biopsy targets that could allow for greater functional recovery after appropriate treatment.

Related Concept Videos
 01:54
The Spinal Cord
 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:15
Spinal Cord: Gross Anatomy
 01:23
Spinal Nerves: Anatomy
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...
 01:24
Peripheral Nervous System: Ganglia and Nerves
Nerves
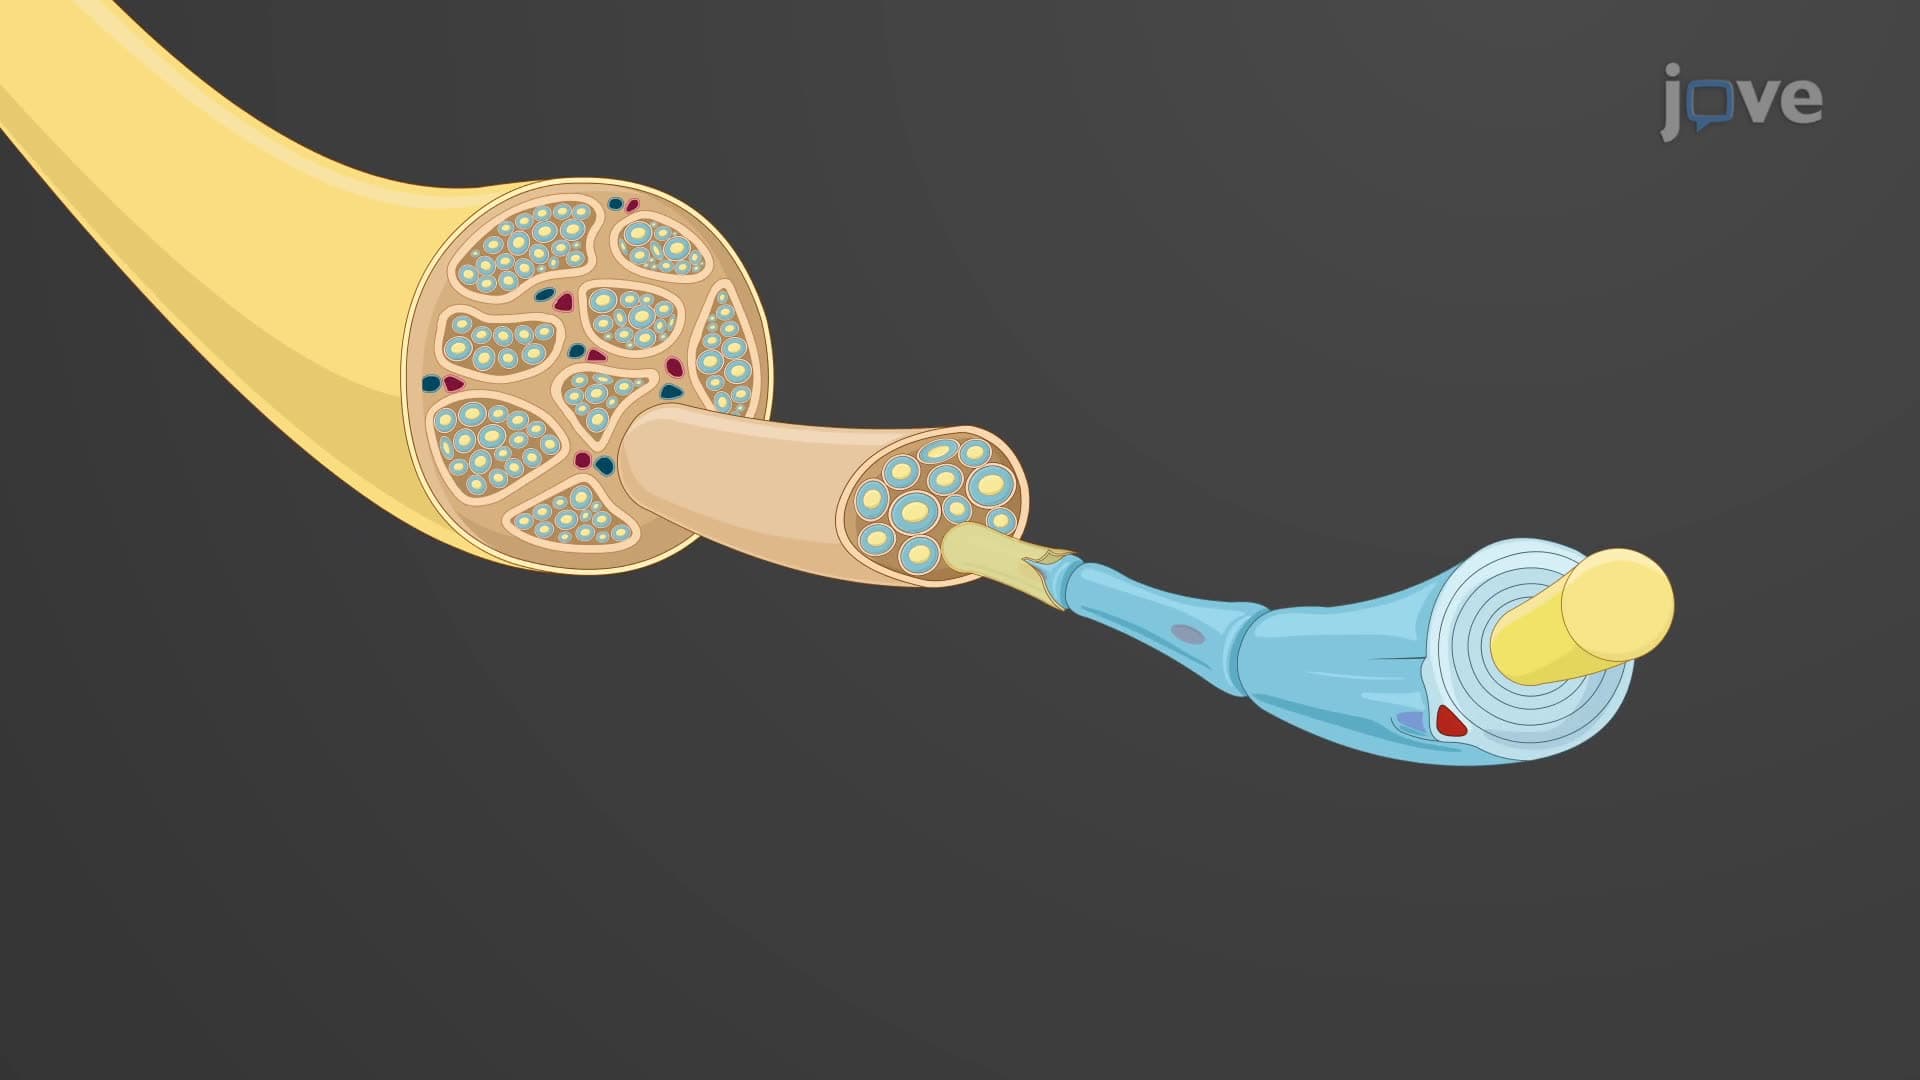
The nerve is a bundle of axons that serves as the communication highway in the PNS. Each nerve is ensheathed in a protective layer of connective tissue called the epineurium. This outermost layer safeguards the nerve and supports the...
 01:28
Major Somatic Sensory Pathways