Related Experiment Video
Updated: Oct 17, 2025
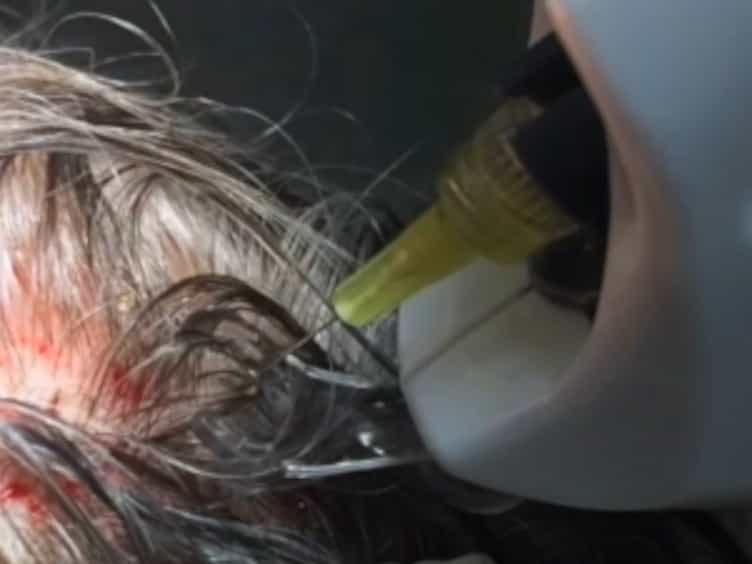
Mechanical and Controlled PRP Injections in Patients Affected by Androgenetic Alopecia
Published on: January 27, 2018
Autologous platelet-rich plasma treatment for moderate-severe Asherman syndrome: the first experience
Lusine Aghajanova1,2, Viji Sundaram3, Chia-Ning Kao3
1Division of Reproductive Endocrinology and Infertility, Department of Obstetrics, Gynecology and Reproductive Sciences, University of California San Francisco, San Francisco, CA, USA. aghajano@stanford.edu.

Purpose:
Treatment of Asherman syndrome (AS) presents a significant clinical challenge. Based on our in vitro data showing that PRP could activate endometrial cell proliferation and migration, we hypothesized that intrauterine infusion of autologous platelet-rich plasma (PRP) may improve endometrial regeneration and fertility outcomes in patients with moderate-severe AS.
Materials And Methods:
Subjects with moderate-severe AS were randomized to PRP or saline control administered following hysteroscopic adhesiolysis. Due to relative inability to randomize patients to the control group, after initial randomization of 10 subjects (6 in PRP and 4 in control groups), the remainder were prospectively enrolled in PRP group (n = 9), with 11 historic controls added to control group, for a total of 30 subjects (PRP n = 15; saline control n = 15). Right after hysteroscopy, 0.5-1 mL of PRP or saline was infused into the uterus via a Wallace catheter, followed by estrogen therapy. The primary outcomes were changes in endometrial thickness (EMT, checked in 3 weeks) and in menstrual flow; secondary outcomes were pregnancy and live birth rates. EMT and menstrual bleeding pattern were assessed before and after the intervention. Pregnancy was assessed over a 6-month period.
Results:
There were no statistically significant differences in age, gravidity/parity, cause of AS, preoperative menses assessment, AS hysteroscopy score, and intrauterine balloon placement between the groups. There was no statistically significant difference (p = 0.79) in EMT pre-PRP infusion for control (5.7 mm, 4.0-6.0) and study arm (5.3 mm, 4.9-6.0). There was no statistically significant change (p = 0.78) in EMT after PRP infusion (1.4 mm, - 0.5-2.4) vs saline (1.0 mm, 0.0-2.5). Patients tolerated the procedure well, with no adverse effects. There was no difference in the predicted likelihood of pregnancy (p = 0.45) between the control (0.67, 0.41-0.85) and study arm (0.53, 0.29-0.76).
Conclusions:
PRP was well accepted and tolerated in AS patients. However, we did not observe any significant EMT increase or improved pregnancy rates after adding PRP infusion, compared to standard treatment only. The use of intrauterine PRP infusion may be a feasible option, and its potential use must be tested on a larger sample size of AS patients.
More Related Videos

Related Concept Videos
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:27
Peripheral Artery Disease III: Interprofessional Care