Related Experiment Video
Updated: Oct 17, 2025


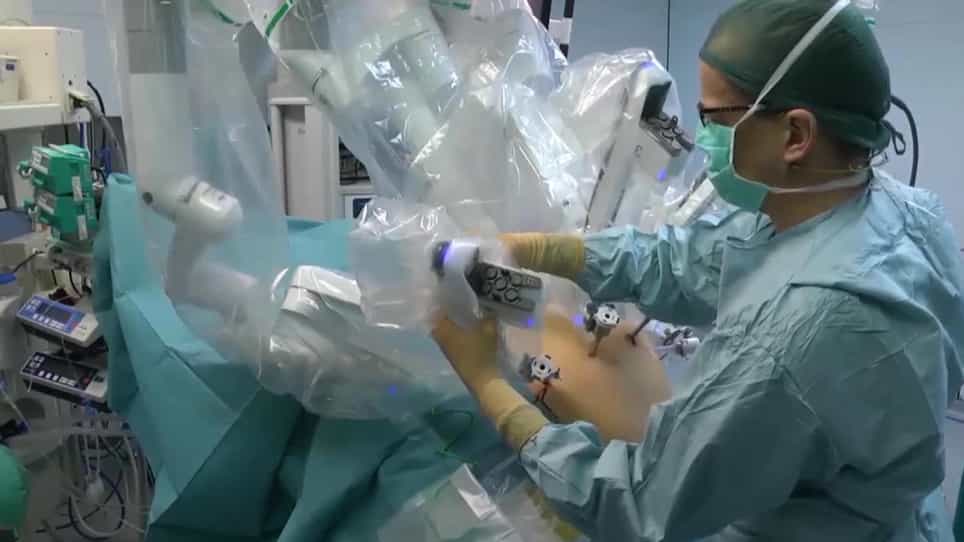
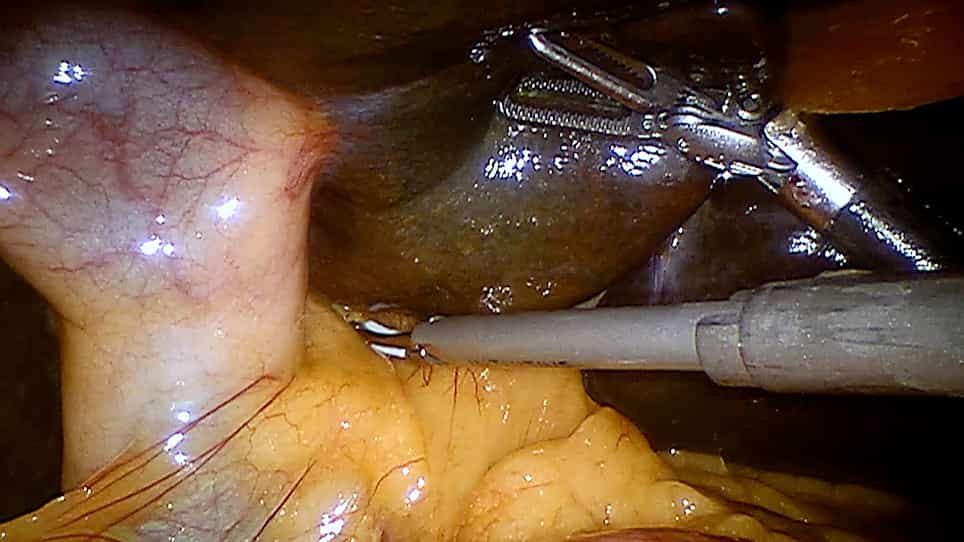
Retzius-Sparing Robot-Assisted Radical Prostatectomy
Published on: May 19, 2022
Clinical indications for necessary and discretionary hospital readmissions after radical cystectomy
Ahmet Murat Aydin1, Richard R Reich2, Biwei Cao2
1Department of Genitourinary Oncology, H. Lee Moffitt Cancer Center & Research Institute, Tampa, FL; Present Address: Department of Urology, University of Arkansas for Medical Sciences, 4301 W Markham St, Little Rock, AR 72205.

Background:
To assess predictors, indicators and medical necessity of readmissions after neoadjuvant chemotherapy and radical cystectomy in order to identify opportunities for reducing readmission rates.
Methods:
Records for patients treated with cisplatin-based neoadjuvant chemotherapy followed by radical cystectomy between 2007 and 2017 were reviewed for 90-day complications and readmission. Readmissions were classified as necessary vs. discretionary based on independent clinician review. The association between postoperative complications and necessary or discretionary readmission were examined with adjusted regression models.
Results:
Among a total of 250 patients, 76 patients (30.4%) were readmitted within 90 days of surgery (19 discretionary and 57 necessary). Age, insurance coverage, and comorbidity were similar between readmitted and non-readmitted patients. Readmission was more likely after neobladder than ileal conduit (39% vs. 23%, P = 0.02). Major (grade ≥ 3) complications within 90-day of surgery including index admission and post-discharge period were significantly more common among re-admitted patients compared to patients who were not readmitted (40% in necessary, 21% in discretionary, 3% in none, P < 0.001). Median length of stay on readmission was twice as long in necessary cases compared to discretionary cases (5 vs. 2.5 days, P < 0.001). Gastrointestinal and infectious complications were associated with discretionary readmission in adjusted analyses, while infectious, renal/genitourinary and thromboembolic complications were associated with necessary readmission.
Conclusions:
Twenty-five percent of readmissions were categorized as discretionary and were driven primarily by low-grade gastrointestinal complications, marginal oral intake and failure to thrive, suggesting that better coordinated post-discharge supportive care could help avoid a substantial proportion of readmissions.
Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination
 01:26
Kidney Transplant II: Surgical Procedure