Related Experiment Video
Updated: Oct 16, 2025
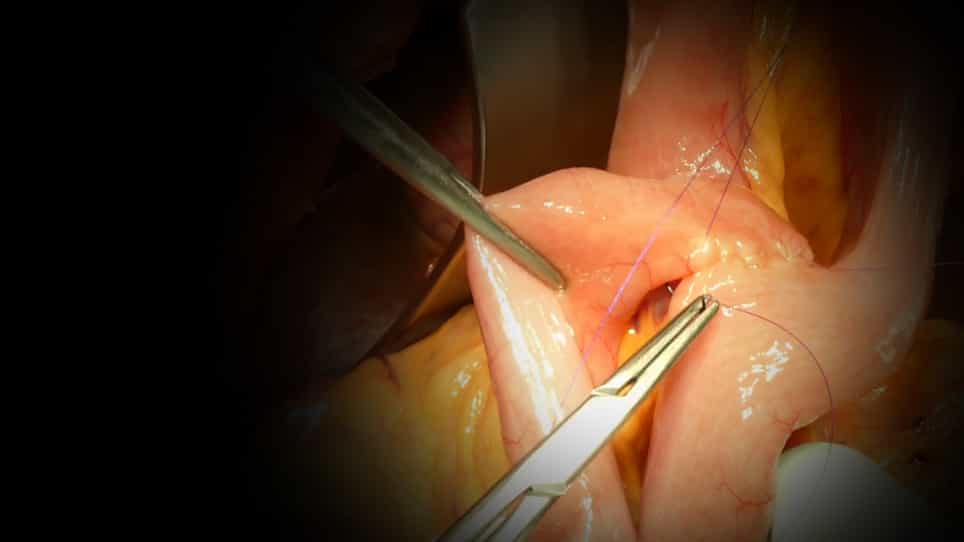
Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019
Drain fluid amylase and lipase as a predictive factor of postoperative pancreatic fistula
Sharnice Koek1,2, Sophie Wiegele1, Mohammed Ballal1,2
1Department of General Surgery, Fiona Stanley Hospital, Murdoch, Western Australia, Australia.

Insights
Early detection of postoperative pancreatic fistula (POPF) after pancreaticoduodenectomy (PD) is crucial. Postoperative drain fluid lipase (DFL) on postoperative day 3 is a highly accurate predictor of POPF, enabling earlier intervention.
Area of Science:
- Gastroenterology
- Surgical Oncology
- Abdominal Surgery
Background:
- Postoperative pancreatic fistula (POPF) is a significant complication following pancreaticoduodenectomy (PD).
- Early detection of POPF is essential for improving patient outcomes.
- Drain fluid amylase (DFA) and drain fluid lipase (DFL) are potential biomarkers for POPF detection.
Purpose of the Study:
- To evaluate the predictive value of postoperative drain fluid amylase (DFA) and drain fluid lipase (DFL) measurements for the development of POPF.
- To identify the optimal timing and biomarker for early POPF detection.
Main Methods:
- Retrospective cohort study of 169 patients undergoing PD between 2009 and 2017.
- DFA and DFL levels were measured on postoperative days (POD) 3 and 5.
- Correlation of DFA and DFL measurements with the incidence of clinically significant POPF.
Main Results:
- 17.1% of patients developed clinically significant POPF.
- Significantly higher DFA and DFL levels were observed in patients who developed POPF (P < 0.001).
- Postoperative day 3 DFL measurement demonstrated the highest predictive accuracy (AUC 0.85) with a negative predictive value of 97.4%.
Conclusions:
- Drain fluid lipase (DFL) measurement on postoperative day 3 is a reliable and accurate predictor of clinically significant POPF.
- Utilizing POD 3 DFL measurement can lead to cost reduction, earlier drain removal, and timely identification of high-risk patients.
Background:
Early detection of a postoperative pancreatic fistula (POPF) may improve outcomes after pancreaticoduodenectomy (PD). The aim was to assess the role of postoperative drain fluid amylase (DFA) and lipase (DFL) measurements as a predictive indicator in the development of POPF.
Methods:
This retrospective cohort study included all PD procedures performed between 2009 and 2017 at Fremantle and Fiona Stanley Hospital in Western Australia. The DFA and DFL measurements on postoperative day (POD) three and five were correlated with the development of POPF.
Results:
A total of 169 patients were included in this study with a mean age of 64 ± 11.3 years. Of these, 17 (10.1%) developed a clinically significant POPF. In patients who had both a DFA and DFL measured on both POD 3 and 5, DFA and DFL was significantly higher in patients who developed POPF than those who did not (P < 0.001). In a receiver operating characteristic curve analysis, the most accurate test was POD 3 DFL measurement with an AUC 0.85 (CI 0.75-0.95, P < 0.001). A negative predictive value of 97.4% was observed. DFA and DFL were concordant in 89.2% of cases on POD 3 and 90.6% of cases on POD 5.
Conclusion:
In this study, DFL measured on POD 3 as a single measurement appears to carry the most benefit in prediction of clinically significant POPF. Reduction to a measurement on this day may lead to a reduction in cost, earlier drain removal and earlier identification of high-risk patients.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:26
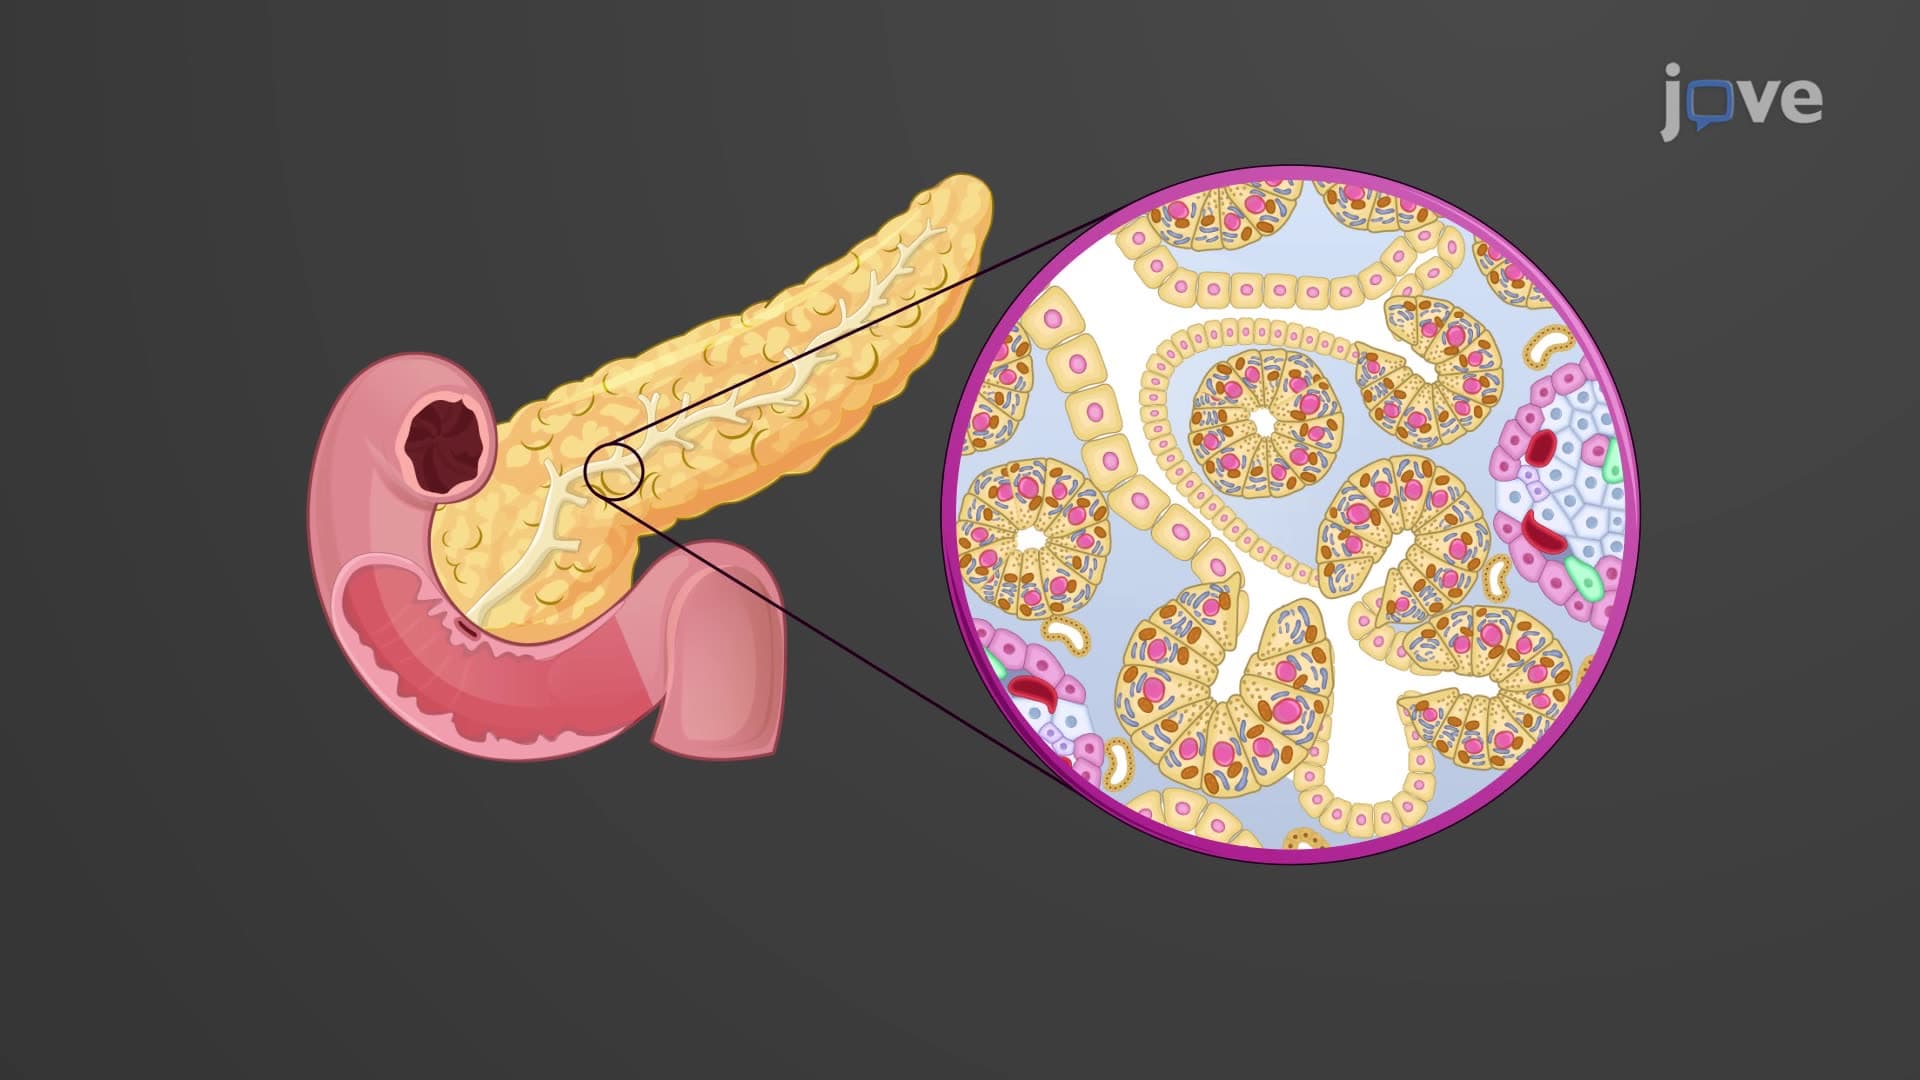
Pancreatic Juice and Secretion
When acidic chyme from the stomach enters the duodenum, it triggers the release of secretin, a hormone that prompts pancreatic juice secretion. After a fatty meal, cholecystokinin, another hormone, stimulates gallbladder contraction and enhances enzyme-rich...