Related Experiment Video
Updated: Oct 15, 2025
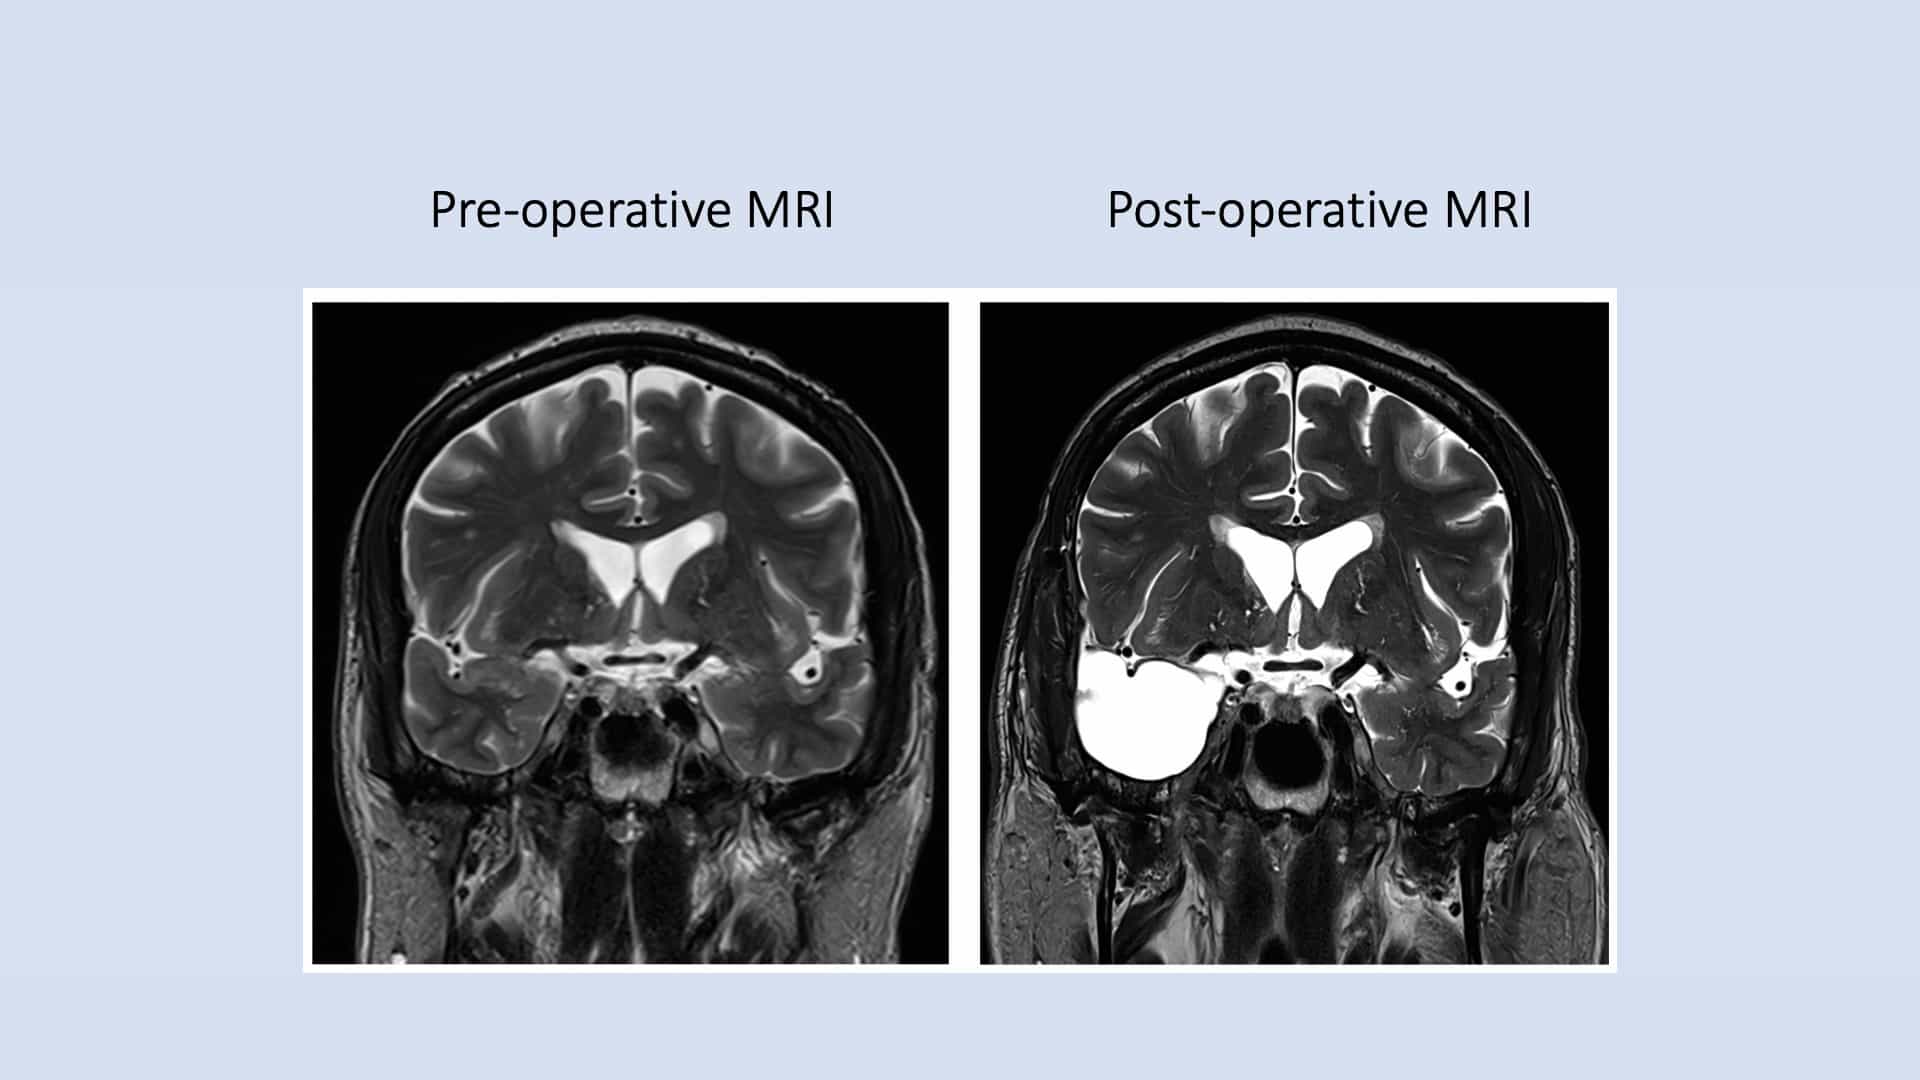
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
[Surgical treatment of drug-resistant epilepsy following hippocampal sclerosis]
D I Pitskhelauri1, E S Kudieva1, A G Melikyan1
1Burdenko Neurosurgical Center, Moscow, Russia.

Abstract:
Surgery is an effective approach for drug-resistant temporal lobe epilepsy following hippocampal sclerosis. There is still no clear and unanimous opinion about advantages and disadvantages of certain surgical technique.
Material And Methods:
There were 103 surgical interventions in 101 patients. Females prevailed (1.45:1). Age of patients ranged from 16 to 56 years (median 28). Anteromedial temporal lobectomy and selective amygdaloghippocampectomy were performed in 49 (47.6%) and 54 (52.4%) patients, respectively. In the latter group, 30 patients were operated via a 14-mm burr hole-subtemporal approach. Postoperative outcomes were assessed using the Engel grading system. The follow-up period ranged from 2 to 8 years (median 4 years).
Results:
By the 2nd year, Engel class I was observed in 74 (72%) patients, Engel II, III and IV - in 20 (19.4%), 6 (5.8%) and 3 (2.9%) patients, respectively. Engel class I was achieved after anteromedial temporal lobectomy in 68% of cases, selective amygdaloghippocampectomy via standard approaches in 75% of cases, amygdaloghippocampectomy via subtemporal burr hole approach - in 80% of cases. Neurocognitive impairments after anteromedial lobectomy and selective amygdaloghippocampectomy were similar. At the same time, mental disorders de novo prevailed in the group of anteromedial lobectomy (p<0.05). There were no severe visual field disorders after subtemporal burr-hole access. In other cases, these disorders occurred in 36.2% of patients (p<0.05). There were 8 (7.8%) postoperative complications: 5 (10.2%) - after anterior temporal lobectomy, 3 (5.5%) - after selective surgeries via standard approaches. There were no complications after burr-hole surgery.
Conclusion:
Selective amygdaloghippocampectomy is not inferior to anteromedial lobectomy. Moreover, this procedure is associated with a lower risk of complications and adverse events.


Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:14
Antiepileptic Drugs: Glutamate Antagonists
 01:30
Psychosurgery
Historical Development of Psychosurgery
In the 1930s, Portuguese neurologist Antonio Egas Moniz introduced a surgical procedure designed...