Related Experiment Video
Updated: Oct 15, 2025
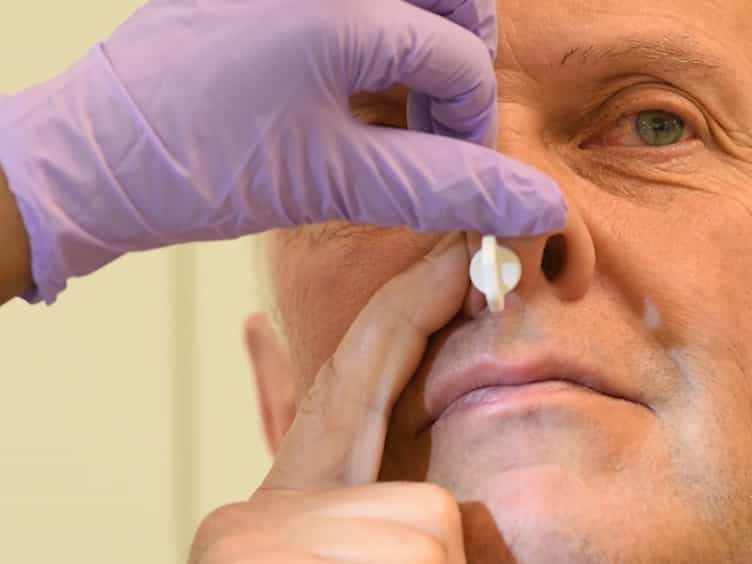
Absorption of Nasal and Bronchial Fluids: Precision Sampling of the Human Respiratory Mucosa and Laboratory Processing of Samples
Published on: January 21, 2018
Effect of CRTH2 antagonism on the response to experimental rhinovirus infection in asthma: a pilot randomised
Hugo Farne1, Nicholas Glanville1, Nicholas Johnson2
1National Heart and Lung Institute, Imperial College London, London, UK.

Background And Aims:
The chemoattractant receptor-homologous molecule expressed on T helper type 2 cells (CRTH2) antagonist timapiprant improved lung function and asthma control in a phase 2 study, with evidence suggesting reduced exacerbations. We aimed to assess whether timapiprant attenuated or prevented asthma exacerbations induced by experimental rhinovirus (RV) infection. We furthermore hypothesised that timapiprant would dampen RV-induced type 2 inflammation and consequently improve antiviral immune responses.
Methods:
Atopic patients with partially controlled asthma on maintenance inhaled corticosteroids were randomised to timapiprant (n=22) or placebo (n=22) and challenged with RV-A16 3 weeks later. The primary endpoint was the cumulative lower respiratory symptom score over the 14 days post infection. Upper respiratory symptoms, spirometry, airway hyperresponsiveness, exhaled nitric oxide, RV-A16 virus load and soluble mediators in upper and lower airways samples, and CRTH2 staining in bronchial biopsies were additionally assessed before and during RV-A16 infection.
Results:
Six subjects discontinued the study and eight were not infected; outcomes were assessed in 16 timapiprant-treated and 14 placebo-treated, successfully infected subjects. There were no differences between treatment groups in clinical exacerbation severity including cumulative lower respiratory symptom score day 0-14 (difference 3.0 (95% CI -29.0 to 17.0), p=0.78), virus load, antiviral immune responses, or RV-A16-induced airway inflammation other than in the bronchial biopsies, where CRTH2 staining was increased during RV-A16 infection in the placebo-treated but not the timapiprant-treated group. Timapiprant had a favourable safety profile, with no deaths, serious adverse events or drug-related withdrawals.
Conclusion:
Timapiprant treatment had little impact on the clinicopathological changes induced by RV-A16 infection in partially controlled asthma.


Related Concept Videos
 01:20
Antiasthma Drugs: Muscarinic Receptor Antagonists
Antimuscarinic agents compete with ACh for the same binding site on the muscarinic receptors. By binding to these receptors, they inhibit the downstream effects of ACh and block the parasympathetic...
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by...
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms: