Related Experiment Video
Updated: Oct 12, 2025
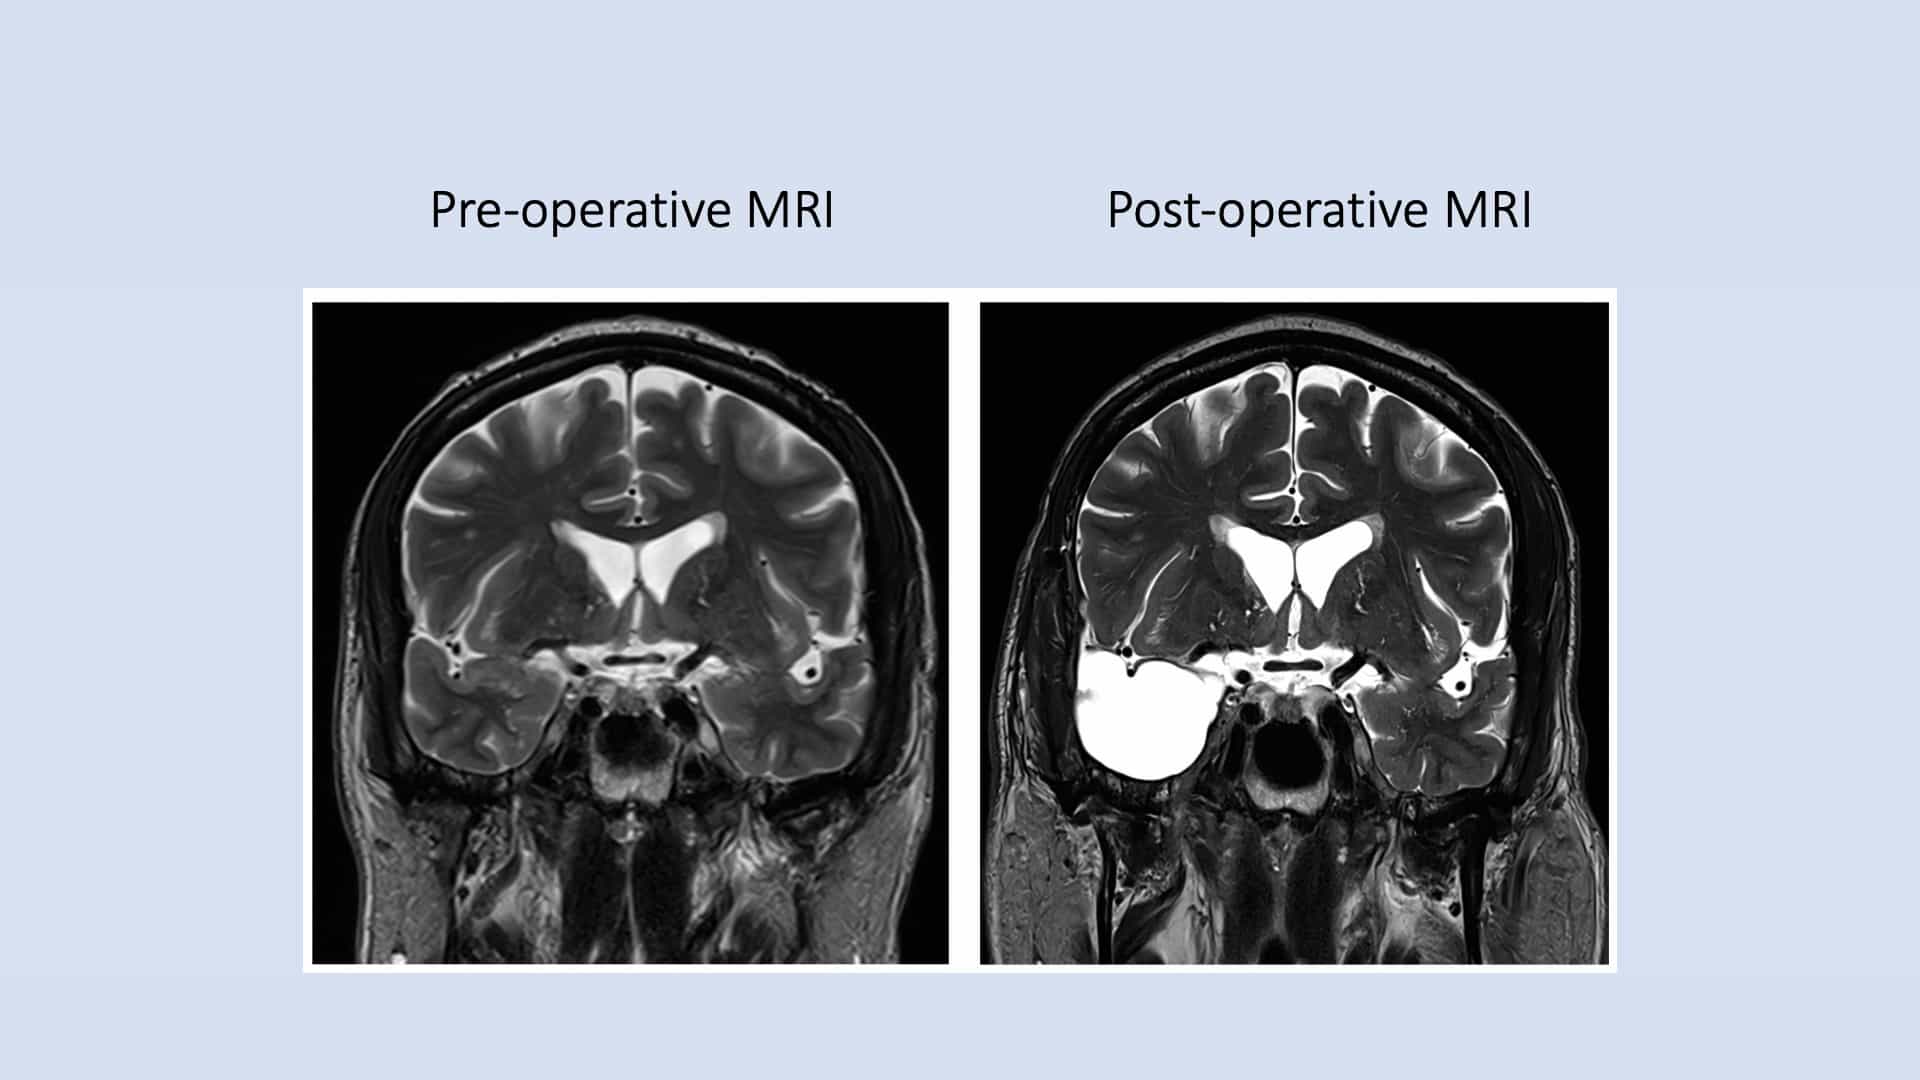
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Outcomes of cingulate epilepsy surgery: insights from an institutional and patient-level systematic review and
Panagiotis Kerezoudis1, Rohin Singh2, Gregory A Worrell3
11Department of Neurologic Surgery, Mayo Clinic, Rochester, Minnesota.

Objective:
Due to their deep and medial location, range of seizure semiologies, and poor localization on ictal electroencephalography (EEG), cingulate gyrus seizures can be difficult to diagnose and treat. The aim of this study was to review the available evidence on postoperative outcomes after cingulate epilepsy surgery.
Methods:
A comprehensive literature search of the PubMed/MEDLINE, Ovid Embase, Ovid Scopus, and Cochrane Library databases was conducted to identify studies that investigated postoperative outcomes of patients with cingulate epilepsy. Seizure freedom at the last follow-up (at least 12 months) was the primary endpoint. The literature search was supplemented by the authors' institutional series (4 patients).
Results:
Twenty-one studies were identified, yielding a total of 105 patients (68 with lesional epilepsy [65%]). Median age at surgery was 23 years, and 56% of patients were male. Median epilepsy duration was 7.5 years. Invasive EEG recording was performed on 69% of patients (53% of patients with lesional epilepsy and 97% of those with nonlesional epilepsy, p < 0.001). The most commonly resected region was the anterior cingulate (55%), followed by the posterior (17%) and middle (14%) cingulate. Lesionectomy alone was performed in 9% of patients. Additional extracingulate treatment was performed in 54% of patients (53% of patients with lesional epilepsy vs 57% of those with nonlesional epilepsy, p = 0.87). The most common pathology was cortical dysplasia (54%), followed by low-grade neoplasm (29%) and gliosis (8%). Seizure freedom was noted in 72% of patients (median follow-up 24 months). A neurological deficit was noted in 27% of patients (24% had temporary deficit), with the most common deficit being motor weakness (13%) followed by supplementary motor area syndrome (9.5%). Univariate survival analysis revealed significantly greater probability of seizure freedom in patients with lesional epilepsy (p = 0.015, log-rank test).
Conclusions:
Surgical treatment of drug-resistant focal epilepsy originating from the cingulate gyrus is safe, leads to low rates of permanent adverse effects, and leads to high rates of long-term seizure freedom in carefully selected patients. These data may serve as a benchmark for surgical counseling of patients with cingulate epilepsy.
More Related Videos
 06:04
Author Spotlight: Studying Clinical Characters and Epilepsy Outcomes After Frontal Disconnection in Patients with MOGHE
Published on: August 16, 2024
 09:00
Investigating the Function of Deep Cortical and Subcortical Structures Using Stereotactic Electroencephalography: Lessons from the Anterior Cingulate Cortex
Published on: April 15, 2015
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:30
Psychosurgery
Historical Development of Psychosurgery
In the 1930s, Portuguese neurologist Antonio Egas Moniz introduced a surgical procedure designed...
 01:30
Electroconvulsive Therapy