Related Experiment Video
Updated: Oct 18, 2026
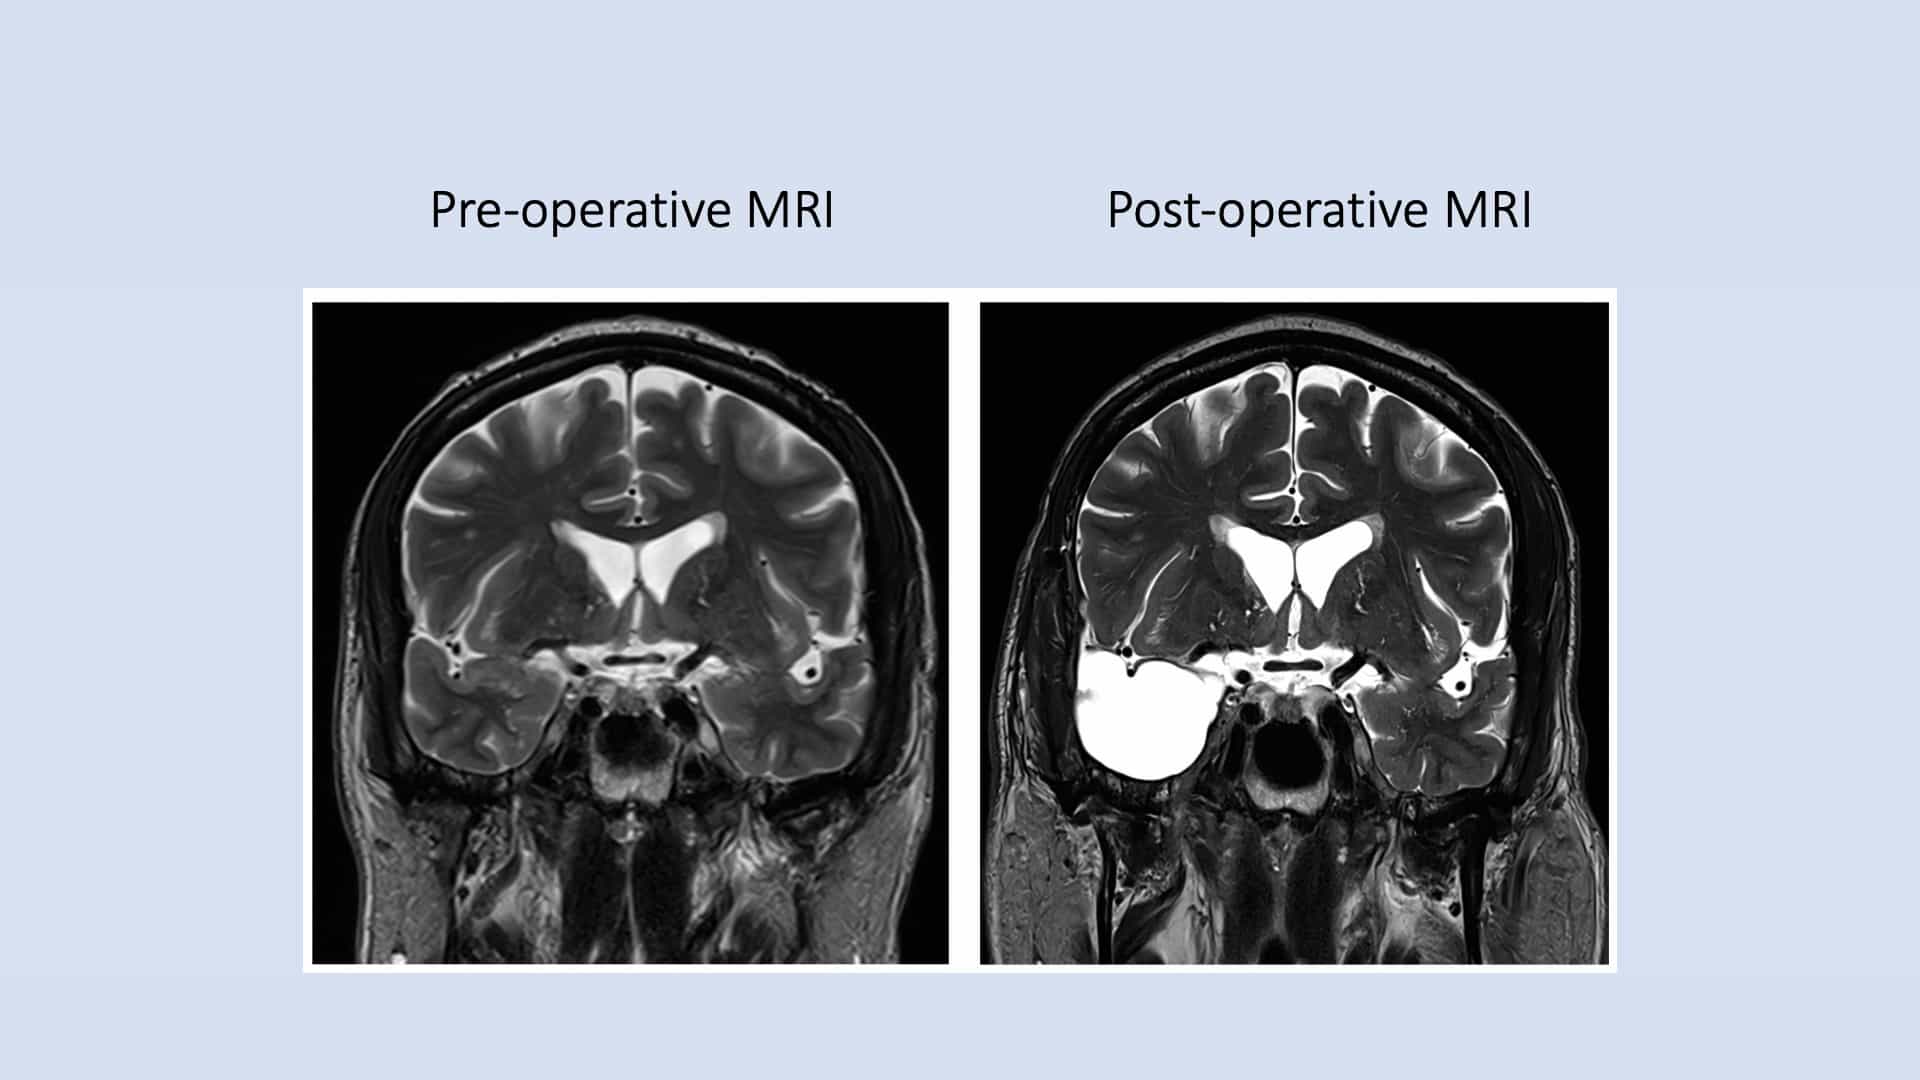
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Combining responsive neurostimulation with resection or ablation for treatment of epilepsy: a multicenter experience
Christian G Lopez Ramos1, Ahmed M Raslan1, Vikram R Rao2
11Department of Neurological Surgery, Oregon Health & Science University, Portland, Oregon.

Objective:
Despite advances in surgical and neuromodulatory treatments, a substantial proportion of patients with drug-resistant epilepsy remain ineligible for standalone resection or ablation. Combining resection or laser interstitial thermal therapy (LITT) with responsive neurostimulation (RNS) has emerged as a promising approach for patients with multifocal seizure onset or eloquent cortex involvement. However, the clinical impact of combination surgery remains poorly characterized. The aim of this study was to characterize the clinical rationale and surgical decision-making used across multiple high-volume epilepsy centers performing combination surgeries, and to evaluate the seizure outcomes and safety profile associated with this approach.
Methods:
This retrospective study included patients with drug-resistant epilepsy who underwent RNS implantation in combination with resection or LITT at 9 epilepsy centers and had ≥ 1 year of follow-up. Demographic, clinical, surgical, and seizure outcome data were collected. The primary outcome was seizure reduction at 1 year. Secondary outcomes included the Clinical Global Impression and adverse events.
Results:
Overall, 73 patients (40 male, mean age 34 years) with a mean epilepsy duration of 21 years were included in this analysis. The most common etiology was unknown (37%), followed by cortical malformation (16%). Most patients experienced focal impaired consciousness (FIC, 78%) and focal to bilateral tonic-clonic (FBTC, 70%) seizures. Prior resection was performed in 23%. Combination procedures were performed on the same day in 89% of patients. RNS implantation was concurrent with resection in 92% and with LITT in 8.2% of patients. Neocortical and mesial temporal regions accounted for 61% of resection/ablation targets. More than two-thirds of RNS leads were subdural strips, most commonly in the left hemisphere (73%). Indications for the combined approach included eloquent cortex involvement (67%) and multifocal seizure onset (33%) or both (9.6%). At 1 year, mean seizure reductions were 53% for focal impaired, 69% for FIC, and 67% for FBTC seizures. Overall, 48% of patients had at least a 6-month period of seizure freedom, and 4 patients had no seizures after surgery. Significant global clinical improvement (much or very much improved) was observed in 79% of patients. Three patients experienced infection, and 1 patient died due to causes unrelated to surgical treatment (sudden unexpected death in epilepsy).
Conclusions:
Combined RNS with resection or ablation might provide meaningful seizure control in complex drug-resistant epilepsy with acceptable safety profiles. These findings describe current practice and support further investigation of hybrid surgical strategies in patients with challenging seizure networks as a potential treatment strategy.
More Related Videos
 05:54
Stereo-Electro-Encephalo-Graphy (SEEG) With Robotic Assistance in the Presurgical Evaluation of Medical Refractory Epilepsy: A Technical Note
Published on: June 13, 2016
 04:50
Operative Technique and Nuances for the Stereoelectroencephalographic (SEEG) Methodology Utilizing a Robotic Stereotactic Guidance System
Published on: June 9, 2023