
Determinants of Exercise Capacity Following ST-Elevation Myocardial Infarction (STEMI)
Harry Klimis1,2, Aaisha Ferkh1,2, Paula Brown2
1Faculty of Medicine and Health, The University of Sydney, Camperdown, NSW 2006, Australia.

Insights
Reduced exercise capacity after ST-elevation myocardial infarction (STEMI) is linked to poor outcomes. Abnormal diastolic function, increased left atrial volume, and anterior infarction predict lower exercise capacity and major adverse cardiac events (MACEs) in STEMI patients.
Area of Science:
- Cardiology
- Cardiovascular Medicine
- Exercise Physiology
Background:
- Abnormal left ventricular systolic and diastolic function are linked to worse prognosis after ST-elevation myocardial infarction (STEMI).
- Limited evidence exists on the determinants of exercise capacity post-STEMI.
- This study investigated the impact of systolic and diastolic dysfunction on exercise capacity and outcomes following STEMI.
Purpose of the Study:
- To identify clinical and echocardiographic determinants of exercise capacity after STEMI.
- To determine predictors of major adverse cardiac events (MACEs) in STEMI patients.
- To elucidate the prognostic significance of diastolic dysfunction and exercise capacity post-STEMI.
Main Methods:
- Retrospective analysis of 139 STEMI patients.
- Transthoracic echocardiogram and exercise treadmill testing were performed post-STEMI.
- Outcomes included exercise capacity (METs) and MACEs.
Main Results:
- Abnormal diastolic function, increased minimum left atrial indexed volume (LAVImin ≥ 18 mL/m²), and anterior infarction independently predicted reduced exercise capacity (METs ≤ 8).
- Left ventricular ejection fraction (LVEF) did not predict reduced exercise capacity.
- Reduced exercise capacity (METs ≤ 8) and abnormal diastolic function were associated with MACEs; reduced exercise capacity independently predicted MACEs.
Conclusions:
- Increased LAVImin, anterior infarction, and abnormal diastolic function are independent predictors of reduced exercise capacity post-STEMI.
- Reduced exercise capacity is an independent predictor of MACEs.
- Abnormal diastolic function has significant prognostic and therapeutic implications in STEMI patients, distinct from systolic impairment.
Background:
Abnormal left ventricular systolic and diastolic function and reduced exercise capacity are associated with worse prognosis following ST-elevation myocardial infarction (STEMI). However, evidence is lacking on the determinants of exercise capacity following STEMI. We sought to determine the impact of systolic and diastolic dysfunction on exercise capacity and outcomes following first-ever STEMI.
Methods:
In a retrospective analysis of 139 consecutive STEMI patients who had a transthoracic echocardiogram following STEMI and completed exercise treadmill testing, the primary outcome was to identify clinical and echocardiographic determinants of exercise capacity, and the secondary outcome was to identify determinants of major adverse cardiac events (MACEs).
Results:
Mean number of metabolic equivalents (METs > 8) was used as a cut-off. Age, female sex, anterior infarction, abnormal diastolic function, minimum left atrial indexed volume (LAVImin) ≥ 18 mL/m2, average e', and E/e' were associated with METs ≤ 8, but not left ventricular ejection fraction (LVEF). On multivariate analysis, LAVImin (OR 4.3, 95%CI 1.3-14.2; p = 0.017), anterior infarction (OR 2.6, 95%CI 1.2-5.9; p = 0.022), and abnormal diastolic function (OR 3.73, 95%CI 1.7-8.4; p = 0.001) were independent predictors of METs ≤ 8. On Kaplan-Meier analysis, METs ≤ 8 (p = 0.01) and abnormal diastolic function (p = 0.04) were associated with MACEs (median follow-up 2.3 years). METs ≤ 8 was an independent predictor of MACEs (HR 3.4, 95%CI 1.2-9.8; p = 0.02).
Conclusions:
Following first-ever STEMI, increased LAVImin, anterior infarction, and abnormal diastolic function were independent predictors of reduced exercise capacity. Furthermore, reduced exercise capacity was an independent predictor of MACEs. These results highlight important prognostic and therapeutic implications related to abnormal diastolic function in STEMI patients that are distinct from those with LV systolic impairment.
More Related Videos


Related Concept Videos
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:29
Pathophysiology of Cardiac Performance
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:26
Exercise Stress Test
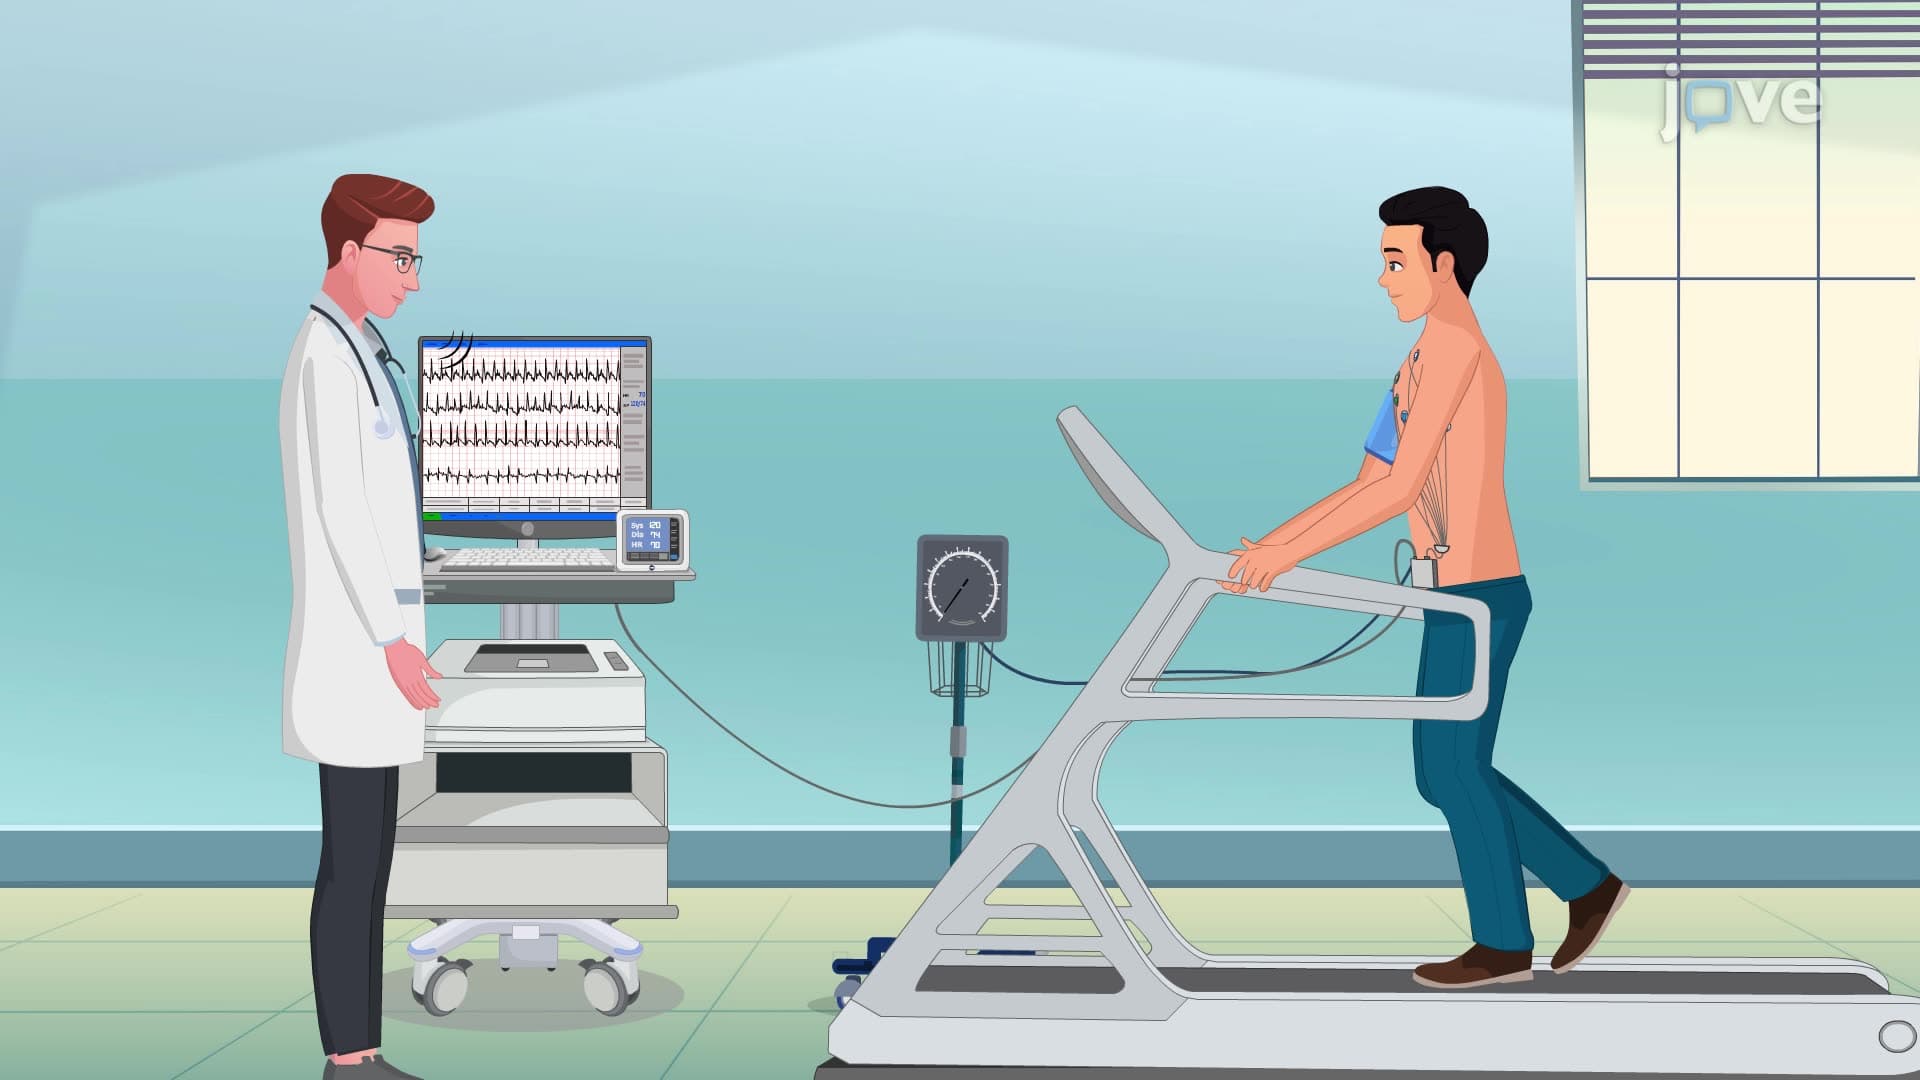
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes