Related Experiment Video
Updated: Oct 11, 2025


Establishing a Competing Risk Regression Nomogram Model for Survival Data
Published on: October 23, 2020
A novel nomogram for predicting 3-year mortality in critically ill patients after coronary artery bypass grafting
HuanRui Zhang1, Wen Tian1, YuJiao Sun2
1Department of Geriatric Cardiology, The First Affiliated Hospital of China Medical University, NO.155 Nanjing North Street, Heping Ward, Shenyang, 110001, China.

Insights
A new nomogram accurately predicts 3-year mortality in critically ill patients after coronary artery bypass grafting (CABG). This tool aids in improving long-term outcomes and patient management post-surgery.
Area of Science:
- Cardiovascular Surgery
- Critical Care Medicine
- Medical Informatics
Background:
- Long-term outcomes after coronary artery bypass grafting (CABG) are a growing concern.
- Existing models primarily focus on in-hospital mortality, with limited research on long-term prediction.
- There is a need for reliable tools to predict mortality beyond the immediate postoperative period.
Purpose of the Study:
- To develop and validate a novel nomogram for predicting 3-year mortality in critically ill patients following CABG.
- To create a tool that offers improved prognostic accuracy compared to existing methods.
Main Methods:
- Utilized data from the Medical Information Mart for Intensive Care III (MIMIC-III) database.
- Enrolled 2929 critically ill patients who underwent CABG during their first admission.
- Employed multivariable logistic regression to identify independent prognostic factors.
Main Results:
- A nomogram was constructed using seven independent prognostic factors: age, congestive heart failure, white blood cell count, creatinine, SpO2, anion gap, and continuous renal replacement treatment.
- The nomogram demonstrated accurate discrimination in both primary (AUC: 0.81) and validation cohorts (AUC: 0.802).
- Calibration curves and decision curve analysis confirmed its superior performance and clinical utility over traditional severity scores.
Conclusions:
- The developed nomogram exhibits strong performance in predicting 3-year mortality for critically ill patients post-CABG.
- This predictive model offers valuable insights for treatment strategies and post-discharge management.
- The tool has the potential to enhance long-term prognosis for this patient population.
Background:
The long-term outcomes for patients after coronary artery bypass grafting (CABG) have been received more and more concern. The existing prediction models are mostly focused on in-hospital operative mortality after CABG, but there is still little research on long-term mortality prediction model for patients after CABG.
Objective:
To develop and validate a novel nomogram for predicting 3-year mortality in critically ill patients after CABG.
Methods:
Data for developing novel predictive model were extracted from Medical Information Mart for Intensive cart III (MIMIC-III), of which 2929 critically ill patients who underwent CABG at the first admission were enrolled.
Results:
A novel prognostic nomogram for 3-year mortality was constructed with the seven independent prognostic factors, including age, congestive heart failure, white blood cell, creatinine, SpO2, anion gap, and continuous renal replacement treatment derived from the multivariable logistic regression. The nomogram indicated accurate discrimination in primary (AUC: 0.81) and validation cohort (AUC: 0.802), which were better than traditional severity scores. And good consistency between the predictive and observed outcome was showed by the calibration curve for 3-year mortality. The decision curve analysis also showed higher clinical net benefit than traditional severity scores.
Conclusion:
The novel nomogram had well performance to predict 3-year mortality in critically ill patients after CABG. The prediction model provided valuable information for treatment strategy and postdischarge management, which may be helpful in improving the long-term prognosis in critically ill patients after CABG.
More Related Videos
 06:46
Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
 07:13
Comparison of Predictive Performance of Three Lymph Node Staging Systems in Colorectal Signet Ring Cell Carcinoma Based on Machine Learning Model
Published on: April 18, 2025
Related Concept Videos
 01:23
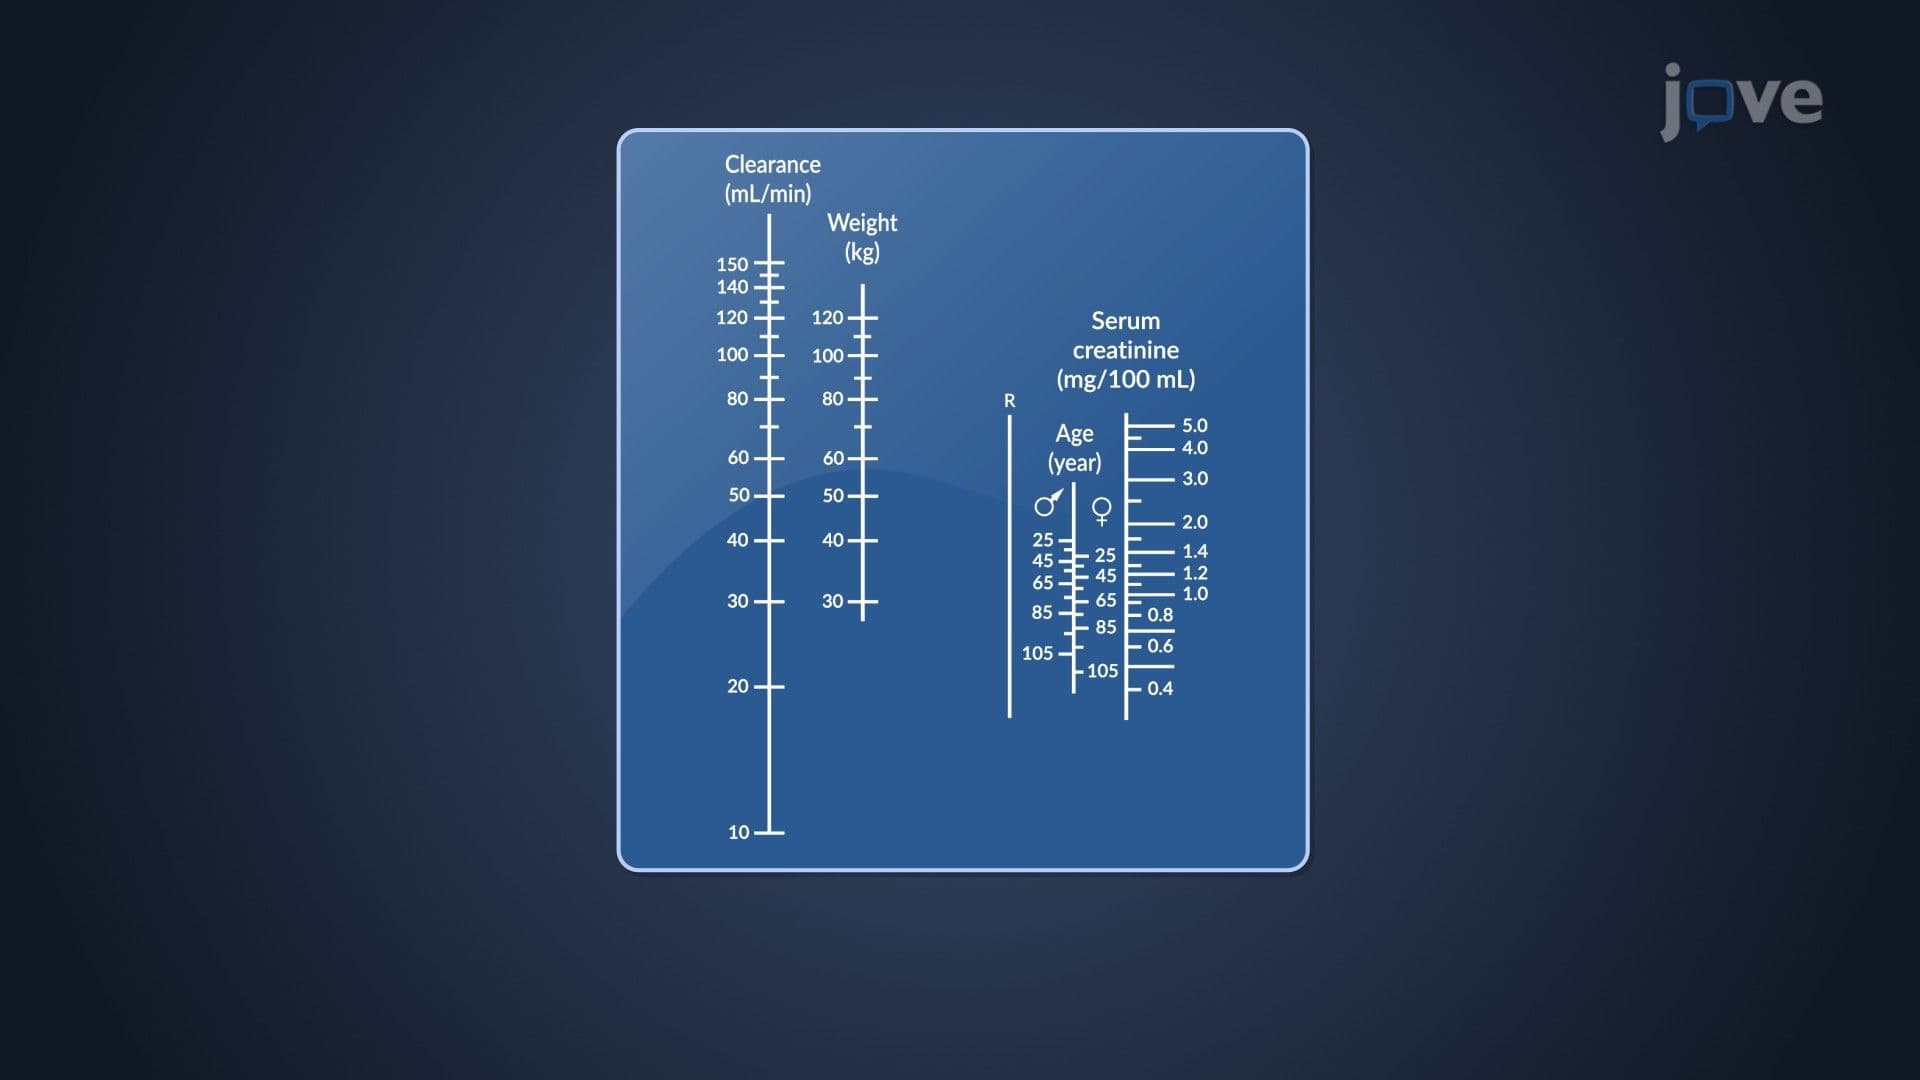
Dosage Regimen Designs: Nomograms and Tabulations
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration