Related Experiment Video
Updated: Oct 11, 2025
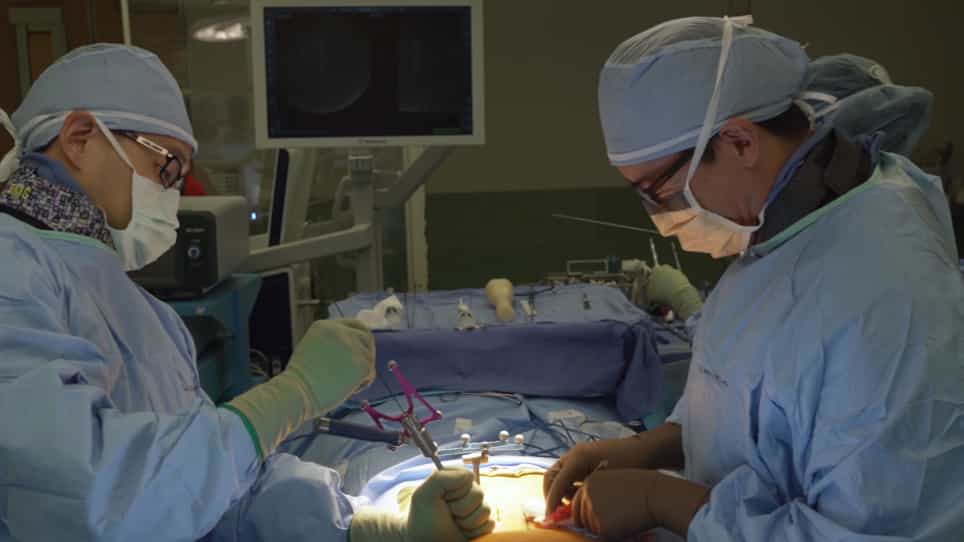

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Spinal versus general anesthesia for minimally invasive transforaminal lumbar interbody fusion: implications on
Gaetano De Biase1, Shaun E Gruenbaum2, James L West1
11Department of Neurosurgery, Mayo Clinic, Jacksonville.

Objective:
There has been increasing interest in the use of spinal anesthesia (SA) for spine surgery, especially within Enhanced Recovery After Surgery (ERAS) protocols. Despite the wide adoption of SA by the orthopedic practices, it has not gained wide acceptance in lumbar spine surgery. Studies investigating SA versus general anesthesia (GA) in lumbar laminectomy and discectomy have found that SA reduces perioperative costs and leads to a reduction in analgesic use, as well as to shorter anesthesia and surgery time. The aim of this retrospective, case-control study was to compare the perioperative outcomes of patients who underwent minimally invasive surgery (MIS)-transforaminal lumbar interbody fusion (TLIF) after administration of SA with those who underwent MIS-TLIF under GA.
Methods:
Overall, 40 consecutive patients who underwent MIS-TLIF by a single surgeon were analyzed; 20 patients received SA and 20 patients received GA. Procedure time, intraoperative adverse events, postoperative adverse events, postoperative length of stay, 3-hour postanesthesia care unit (PACU) numeric rating scale (NRS) pain score, opioid medication, and time to first ambulation were collected for each patient.
Results:
The two groups were homogeneous for clinical characteristics. A decrease in total operating room (OR) time was found for patients who underwent MIS-TLIF after administration of SA, with a mean OR time of 156.5 ± 18.9 minutes versus 213.6 ± 47.4 minutes for patients who underwent MIS-TLIF under GA (p < 0.0001), a reduction of 27%. A decrease in total procedure time was also observed for SA versus GA (122 ± 16.7 minutes vs 175.2 ± 10 minutes; p < 0.0001). No significant differences were found in intraoperative and postoperative adverse events. There was a difference in the mean maximum NRS pain score during the first 3 hours in the PACU as patients who received SA reported a lower pain score compared with those who received GA (4.8 ± 3.5 vs 7.3 ± 2.7; p = 0.018). No significant difference was observed in morphine equivalents received by the two groups. A difference was also observed in the mean overall NRS pain score, with 2.4 ± 2.1 for the SA group versus 4.9 ± 2.3 for the GA group (p = 0.001). Patients who received SA had a shorter time to first ambulation compared with those who received GA (385.8 ± 353.8 minutes vs 855.9 ± 337.4 minutes; p < 0.0001).
Conclusions:
The results of this study have pointed to some important observations in this patient population. SA offers unique advantages in comparison with GA for performing MIS-TLIF, including reduced OR time and postoperative pain, and faster postoperative mobilization.
Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...