Related Experiment Video
Updated: Oct 10, 2025

Guidelines for Elective Pediatric Fiberoptic Intubation
Published on: January 17, 2011
Update on ventilation management in the Pediatric Intensive Care Unit
Chinyere Egbuta1, Ronald Blaine Easley2
1Harvard Medical School, Boston Children's Hospital, Boston, Massachusetts, USA.

Insights
Mechanical ventilation is crucial for pediatric intensive care unit patients with respiratory illness. Advancements focus on noninvasive support, optimizing invasive ventilation, and exploring new strategies, though weaning and complication reduction remain challenges.
Area of Science:
- Pediatric Critical Care Medicine
- Respiratory Physiology
- Mechanical Ventilation
Background:
- Up to 63% of pediatric intensive care unit patients with cardiorespiratory illness require mechanical ventilation.
- Mechanical ventilation management involves initiation, escalation, and resolution phases.
- Noninvasive ventilation, including high-flow nasal cannula, is key in early management.
Purpose of the Study:
- To review advancements in noninvasive and invasive mechanical ventilation for pediatric patients.
- To highlight emerging strategies for optimizing ventilator support and reducing complications.
- To identify areas needing further research in pediatric mechanical ventilation.
Main Methods:
- Review of current literature on pediatric mechanical ventilation strategies.
- Discussion of advancements in noninvasive (high-flow nasal cannula, CPAP, BiPAP) and invasive ventilation.
- Exploration of novel monitoring techniques and nonconventional ventilation modes.
Main Results:
- High-flow nasal cannula is a significant advancement in noninvasive support.
- Optimizing ventilator settings and monitoring (e.g., esophageal pressure, volumetric capnography) improve conventional support.
- Extracorporeal support offers rescue options, while weaning and complication reduction require further research.
Conclusions:
- Significant progress has been made in pediatric mechanical ventilation, particularly in noninvasive support and optimizing invasive techniques.
- Challenges remain in developing reliable weaning strategies and reducing ventilator-induced lung injury.
- Ongoing research is needed to address tracheostomy timing, sedation reduction, and overall patient outcomes.
Abstract:
Studies have shown that up to 63% of pediatric intensive care unit patients admitted with acute respiratory or cardiorespiratory illness require mechanical ventilation. Mechanical ventilator support can be divided into three phases: initiation, escalation, and resolution. Noninvasive ventilation is typical during the initiation phase in the management of acute pediatric respiratory failure. The major advancements in the use of noninvasive ventilation involve the emergence of high-flow nasal cannula and how widespread the use of high-flow nasal cannula has become in pediatric critical care practice. When high-flow nasal cannula fails, escalation to continuous positive airway pressure or bi-level positive airway pressure is the next step in respiratory care progression. Careful clinical assessment is necessary to avoid delayed escalation between forms of noninvasive support or escalation to intubation and invasive mechanical ventilation. Advancements in conventional mechanical ventilation are centered on optimizing ventilator settings and customizing monitoring with the overarching goal to reduce complications of mechanical ventilation, such as ventilator-induced lung injury. New mechanical ventilator strategies integrating esophageal pressure monitoring, volumetric capnography, and neurally adjusted ventilator assist help to optimize conventional ventilator support. Nonconventional modes of ventilation in the intensive care unit are high-frequency modes and airway pressure release ventilation. Extracorporeal pulmonary support via extracorporeal membrane oxygenation or paracorporeal lung assist devices provides rescue options when conventional and nonconventional methods fail. During resolution of a course of mechanical ventilator support, reliable weaning strategies and extubation readiness testing are lacking in pediatric critical care. Further, timing of tracheostomy, risk reduction in ventilator-induced lung injury, and decreased sedation requirements in pediatric patients requiring mechanical ventilation in the pediatric intensive care unit are areas of ongoing research.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:29
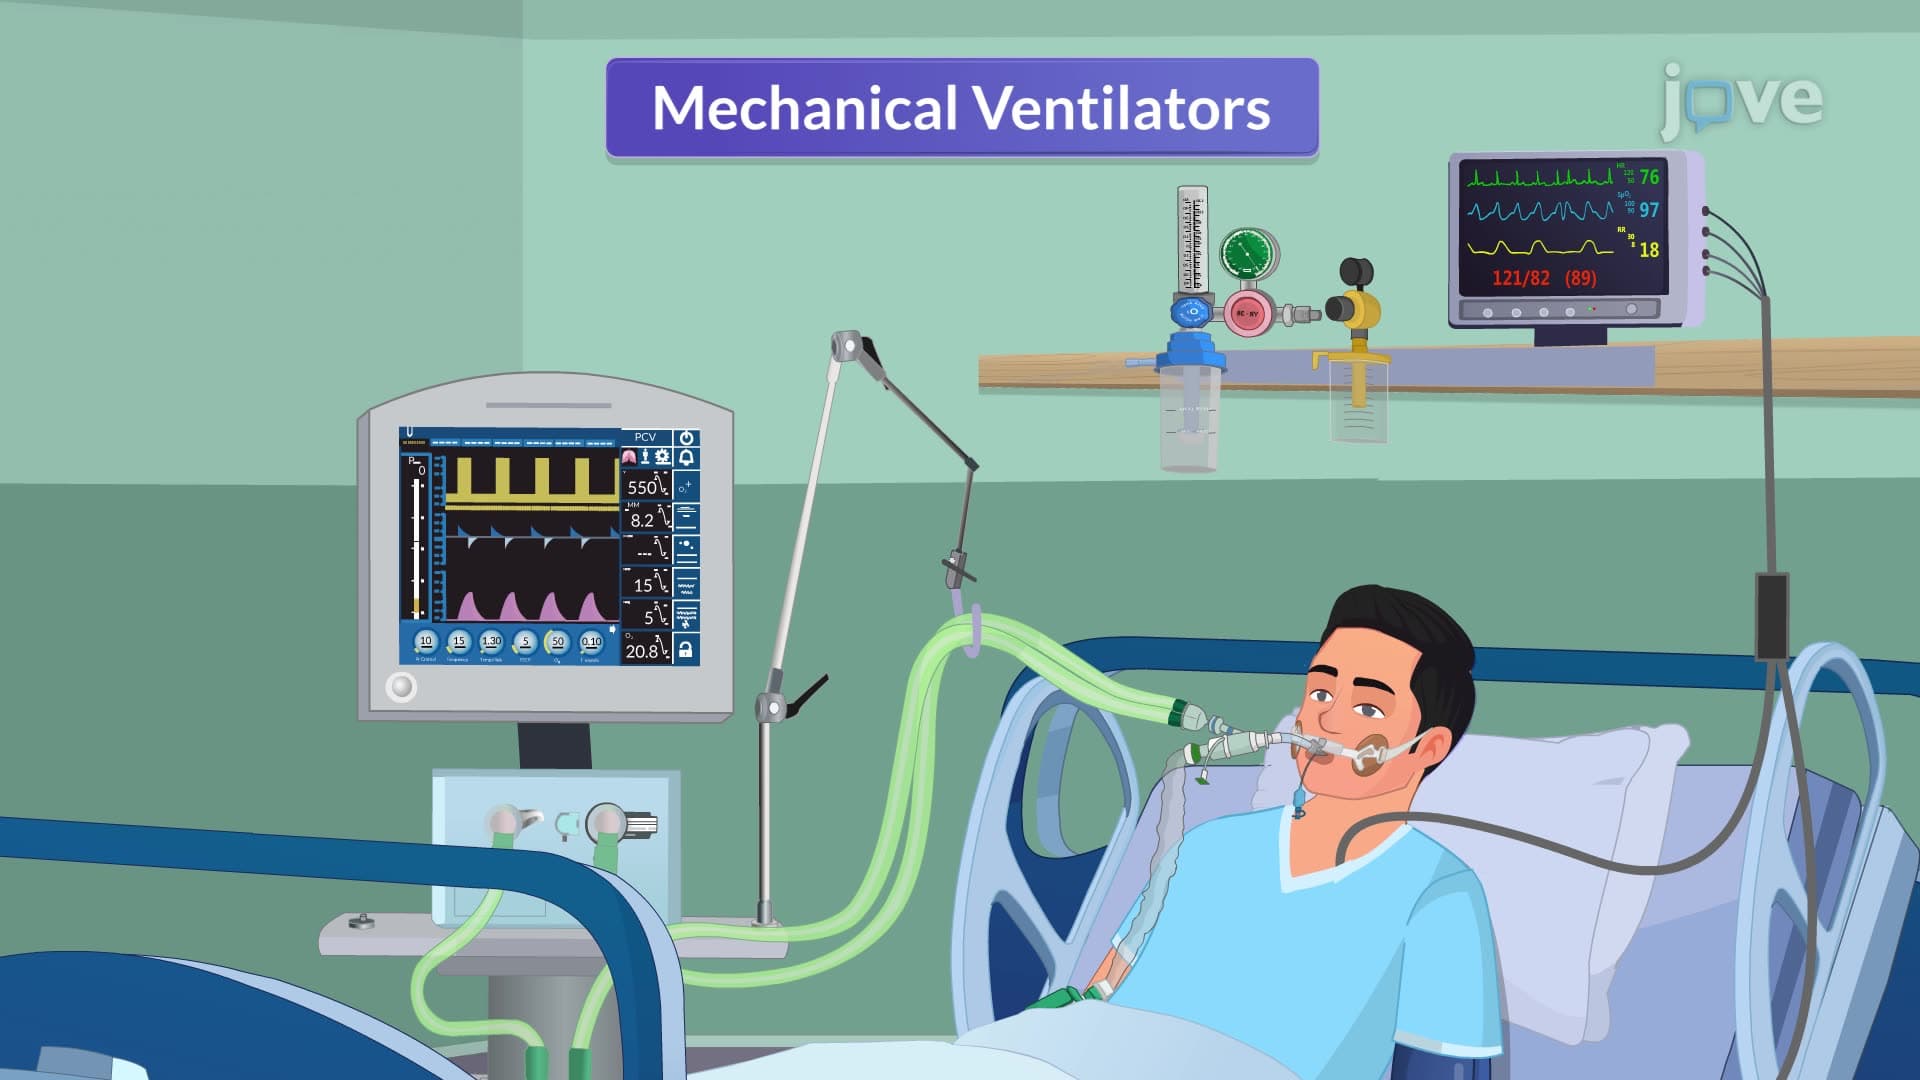
Mechanical Ventilation I: Indication and Settings
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....