Related Experiment Video
Updated: Oct 10, 2025
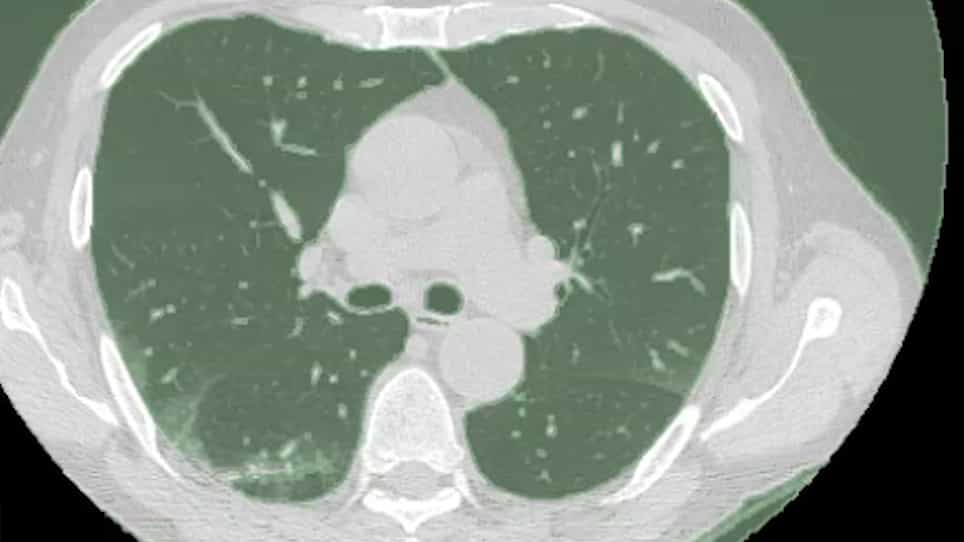

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Diagnostic Accuracy of D-Dimers for Predicting Pulmonary Embolism in COVID-19-Patients
Falmata Laouan Brem1, Boudouh Asmae2, Yassine Amane3
1Department of Cardiology, 470522Mohammed VI University Hospital, Mohammed First University, Oujda, MAR, Morocco.

Insights
A D-dimer cut-off of 2600 ng/mL effectively predicts pulmonary embolism (PE) in COVID-19 patients. This finding aids in guiding computed tomography pulmonary angiography (CTPA) decisions for patients with SARS-CoV-2 infection.
Area of Science:
- Pulmonary Medicine
- Infectious Diseases
- Hematology
Background:
- COVID-19 (Coronavirus disease 2019) is associated with hypercoagulable states and elevated D-dimer levels, even without pulmonary embolism (PE).
- D-dimer levels are a key biomarker in assessing thrombotic risk.
Purpose of the Study:
- To compare D-dimer values in COVID-19 patients with and without PE.
- To establish an optimal D-dimer cut-off value for predicting PE in COVID-19 patients.
- To guide the indication for pulmonary computed tomography angiography (CTPA).
Main Methods:
- Retrospective enrollment of 84 COVID-19 patients suspected of PE undergoing CTPA.
- Comparison of demographic characteristics and blood test results between PE-positive and PE-negative groups.
- Construction of a receiver operating characteristics (ROC) curve to determine the optimal D-dimer cut-off.
Main Results:
- Pulmonary embolism (PE) was diagnosed in 31.9% of COVID-19 patients.
- The median D-dimer level was significantly higher in patients with PE (14,680 ng/mL) compared to those without PE (2,980 ng/mL).
- An optimal D-dimer cut-off of 2600 ng/mL predicted PE with 90.3% sensitivity and an Area Under the Curve (AUC) of 0.773.
Conclusions:
- A D-dimer cut-off value of 2600 ng/mL is a significant predictor of PE in COVID-19 patients.
- This cut-off demonstrates high sensitivity (90.3%) for PE detection.
- The findings support the use of D-dimer levels to refine CTPA indications in COVID-19 patients.
Importance:
Proinflammatory and hypercoagulable states with marked elevation seen in D-Dimer levels have been accurately described in patients infected by the SARS- Cov2 even without pulmonary embolism (PE).
Objectives:
To compare D-dimers values in patients infected by the novel Coronavirus 2019 (COVID-19) with and without PE and to establish an optimal D-dimer cut-off to predict the occurrence of PE, which guides pulmonary computed tomography angiography (CTPA) indication.
Methods:
We retrospectively enrolled all COVID-19-patients admitted between October first and November 22th, 2020, at the University Hospital Center of Mohammed VI, Oujda (Morocco), suspected to have PE and underwent a CTPA. Demographic characteristics and blood test results were compared between PE-positive and PE-negative. The receiver operating characteristics (ROC) curve was constructed to establish an optimal D-Dimer cut-off to predict the occurrence of PE.
Results:
The study population consisted of 84 confirmed COVID-19-patients. The mean age was 64.93 years (SD 14.19). PE was diagnosed on CTPA in 31 (36.9%) patients. Clinical symptoms and in-hospital outcomes were similar in both groups except that more men had PE (p = .025). The median value of D-dimers in the group of patients with PE was significantly higher (14 680[IQR 33620-3450]ng/mL compared to the group of patients without PE 2980[IQR 6870-1600]ng/mL [P < .001]. A D-dimer at 2600 ng/mL was the optimal cut-off for predicting PE with a sensitivity of 90.3%, and AUC was .773[CI 95%, .667 -.876).
Conclusion:
A D-dimer cut-off value of 2600 ng/mL is a significant predictor of PE in COVID-19-patients with a sensitivity of 90.3%.

Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:27
Pulmonary Embolism III: Nursing Management
 01:29
Pulmonary Embolism I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History