The Biomechanical Consequences of Arthroscopic Hip Capsulotomy and Repair in Positions at Risk for Dislocation
Amanda Wach1, Ryan Mlynarek2, Suzanne A Maher1
1Department of Biomechanics, Hospital for Special Surgery, New York, New York, USA.

Background:
The effect of interportal (IP) capsulotomy, short T-capsulotomy, and long T-capsulotomy, and their repairs, on resistance to anterior and posterior "at risk for dislocation" positions has not been quantified.
Hypotheses:
Our primary hypothesis was that an IP capsulotomy would have a minimal effect on hip resistive torque compared with both short and long T-capsulotomies in the at-risk dislocation positions. Our secondary hypothesis was that capsule repair would significantly increase hip resistive torque for all capsulotomies.
Study Design:
Controlled laboratory study.
Methods:
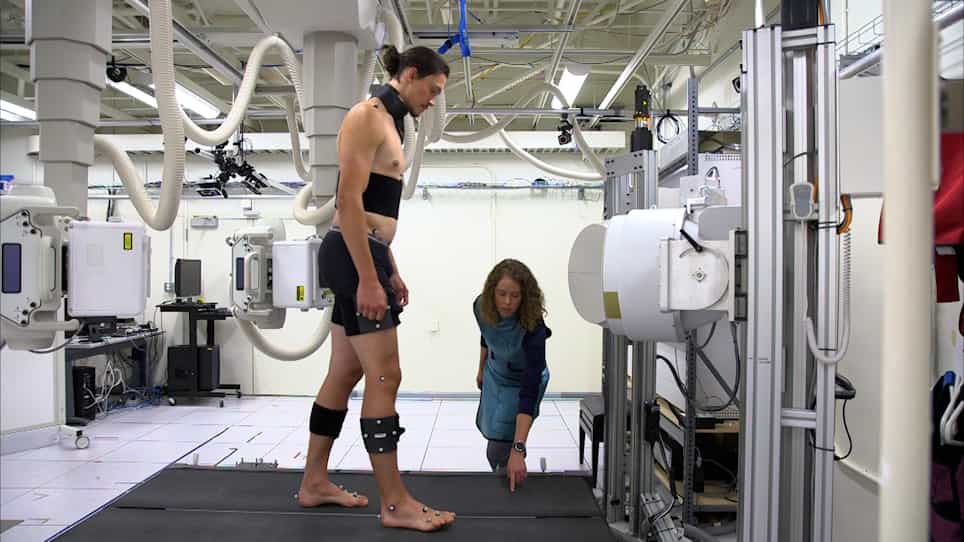
We mounted 10 cadaveric hips on a biaxial test frame in an anterior dislocation high-risk position (20° of hip extension and external rotation) and posterior dislocation high-risk position (90° of hip flexion and internal rotation). An axial force of 100 N was applied to the intact hip while the femur was internally or externally rotated at 15° per second to a torque of 5 N·m. The rotatory position at 5 N·m was recorded and set as a target for each subsequent condition. Hips were then sequentially tested with IP, short T-, and long T-capsulotomies and with corresponding repairs randomized within each condition. Peak resistive torques were compared using generalized estimating equation modeling and post hoc Bonferroni-adjusted tests.
Results:
For the anterior position, the IP and long T-capsulotomies demonstrated significantly lower resistive torques compared with intact. For the posterior position, both the short and long T-capsulotomies resulted in significantly lower resistive torques compared with intact. Repairs for all 3 capsulotomy types were not significantly different from the intact condition at anterior and posterior positions.
Conclusion:
An IP incision resulted in a decrease in capsular resistive torque in the anterior but not the posterior at-risk dislocation position, in which direction only T-capsulotomies led to a significant decrease. All capsulotomy repair conditions resulted in hip resistive torques that were similar to the intact hip in both dislocation positions.
Clinical Relevance:
Our results suggest that it is biomechanically advantageous to repair IP, short T-, and long T-capsulotomies, particularly for at-risk anterior dislocation positions.