Related Experiment Video
Updated: Oct 6, 2025

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Tympanic membrane perforations: the importance of etiology, size and location
L Castelhano1, F Correia2, T Colaço2
1Serviço de Otorrinolaringologia, Hospital de Egas Moniz, Centro Hospitalar de Lisboa Ocidental, Rua da Junqueira 126, 1349-019, Lisboa, Portugal. lmgcastelhano@gmail.com.

Purpose:
The ability to predict the degree of a conductive hearing loss caused by a tympanic membrane perforation is important for every otologist, as it may require additional diagnostic tests and prevent unexpected intraoperative findings. The aim of this study was to correlate the various characteristics of a perforation (etiology, size, location, involvement of the manubrium or umbo) with the degree and frequency predominance of the consequent hearing loss.
Methods:
A transversal study in a tertiary hospital center was conducted between July 2019 and December 2020. Fifty-eight patients with 65 tympanic perforations underwent a comprehensive medical and audiological evaluation, which included an otoendoscopy. An image processing software (ImageJ®) was used to measure the perforated area. The qualitative variables were etiology, affected quadrants, presence of myringosclerosis and involvement of umbo or manubrium of the malleus. The air-bone gap was measured at 250, 500, 1000, 2000 and 4000 Hz. Primary outcomes (mean air-bone gap and pure-tone average) were evaluated to find clinical factors associated with worse hearing.
Results:
Data collected from 50 ears was included. Perforation size showed a positive statistically significant correlation with the air-bone gap (r = .508; p < .001) and pure-tone average (r = .375; p < .001). Higher air-bone gaps were found in perforations involving the posterior quadrants and the manubrium (p < .001 and p = .031, respectively). Inflammatory causes showed higher bone and air conduction pure-tone averages (p = .031 and p = .084, respectively) compared to traumatic or iatrogenic. An "inverted V" pattern of the air-bone gap, with the 2 kHz frequency being the least affected, was a consistent finding. However, it was not due to the Carhart's notch in bone conduction.
Conclusion:
The conductive hearing loss resulting from a tympanic membrane perforation is etiology, size and location-dependent, with higher losses occurring for inflammatory backgrounds, large perforations and when the posterior quadrants or the manubrium are involved. If the "inverted V" is absent, additional middle ear pathology should be investigated.
Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:16
Anatomy of the Ear
 01:21
Perceiving Loudness, Pitch, and Location
Place theory, or place coding, suggests that different pitches are heard because various sound waves activate specific locations along the cochlea's basilar membrane. The brain determines the pitch of a sound by...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:14
Assessing Body Temperature - Tympanic membrane
Step 1: Begin by practicing good hand hygiene to prevent the transmission of microorganisms.
Step 2: Turn on the thermometer and wait until the ready sign appears on the screen to ensure accurate measurement.
Step 3: Slide the probe cover in place to prevent cross-contamination.
Step 4: Instruct the patient to tilt their head to the side for comfort and check for cerumen...
 01:11
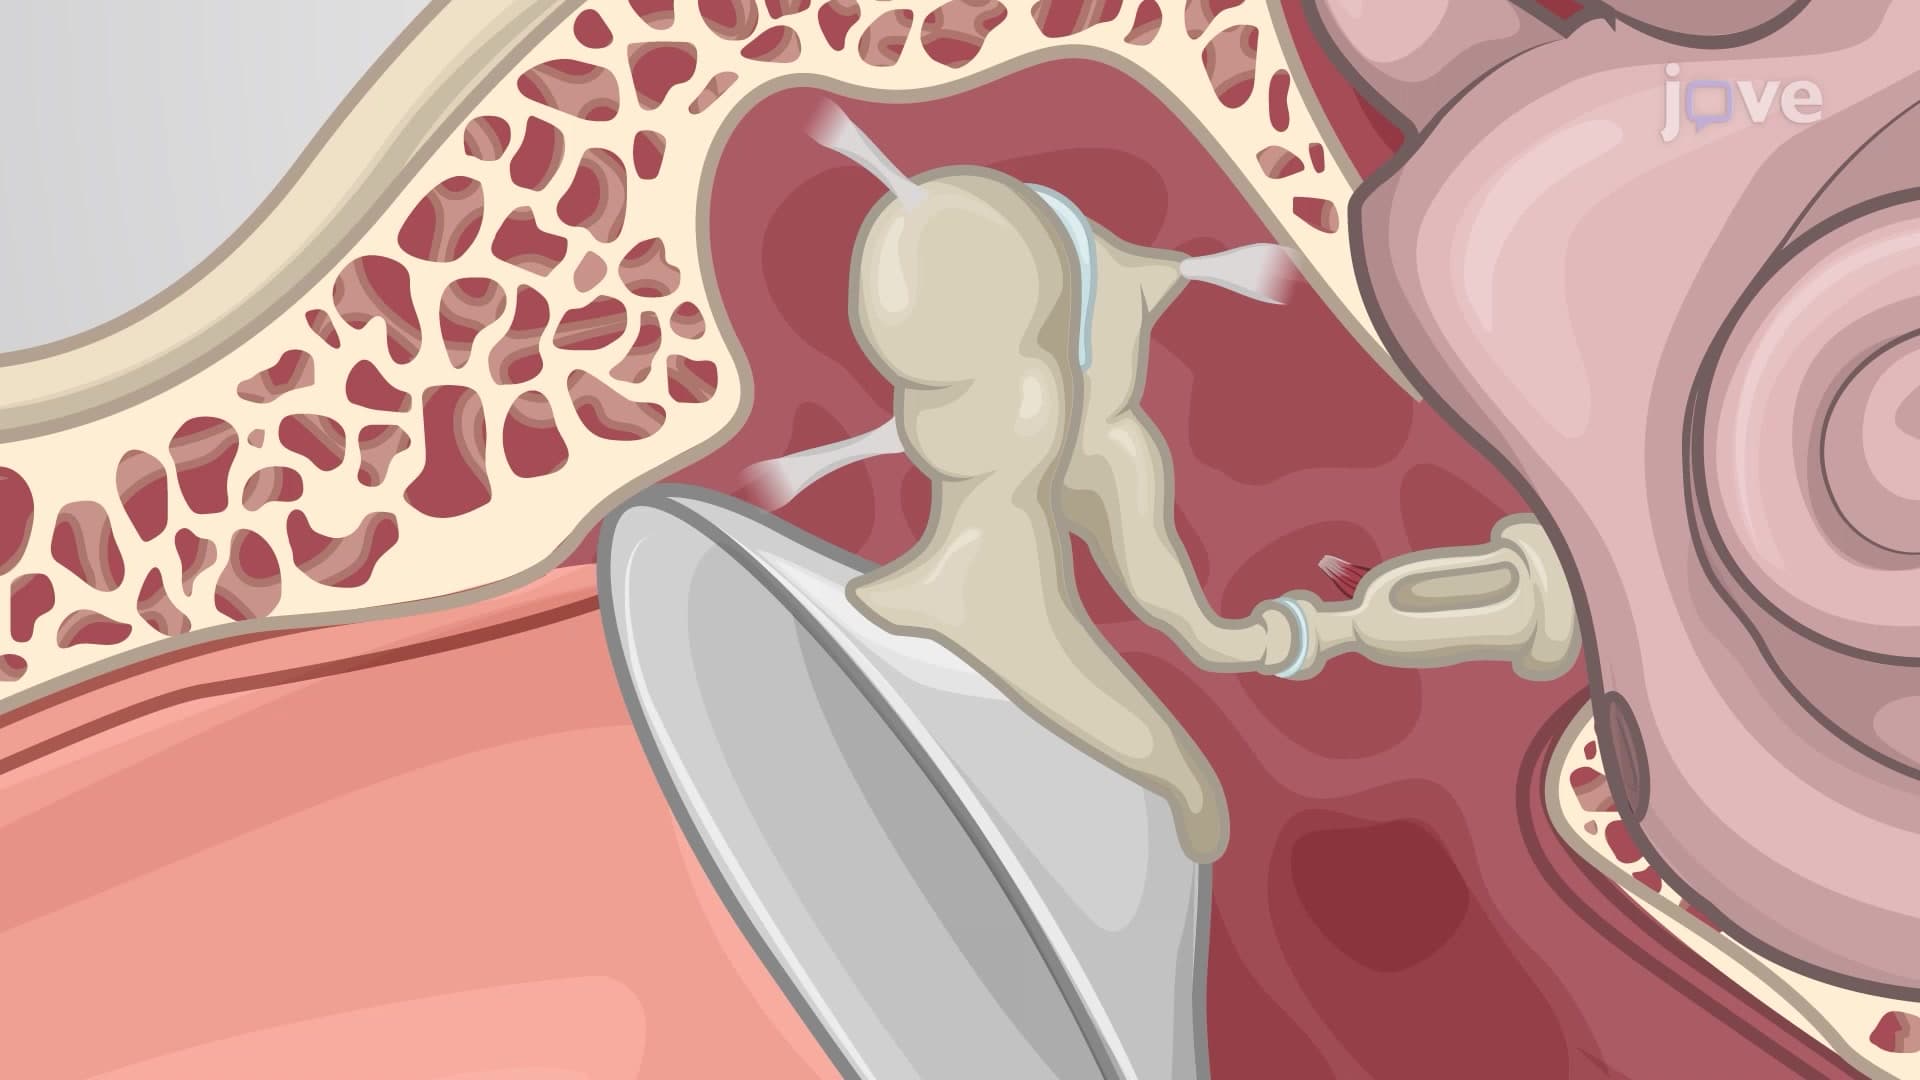
The Auditory Ossicles
The aptly named stapes look very much like a stirrup. The three ossicles are unique to mammals, and each plays a role in...