Related Experiment Video
Updated: Oct 6, 2025
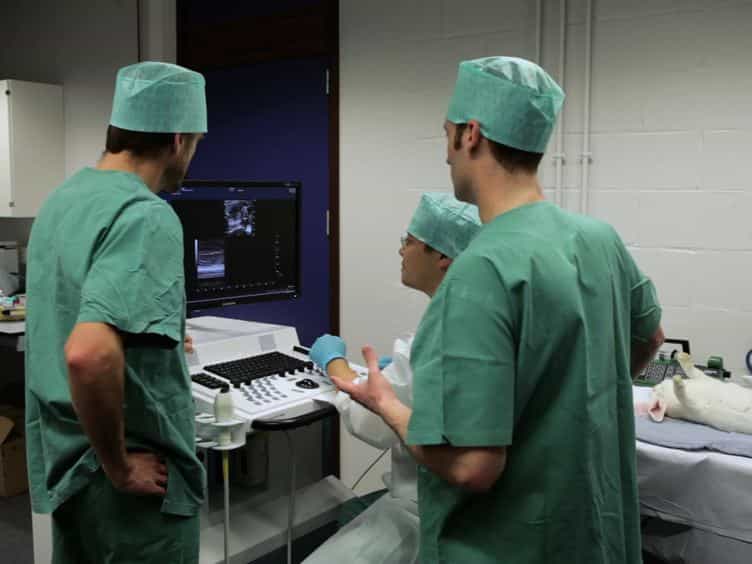
Fetal Echocardiography and Pulsed-wave Doppler Ultrasound in a Rabbit Model of Intrauterine Growth Restriction
Published on: June 29, 2013
Arterial health during early childhood following abnormal fetal growth
Rasmus F W Olander1,2, Johnny K M Sundholm3,4, Sanna Suonsyrjä3,4
1Children's Hospital, Pediatric Research Center, University of Helsinki, and Helsinki University Hospital, Stenbäckinkatu 9, POB 347, FIN-00029, Helsinki, Finland. rasmus.olander@helsinki.fi.

Insights
Childhood arterial health is linked to current body composition, not fetal growth patterns. Studies found no evidence of fetal programming affecting cardiovascular risk or arterial health in early childhood.
Area of Science:
- Pediatric cardiology
- Developmental biology
- Vascular health
Background:
- Abnormal fetal growth, including small for gestational age (SGA) and large for gestational age (LGA) births, is linked to adult cardiovascular disease.
- Understanding the long-term impact of fetal growth on childhood arterial health is crucial for early risk assessment.
Purpose of the Study:
- To investigate the influence of fetal programming on arterial health and morphology in early childhood.
- To determine if birth weight categories (SGA, LGA, appropriate for gestational age - AGA) affect childhood arterial structure and stiffness.
Main Methods:
- Examined 90 children (median age 5.81 years) categorized by birth weight: SGA (N=23), LGA (N=19), and AGA (N=48).
- Measured body composition, anthropometrics, blood pressure, pulse wave velocity (PWV), lipids, glucose, and inflammatory markers.
- Assessed arterial morphology (lumen diameter, intima-media thickness, adventitia thickness) and stiffness (PWV) of major arteries using high-resolution ultrasound.
Main Results:
- LGA children had increased anthropometry and lean body mass; SGA children had decreased anthropometry and lean body mass.
- No significant group differences were observed in blood pressure, PWV, carotid artery stiffness, or blood work.
- Differences in arterial dimensions and wall thicknesses were explained by current lean body mass and sex, not birth weight category. Birth weight was only associated with carotid and brachial lumen dimensions.
Conclusions:
- Childhood arterial dimensions are primarily associated with current anthropometrics, particularly lean body mass and sex.
- No evidence of fetal programming impacting cardiovascular risk or arterial health was found in early childhood.
- Adiposity did not independently predict arterial dimensions in this cohort.
Background:
Abnormal fetal growth is associated with increased cardiovascular risk in adulthood. We investigated the effect of fetal programming on arterial health and morphology during early childhood.
Methods:
We examined 90 children (median age 5.81 years, interquartile range: 5.67; 5.95), born small for gestational age with fetal growth restriction, large or appropriate for gestational age (SGA, N = 23, LGA, N = 19, AGA N = 48). We measured body composition, anthropometrics, blood pressure, pulse wave velocity (PWV), lipids, glucose and inflammatory markers, and assessed carotid, brachial, radial and femoral arterial morphology and stiffness using very-high resolution ultrasound (46-71 MHz).
Results:
LGA showed increased anthropometry, lean body mass and body mass index. SGA displayed decreased anthropometry and lean body mass. Blood pressure, PWV, carotid artery stiffness and blood work did not differ groupwise. Differences in lumen diameters, intima-media thicknesses (IMT) and adventitia thicknesses disappeared when adjusted for lean body mass and sex. In multiple regression models arterial dimensions were mainly predicted by lean body mass, with birth weight remaining associated only with carotid and brachial lumen dimensions, and not with IMTs. Carotid-femoral PWV was predicted by height and blood pressure only. No independent effect of adiposity was observed.
Conclusions:
Arterial dimensions in childhood associate with current anthropometrics, especially lean body mass, and sex, explaining differences in arterial layer thickness. We found no signs of fetal programming of cardiovascular risk or arterial health in early childhood.

Related Concept Videos
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:07
Development of Blood Vessels
The initial formation of this system is facilitated by the small amount of yolk present in the ovum and yolk sac. Blood vessels originate from...
 01:29
Cardiovascular System Abnormal Findings I: Inspection and Palpation
Abnormal findings observed during an inspection
 01:27
Signs of Puberty
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...