Related Experiment Video
Updated: Oct 6, 2025


A Clinical Trial Assessing the Safety, Efficacy, and Delivery of Olive-Oil-Based Three-Chamber Bags for Parenteral Nutrition
Published on: September 20, 2019
Body Composition of Preterm Infants following Rapid Transition to Enteral Feeding
Cornelia Wiechers1, Vanessa Avellina1, Beate Luger1
1Department of Neonatology, University Children's Hospital, Eberhard Karls University, Tübingen, Germany.

Insights
Body composition in very preterm infants fed rapidly was similar to other preterm groups. Fat-free mass was lower in infants small for gestational age, indicating potential growth differences.
Area of Science:
- Neonatology
- Pediatric Nutrition
- Body Composition Analysis
Background:
- Very preterm infants often face challenges with enteral feeding.
- Rapid transition to full enteral feeding is a strategy to improve outcomes.
- Body composition changes in preterm infants require careful monitoring.
Purpose of the Study:
- To evaluate body composition at hospital discharge in very preterm infants.
- To assess the impact of rapid enteral feeding transition on body composition.
- To compare body composition metrics with gestational age and growth parameters.
Main Methods:
- Prospective, observational, cross-sectional study.
- Included 105 preterm infants (<32 weeks gestational age or <1,500g birth weight).
- Measured fat mass/total body mass (BF%) and fat-free mass (FFM) using air displacement plethysmography at discharge.
Main Results:
- At discharge (37.6 weeks postmenstrual age), BF% was 17.0% and FFM was 2,161g.
- BF% was not associated with gestational age at birth.
- Fat-free mass was significantly lower in infants born small for gestational age.
Conclusions:
- Rapid enteral feeding transition resulted in body composition similar to other preterm populations.
- Body composition was associated with postmenstrual age, not gestational age at birth.
- Preterm infants showed lower fat-free mass and higher fat mass compared to term infants, suggesting diminished growth.
Objective:
This study aimed to evaluate body composition at the time of hospital discharge in very preterm infants following rapid transition to full enteral feeding.
Study Design:
We conducted a prospective, observational, cross-sectional study and included 105 preterm infants <32 gestational age or birth weight <1,500 g, born between April 2015 and December 2020, following rapid transition to full enteral feeding (≥140 mL/kg/day). Fat mass/total body mass (BF%) and fat-free mass (FFM) were measured at the time of hospital discharge using air displacement plethysmography.
Results:
Median and interquartile range (Q1-Q3) of gestational age at birth (GA) was 27.3 (26.1-28.7) weeks and birth weight 845 (687-990) g. Time to reach full enteral feeding was 5 (5-7) days. At 37.6 weeks (36.1-39.0) postmenstrual age (PMA), BF% was 17.0% (14.9-19.8) and FFM 2,161 g (1,966-2,432). BF% was not associated with GA, and not different between small and appropriate for gestational age infants. FFM was significantly lower in infants born small for gestational age.
Conclusions:
Following rapid transition to full enteral feeding, FFM and BF% at discharge were similar to other preterm populations. BF% and FFM were not associated with GA at birth but with PMA at measurement. FFM was lower and BF% higher compared to term infants at birth, suggesting diminished parenchymal growth in preterm infants. Continued monitoring of body composition, metabolic health, and neurological development is needed to study long-term effects.
More Related Videos
 09:36
Effect of Hyaluronic Acid 35 kDa on an In Vitro Model of Preterm Small Intestinal Injury and Healing Using Enteroid-Derived Monolayers
Published on: July 28, 2022
 11:36
A RAPID Method for Blood Processing to Increase the Yield of Plasma Peptide Levels in Human Blood
Published on: April 28, 2016
Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:23
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:18
Metabolic States of the Body: The Postabsorptive State
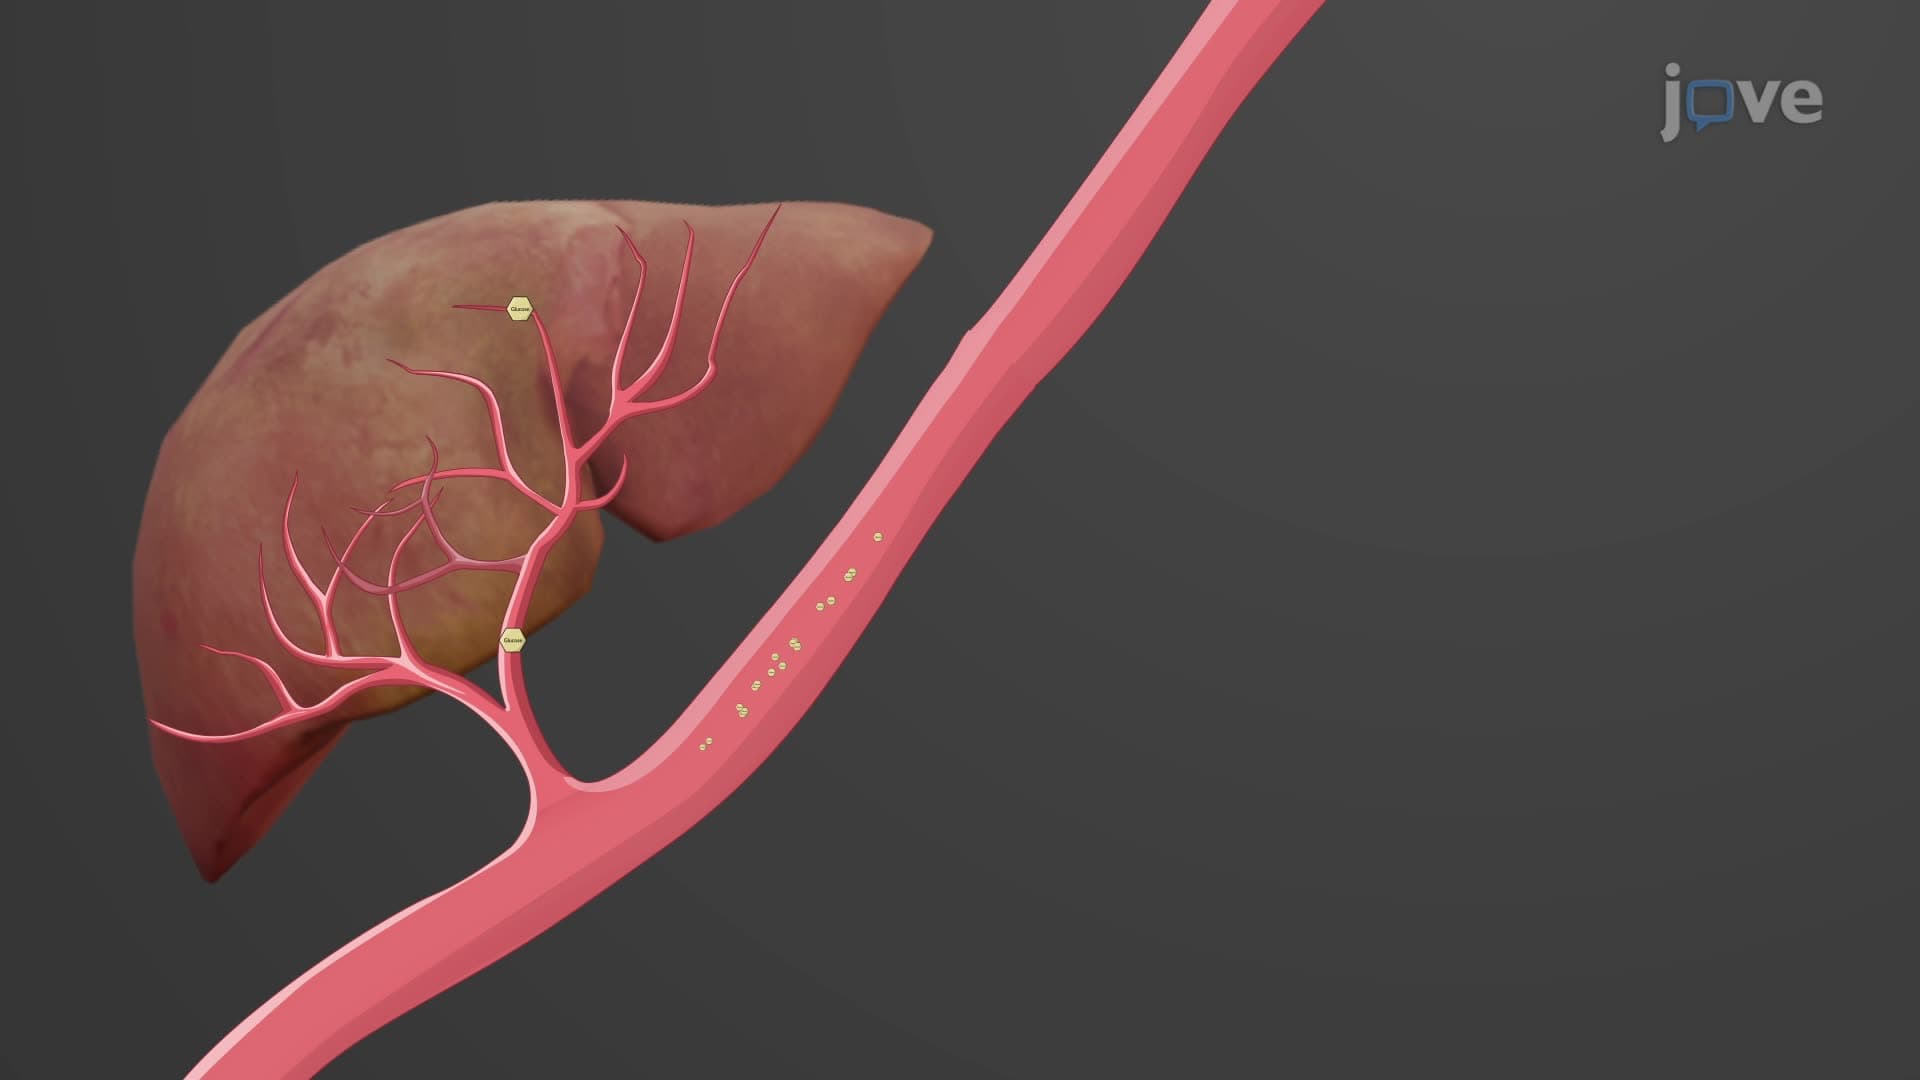
Initially, glycogen stored in the liver is broken down to release glucose into the bloodstream, while glycogen in the muscles is broken down to supply glucose for energy directly within the muscle cells. As glycogen stores diminish,...