Related Experiment Video
Updated: Oct 4, 2025

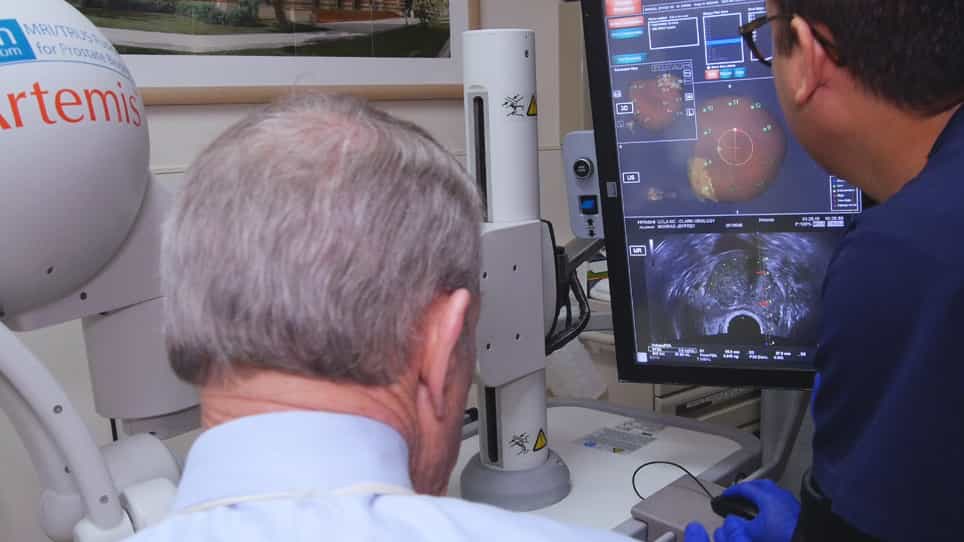
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
SUVmax/ADC Ratio as a Molecular Imaging Biomarker for Diagnosis of Biopsy-Naïve Primary Prostate Cancer
Sheela Chinnappan1, Piyush Chandra2, John Santa Kumar2
1Department of Radiodiagnosis, Sri Ramchandra Institute of Higher Education and Research, Chennai, Tamil Nadu, India.

Background:
Gallium-68-prostate-specific membrane antigen (68Ga-PSMA) positron emission tomography/computed tomography (PET/CT) has recently been shown to be very high accuracy in biopsy-naïve prostate cancer (PCa) detection and can potentially improve the low specificity noted with diffusion-weighted magnetic resonance imaging (DW-MRI), especially in instances of prostate inflammation. We aimed to compare the diagnostic accuracy of DW-MRI and PSMA PET/CT using apparent diffusion coefficient (ADC) and maximum standardized uptake (SUVmax) values in the diagnosis of PCa.
Patients And Methods:
A retrospective study comparing and analyzing the diagnostic accuracy of prebiopsy DW-MRI and 68Ga-PSMA PET/CTs done in patients with suspected PCa (raised prostate specific antigen [PSA] and/or positive digital rectal examination) from January 2019 to December 2020. The standard of reference was transrectal ultrasound-guided biopsies.
Results:
Sixty-seven patients were included in the study, mean age: 70 years (range 49-84), mean PSA: 23.2 ng/ml (range 2.97-45.6). Biopsy was positive for PCa in 56% (n = 38) and negative in 43% (n = 29). Of the benign results, benign hyperplasia was noted in 75% (n = 22) and prostatitis in 25% (n = 7). Of the PCa, 55% (n = 21) of were high International Society of Urological Pathology (ISUP) grade (4-5) and 45% (n = 17) low/intermediate ISUP grade (1-3). Overall the sensitivity/specificity/Accuracy for prediction of PCa of MRI using prostate imaging and reporting data system version 2 criteria and PSMA PET/CT using PCa molecular imaging standardized evaluation criteria was 92.1%/65.5%/80.5% and 76.3%/96.5%/85.1% respectively. Mean apparent diffusion co-efficient (mean ADC) value of benign lesions and PCa was 1.135 × 10⁻³ mm2/s and 0.723 × 10⁻³ mm2/s, respectively (P = 0.00001). Mean SUVmax and ADC of benign and PCa lesions was 4.01 and 16.4 (P = 0.000246). Mean SUVmax/ADC ratio of benign and malignant lesions was 3.8 × 10³ versus 25.21 × 10³ (P < 0.000026). Inverse correlation was noted between ADC and SUVmax values (R = -0.609), inverse correlation noted between ADC and Gleason's score (R = -0.198), and positive correlation of SUVmax and SUVmax/ADC with Gleason's score (R = 0.438 and R = 0.448). Receiver operating characteristic curve analysis revealed a SUVmax cutoff 6.03 (sensitivity/specificity - 76%/90%, area under the curve (AUC) - 0.935, Youden index (YI) - 0.66), ADC cutoff of 0.817 × 10⁻³ mm2/s (sensitivity/specificity - 79%/86%, AUC - 0.890, YI - 0.65), and SUVmax/ADC ratio cutoff of 7.43 × 10³ (sensitivity/specificity - 87%/98%, AUC - 0.966, YI - 0.85) for PCa diagnosis.
Conclusion:
For diagnosis of biopsy-naïve PCas, the combination of diffusion-weighted MRI and PSMA PET/CT (i.e., SUVmax/ADC ratio) shows better diagnostic accuracy than either used alone and the combination of PET and MRI is especially useful when distinguishing cancer from prostatitis.