Related Experiment Video
Updated: Oct 3, 2025
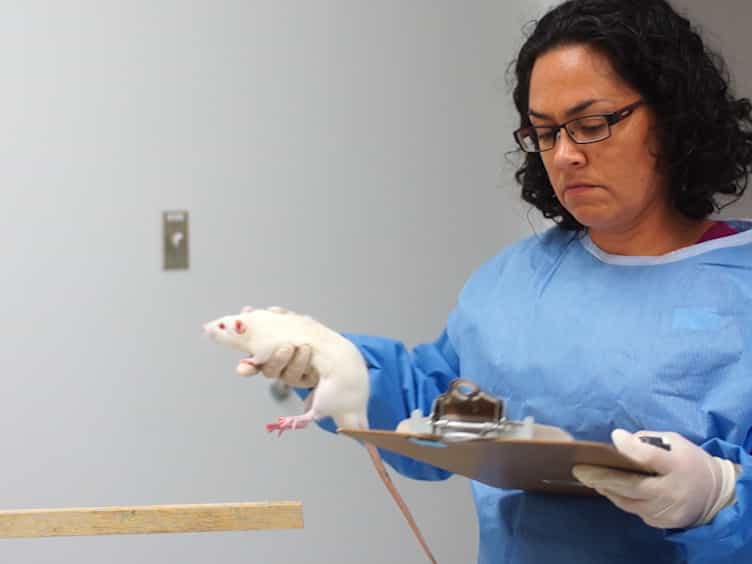

Detecting Behavioral Deficits in Rats After Traumatic Brain Injury
Published on: January 30, 2018
Cognitive Outcome 1 Year After Mild Traumatic Brain Injury: Results From the TRACK-TBI Study
Andrea L C Schneider1, J Russell Huie1, W John Boscardin1
1From the Department of Neurology (A.L.C.S., R.D.-A.), University of Pennsylvania Perelman School of Medicine, Philadelphia; Departments of Neurosurgery (J.R.H., A.R.F., G.T.M.), Epidemiology and Biostatistics (W.J.B., K.Y.), Neurology (K.Y., J.K., R.C.G.), Psychiatry (K.Y.), and Radiology and Biomedical Imaging (E.Y.), University of California San Francisco; Department of Neurosurgery (L.N.), Medical College of Wisconsin, Madison; Departments of Neurological Surgery (J.K.B., N.T.) and Biostatistics (N.T.), University of Washington, Seattle; and Biostatistics Research Center (S.J.), Herbert Wertheim School of Public Health and Human Longevity Science, University of California San Diego, La Jolla.

Background And Objectives:
The objectives of this study were to develop and establish concurrent validity of a clinically relevant definition of poor cognitive outcome 1 year after mild traumatic brain injury (mTBI), to compare baseline characteristics across cognitive outcome groups, and to determine whether poor 1-year cognitive outcome can be predicted by routinely available baseline clinical variables.
Methods:
Prospective cohort study included 656 participants ≥17 years of age presenting to level 1 trauma centers within 24 hours of mTBI (Glasgow Coma Scale score 13-15) and 156 demographically similar healthy controls enrolled in the Transforming Research and Clinical Knowledge in TBI (TRACK-TBI) study. Poor 1-year cognitive outcome was defined as cognitive impairment (below the ninth percentile of normative data on ≥2 cognitive tests), cognitive decline (change score [1-year score minus best 2-week or 6-month score] exceeding the 90% reliable change index on ≥2 cognitive tests), or both. Associations of poor 1-year cognitive outcome with 1-year neurobehavioral outcomes were performed to establish concurrent validity. Baseline characteristics were compared across cognitive outcome groups, and backward elimination logistic regression was used to build a prediction model.
Results:
Mean age of participants with mTBI was 40.2 years; 36.6% were female; 76.6% were White. Poor 1-year cognitive outcome was associated with worse 1-year functional outcome, more neurobehavioral symptoms, greater psychological distress, and lower satisfaction with life (all p < 0.05), establishing concurrent validity. At 1 year, 13.5% of participants with mTBI had a poor cognitive outcome vs 4.5% of controls (p = 0.003). In univariable analyses, poor 1-year cognitive outcome was associated with non-White race, lower education, lower income, lack of health insurance, hyperglycemia, preinjury depression, and greater injury severity (all p < 0.05). The final multivariable prediction model included education, health insurance, preinjury depression, hyperglycemia, and Rotterdam CT score ≥3 and achieved an area under the curve of 0.69 (95% CI 0.62-0.75) for the prediction of a poor 1-year cognitive outcome, with each variable associated with >2-fold increased odds of poor 1-year cognitive outcome.
Discussion:
Poor 1-year cognitive outcome is common, affecting 13.5% of patients with mTBI vs 4.5% of controls. These results highlight the need for better understanding of mechanisms underlying poor cognitive outcome after mTBI to inform interventions to optimize cognitive recovery.

