Related Experiment Video For brachial plexopathy
Updated: Oct 2, 2025
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
The spectrum of brachial plexopathy from perineural spread of breast cancer
Megan M Jack1, Brandon W Smith1, Stepan Capek2
11Department of Neurological Surgery, Mayo Clinic, Rochester, Minnesota.

Objective:
Perineural spread of breast cancer to the brachial plexus can lead to pain, sensory alterations, and upper-extremity weakness. Although rare, perineural spread is an often-misdiagnosed long-term complication following breast cancer diagnosis. The objective of this study was to critically review the clinical, radiological, and pathological findings of biopsy-proven perineural spread of breast cancer to the brachial plexus.
Methods:
This is a retrospective study from a single institution in which a total of 19 patients with brachial plexus involvement from perineural spread of breast cancer who underwent fascicular biopsy between 1999 and 2021 were identified. Clinical, radiographic, and pathological data were retrospectively collected. Descriptive statistics were calculated for the cohort.
Results:
The mean age of patients at the time of diagnosis of breast cancer perineural spread was 60.6 ± 11.5 years. The diagnosis of brachial plexopathy due to perineural spread was on average 12 years after the primary diagnosis of breast cancer. There was also a delay in diagnosis due to the rarity of this disease, with a mean time from initial symptom onset to diagnosis of perineural spread of 25 ± 30 months. All patients at the time of presentation had upper-extremity weakness and pain. Nearly all patients demonstrated T2 signal change and nodular so-called sugar-coating contrast enhancement on brachial plexus MRI. Similarly, all patients who underwent PET/MRI or PET/CT had increased FDG uptake in the involved brachial plexus. Breast cancer perineural spread has an overall poor prognosis, with 16 of 19 patients dying within 5.9 ± 3.0 years after diagnosis of perineural spread.
Conclusions:
Perineural spread should be considered in patients with a history of breast cancer, even 10 years after primary diagnosis, especially in patients who present with arm pain, weakness, and/or sensory changes. Further diagnostic workup with electrodiagnostic studies; brachial plexus MRI, PET/CT, or PET/MRI; and possibly nerve biopsy is warranted to ensure accurate diagnosis.
More Related Videos
 08:57
Author Spotlight: Genetically Engineered Mouse Models and Pathological Characterization of Neurofibromatosis Type 1 Associated Tumors
Published on: May 17, 2024
 06:03
Integrating Augmented Reality Tools in Breast Cancer Related Lymphedema Prognostication and Diagnosis
Published on: February 6, 2020
Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:21
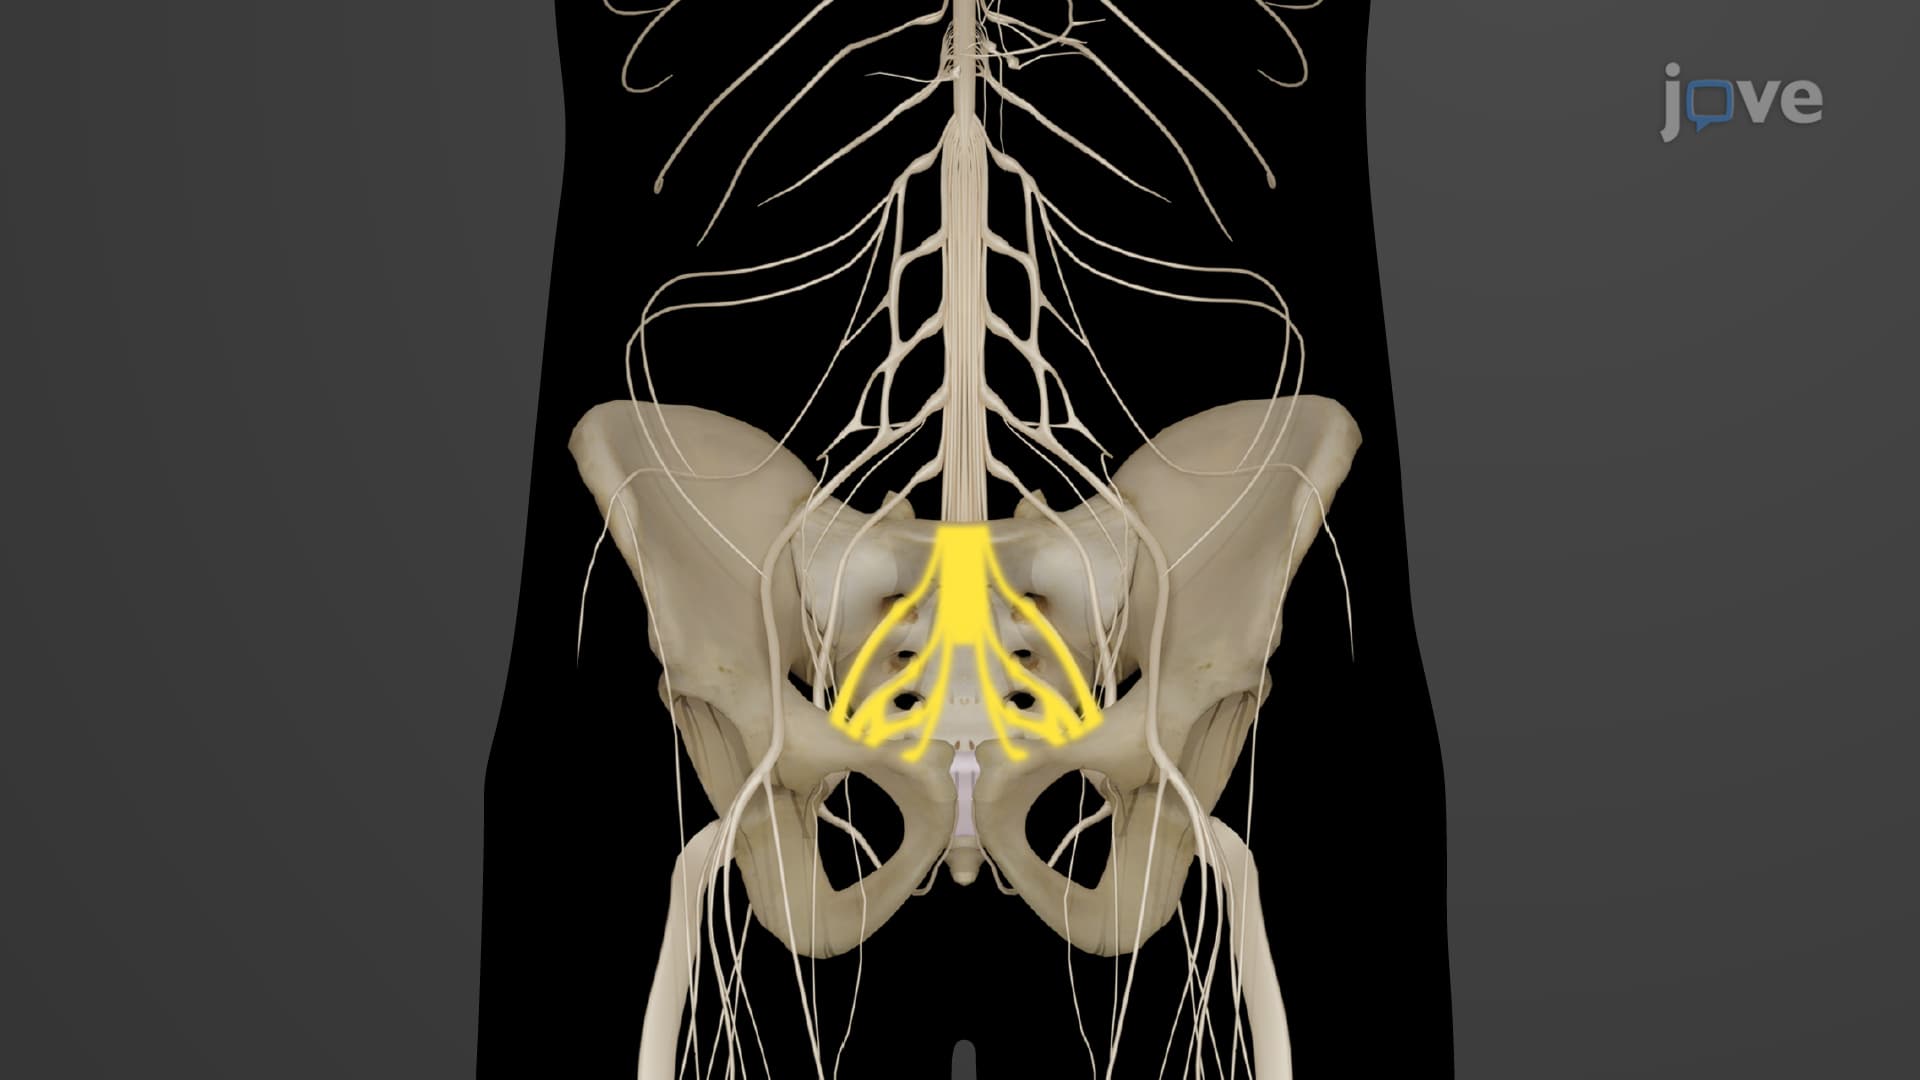
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 02:07
Tumor Progression
Colon cancer is one of the best-documented examples of tumor progression. Early mutation in the APC gene in colon cells causes a small growth on the colon wall called a polyp. With time, this polyp grows into a benign, pre-cancerous tumor. Further...
 01:24
Disorders of the Female Reproductive System