[Surgery for a Massive Left Atrial Myxoma, Four Hours after a Thrombectomy for a Cerebral Embolism:Report of a Case]
Related Experiment Video
Updated: Oct 1, 2025

Comprehensive Endovascular and Open Surgical Management of Cerebral Arteriovenous Malformations
Published on: October 20, 2017
Naoto Fukunaga1, Tatsuto Wakami, Akio Shimoji
1Department of Cardiovascular Surgery, Hyogo Prefectural Amagasaki General Medical Center, Amagasaki, Japan.

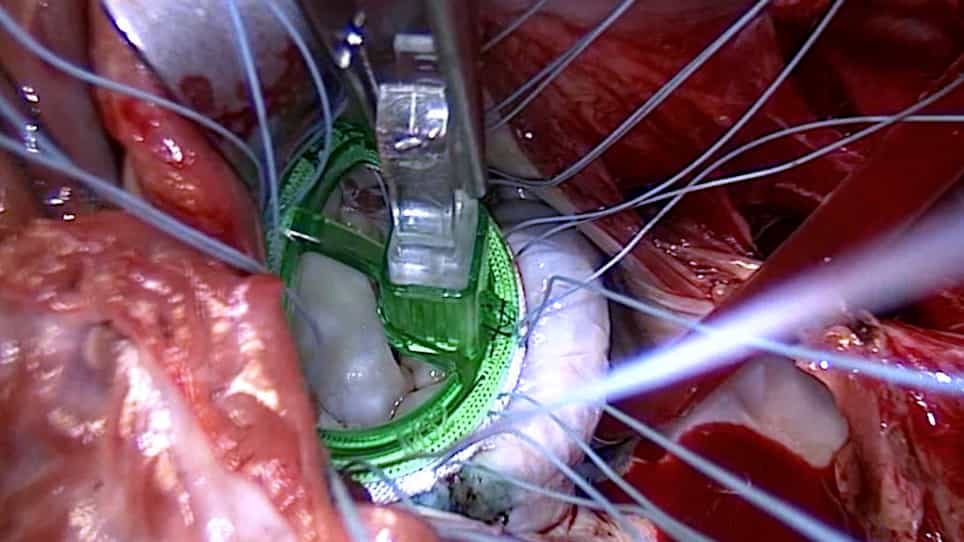
A 48-year-old female patient was transferred with dysarthria and left-sided hemiplegia. Contrast-enhanced computed tomography revealed occlusion of the first branch of the right middle cerebral artery, for which an emergency thrombectomy was successfully performed within 2 hours of patient's initial symptoms. Postoperatively, transthoracic echocardiography revealed a massive mobile left atrial mass, measuring approximately 65×30 mm, a part of which moved in and out of the mitral valve without significant mitral regurgitation. Embolisms to the kidneys and the spleen were demonstrated. Another emergency cardiac surgery was performed, 4 hours after the thrombectomy, to resect the mass from the fossa oval with the atrial septum;the defect was closed using autologous pericardium. The histopathological findings of the specimen were consistent with a myxoma. The patient completely recovered and was discharged when ambulatory. We have discussed the importance of the timing of surgical intervention in the context of patients undergoing cardiac surgery after a cerebral embolism.
A 48-year-old female patient was transferred with dysarthria and left-sided hemiplegia. Contrast-enhanced computed tomography revealed occlusion of the first branch of the right middle cerebral artery, for which an emergency thrombectomy was successfully performed within 2 hours of patient's initial symptoms. Postoperatively, transthoracic echocardiography revealed a massive mobile left atrial mass, measuring approximately 65×30 mm, a part of which moved in and out of the mitral valve without significant mitral regurgitation. Embolisms to the kidneys and the spleen were demonstrated. Another emergency cardiac surgery was performed, 4 hours after the thrombectomy, to resect the mass from the fossa oval with the atrial septum;the defect was closed using autologous pericardium. The histopathological findings of the specimen were consistent with a myxoma. The patient completely recovered and was discharged when ambulatory. We have discussed the importance of the timing of surgical intervention in the context of patients undergoing cardiac surgery after a cerebral embolism.
More Related Videos

Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management