Related Experiment Video
Updated: Sep 29, 2025
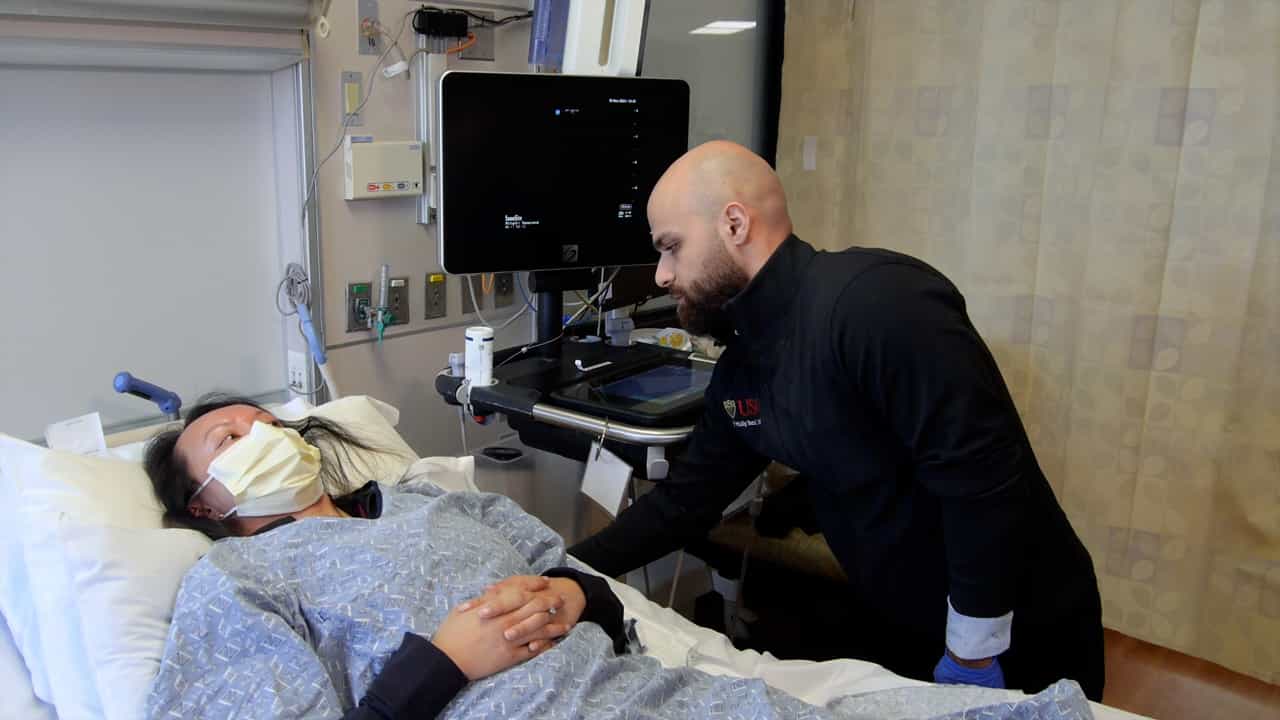

Point of Care Transcranial Color-Coded Duplex Ultrasound of the Middle Cerebral Artery
Published on: August 9, 2024
Significant venous flow alterations following brain arteriovenous malformation Surgery: Assessment by transcranial
Kathryn Busch1, Andrew Davidson2, Antonio Di Ieva3
1Macquarie Medical School, Faculty of Medicine, Health and Human Sciences, Level 3, 75 Talavera Rd, Macquarie University, Sydney, NSW 2109, Australia.

Abstract:
Brain arteriovenous malformation (bAVM) resection imposes several post-operative clinical challenges including intracranial haemorrhage (ICH). Daily non-invasive monitoring of haemodynamic measurements may be useful in predicting post-operative ICH. This prospective study used transcranial colour duplex (TCCD) and central aortic pressure (CAP) measurements to evaluate 15 bAVM patients pre-operatively and daily ≤ 14 days post-operatively. TCCD measurements of middle cerebral artery and veins included peak systolic (PSV), end diastolic (EDV), and pulsatility indices (PI). Parameters were compared with 7 craniotomy patients (non-bAVM craniotomy/surgical group). Normal reference values included 20 healthy volunteers. Significant middle cerebral vein MCV changes in bAVM patients occurred; Maximal PSV was significantly higher (median 47 cm/s) compared to non-bAVM craniotomy/surgical controls (median 17 cm/s, p = 0.0123); maximal PI was significantly higher (median 0.99, p = 0.005) compared to the non-bAVM craniotomy/surgical controls (median 0.49). In 8 of 15 patients, increased MCV velocity and pulsatility "stabilised" within 14 days post-operatively. Mean number of days for the 8 patients to reach stable state was 5.9 days, (range 0-9 days). To our knowledge, this is the first imaging study demonstrating significant venous changes post bAVM resection. Significant increased venous flow occurs in pial veins bilaterally. Increased pressure of venous flow is evidenced by a significant increase in diameter and pulsatility. Subsequently, haemorrhagic complications may be due distal constriction of the pial veins causing venous hypertension. The cause of the dilated vascular bed is unknown.