Predictive value of the stress hyperglycemia ratio in patients with acute ST-segment elevation myocardial infarction: insights from a multi-center observational study

Wei Xu1,2, Yan-Min Yang3,4, Jun Zhu1,2
1Emergency Center, National Center for Cardiovascular Disease, Fuwai Hospital, Chinese Academy of Medical Sciences and Peking Union Medical College, No. 167 Beilishi Road, Xicheng District, Beijing, People's Republic of China.

Background:
Stress hyperglycemia is a strong predictor of adverse outcomes in patients with acute myocardial infarction (AMI). Recently, the stress hyperglycemia ratio (SHR) has been designed as an index to identify acute hyperglycemia with true risk; however, data regarding the impact of SHR on the prognosis of ST-segment elevation myocardial infarction (STEMI) remains limited. This study aimed to evaluate the predictive value of the SHR in patients with acute STEMI and to assess whether it can improve the predictive efficiency of the Thrombolysis in Myocardial Infarction (TIMI) risk score.
Methods:
This study included 7476 consecutive patients diagnosed with acute STEMI across 274 emergency centers. After excluding 2052 patients due to incomplete data, 5417 patients were included in the final analysis. Patients were divided into three groups according to SHR tertiles (SHR1, SHR2, and SHR3) and were further categorized based on diabetes status. All patients were followed up for major cardiovascular adverse events (MACEs) and all-cause mortality.
Results:
After 30 days of follow-up, 1547 MACEs (28.6%) and 789 all-cause deaths (14.6%) occurred. The incidence of MACEs was highest among patients in the SHR3 group with diabetes mellitus (DM) (42.6%). Kaplan-Meier curves demonstrated that patients with SHR3 and DM also had the highest risk for MACEs when compared with other groups (p < 0.001). Moreover, C-statistics improved significantly when SHR3 was added into the original model: the ΔC-statistics (95% confidence interval) were 0.008 (0.000-0.013) in the total population, 0.010 (0.003-0.017) in the DM group, and 0.007 (0.002-0.013) in the non-DM group (all p < 0.05). In the receiver operating characteristic analysis, the area under the curve (AUC) for the original TIMI risk score for all-cause death was 0.760. When an SHR3 value of 1 point was used to replace the history of DM, hypertension, or angina in the original TIMI risk score, the Delong test revealed significant improvements in the AUC value (∆AUC of 0.009, p < 0.05), especially in the DM group (∆AUC of 0.010, p < 0.05).
Conclusion:
The current results suggest that SHR is independently related to the risks of MACEs and mortality in patients with STEMI. Furthermore, SHR may aid in improving the predictive efficiency of the TIMI risk score in patients with STEMI, especially those with DM.
More Related Videos
 09:35
A Mouse Model of Hemorrhagic Transformation Induced by Acute Hyperglycemia Combined with Transient Focal Ischemia
Published on: November 15, 2024
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:26
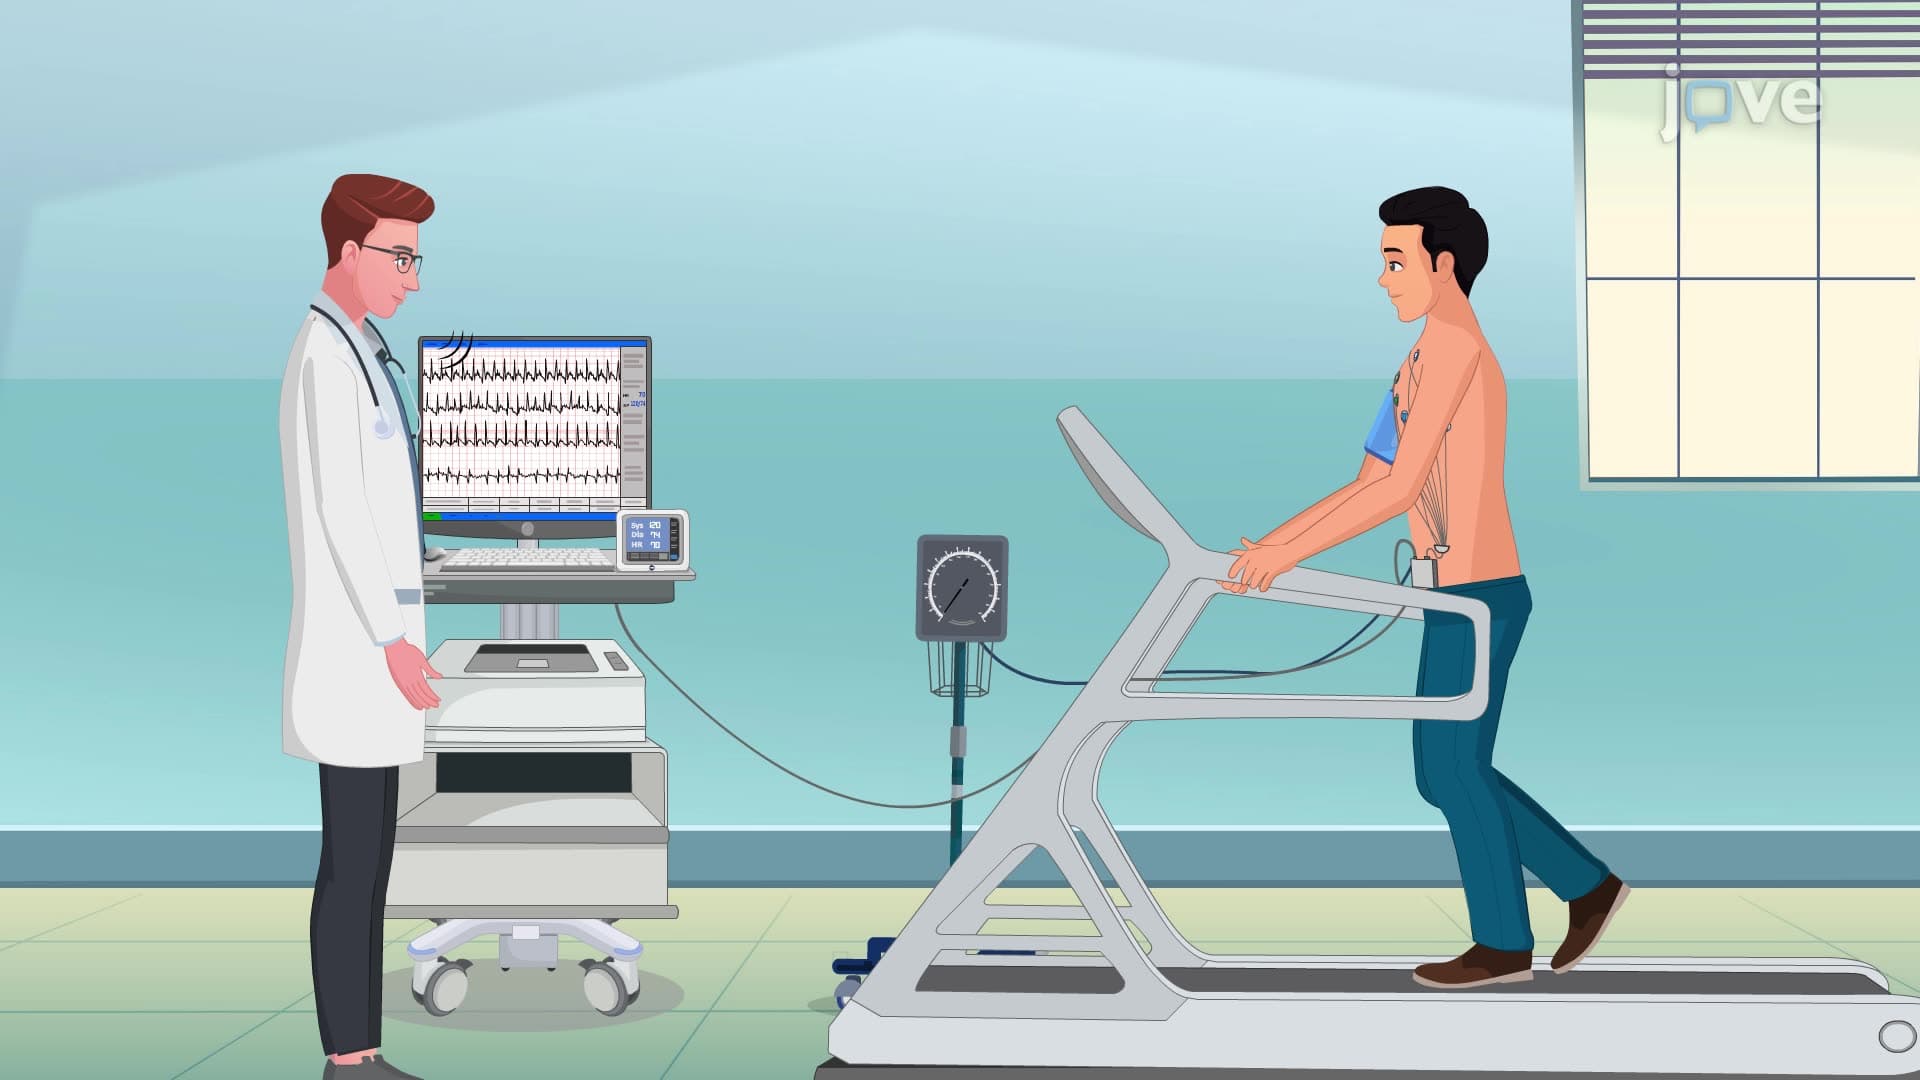
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:19
Psychoneuroimmunology: Diabetes and Cancer
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...