Related Experiment Video
Updated: Sep 28, 2025


Cutoff Value of Phase Angle by Bioelectrical Impedance Analysis at Admission as a Prognostic Factor in Patients with Acute Heart Failure
Published on: June 10, 2025
Obesity, Anion Accumulation, and Anion Gap Metabolic Acidosis: A Cohort Study
Douglas C Lambert1,2, Matthew K Abramowitz3,4,5,6
1Department of General Internal Medicine, Northwell Health, Great Neck, New York.

Background:
Obesity is associated with low serum bicarbonate, an indicator of metabolic acidosis and a CKD risk factor. To further characterize acid-base disturbance and subclinical metabolic acidosis in this population, we examined prospective associations of body mass index (BMI) with elevated anion gap and whether anion gap values in obesity associate with low bicarbonate.
Methods:
Data from adult outpatients (n=94,448) in the Bronx, New York were collected from 2010 to 2018. Mixed effects models and Cox proportional hazards models were used to examine associations of BMI with elevated anion gap and anion gap metabolic acidosis and of baseline anion gap with incident low bicarbonate and anion gap metabolic acidosis. Anion gap was defined using traditional and albumin-corrected calculations.
Results:
Greater BMI was associated with higher anion gap over time and with progressively greater risk of developing an elevated anion gap (hazard ratio [HR] for body mass index [BMI]≥40 kg/m2 versus 18 to <25 kg/m2, 1.32; 95% confidence interval [95% CI], 1.23 to 1.42 for traditional and HR for BMI≥40 kg/m2 versus 18 to <25 kg/m2, 1.74; 95% CI, 1.63 to 1.85 for corrected). Higher BMI was also associated with increased risk of developing anion gap metabolic acidosis (HR for BMI≥40 kg/m2, 1.53; 95% CI, 1.39 to 1.69). Among patients with obesity, higher anion gap was associated with increased risk of incident low bicarbonate (HR for fourth versus first quartile, 1.29; 95% CI, 1.23 to 1.44 for traditional and HR for fourth versus first quartile, 1.36; 95% CI, 1.26 to 1.48 for corrected) and higher risk of anion gap metabolic acidosis (HR for fourth versus first quartile, 1.78; 95% CI, 1.59 to 1.99).
Conclusions:
Obesity is characterized by unmeasured anion accumulation and acid retention or overproduction. Modest elevations in anion gap among patients with obesity are associated with previously unrecognized anion gap metabolic acidosis.
More Related Videos
 06:28
A Chronic High-Intensity Interval Training and Diet-Induced Obesity Model to Maximize Exercise Effort and Induce Physiologic Changes in Rats
Published on: April 28, 2023
 08:30
Intraperitoneal Glucose Tolerance Test, Measurement of Lung Function, and Fixation of the Lung to Study the Impact of Obesity and Impaired Metabolism on Pulmonary Outcomes
Published on: March 15, 2018
Related Concept Videos
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:29
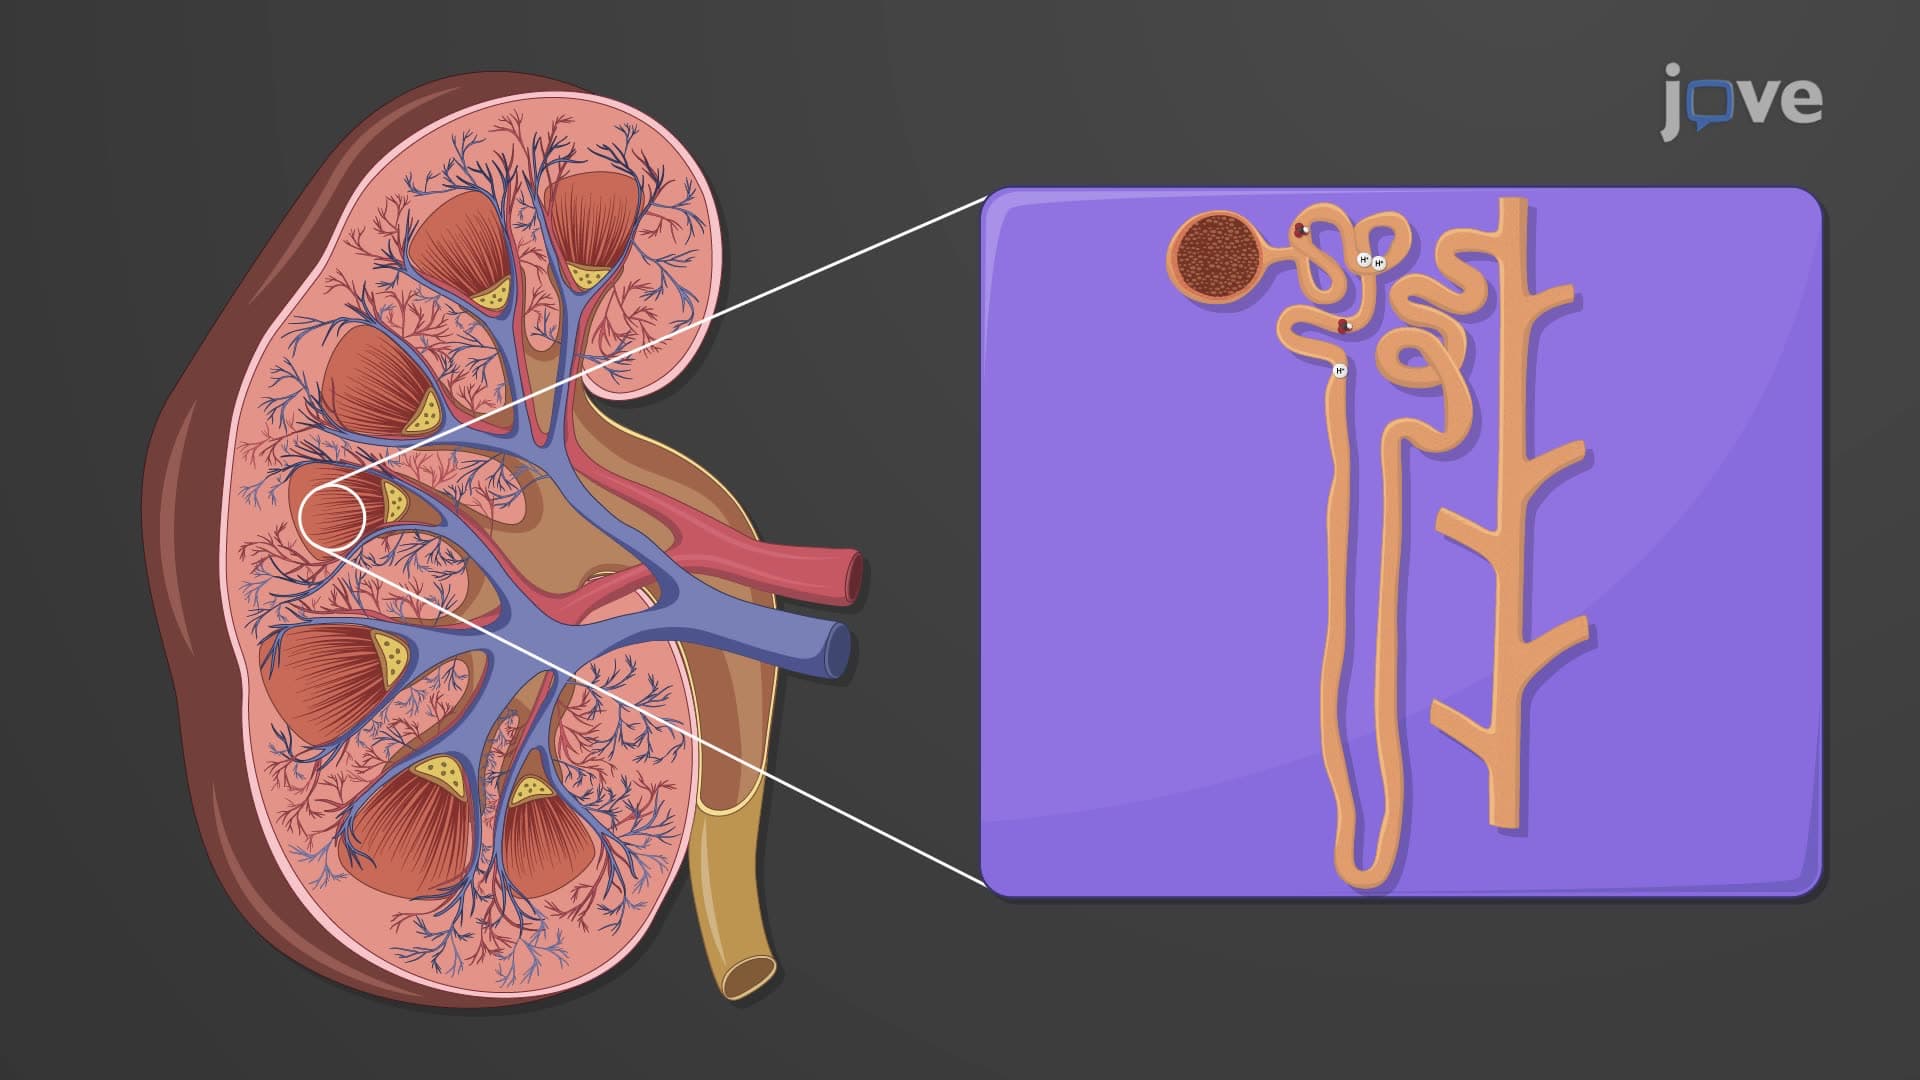
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:29
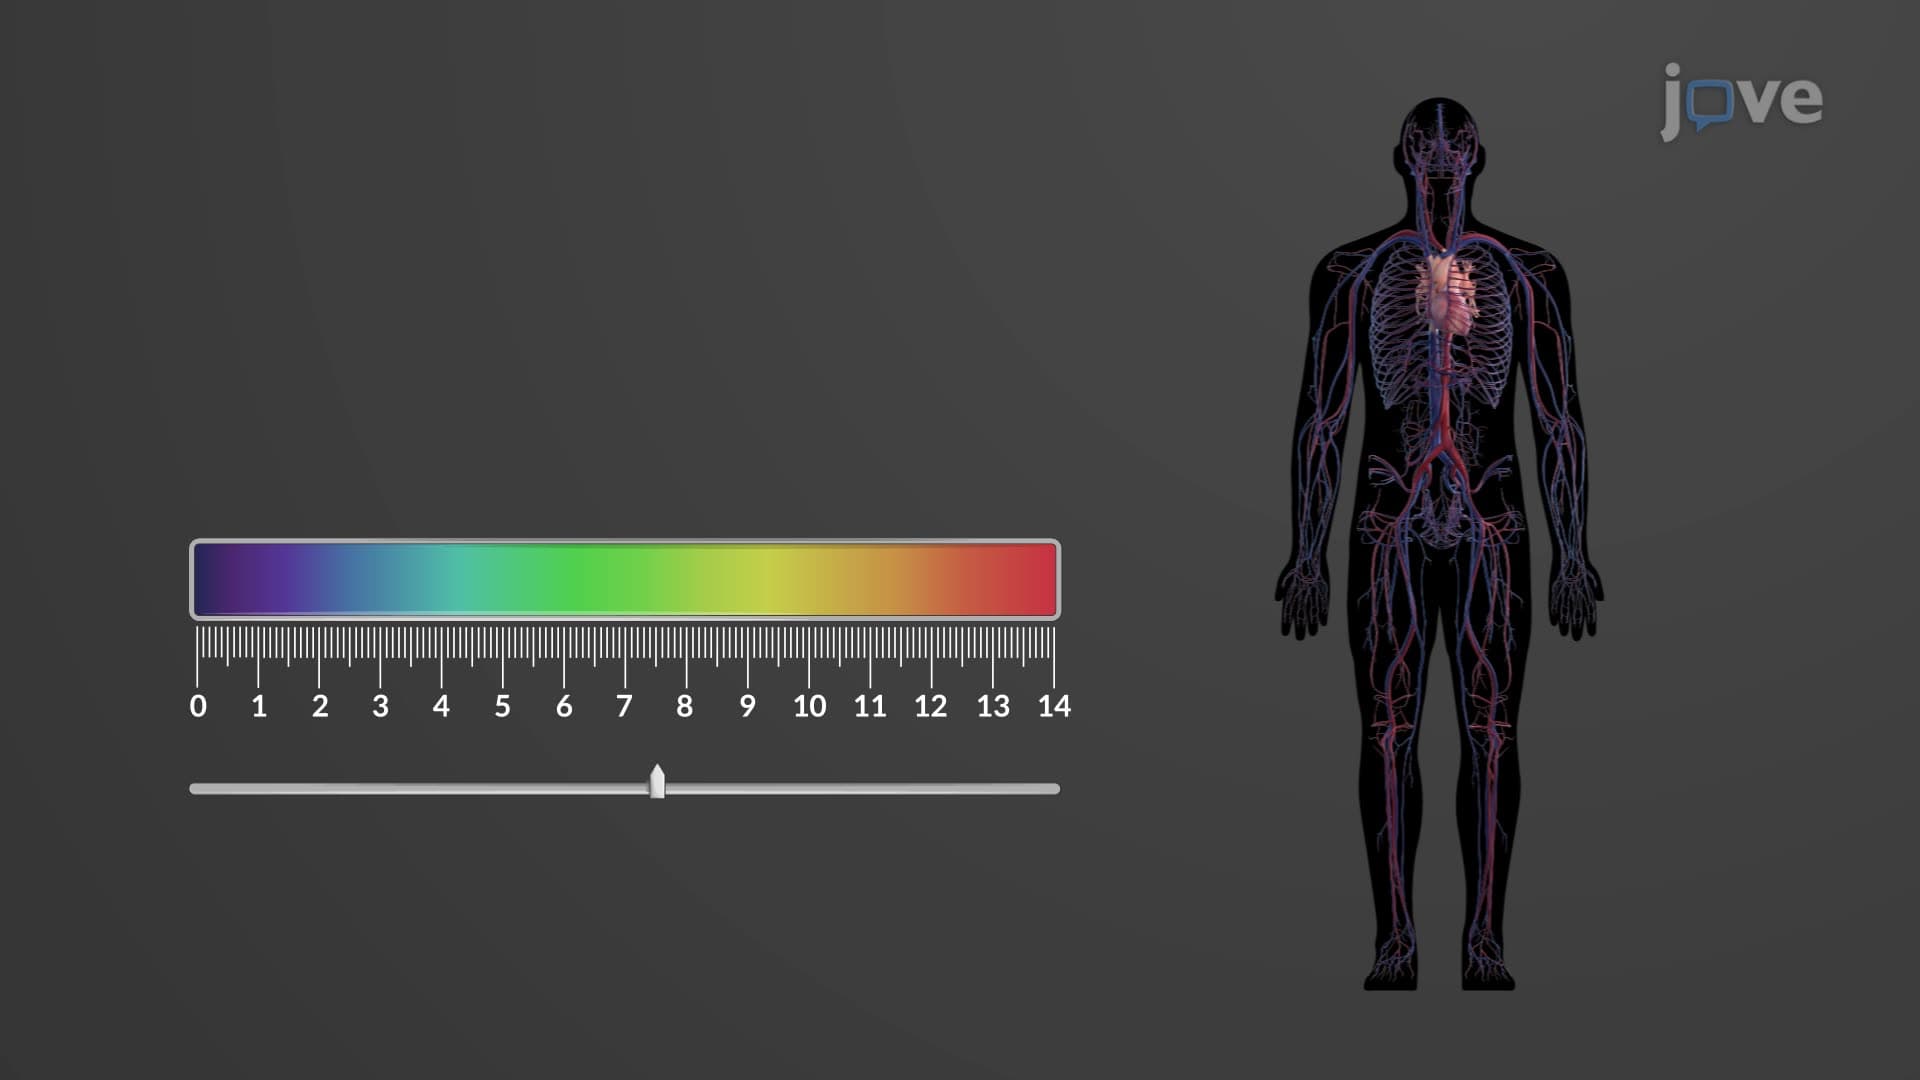
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are...
 01:24
Obesity
 01:29
Acute Kidney Injury III: Clinical Manifestations