Related Experiment Video
Updated: Sep 27, 2025
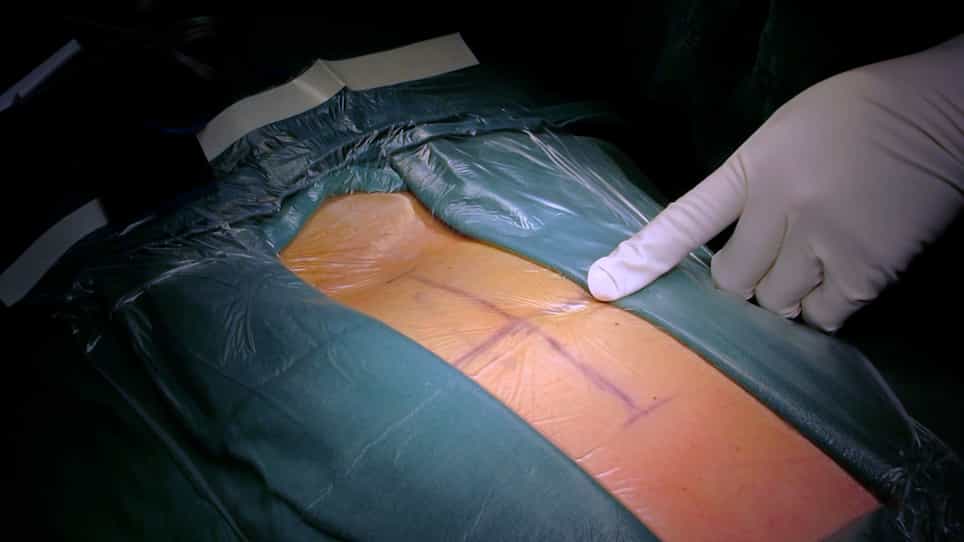
Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
In Scheuermann's kyphosis, a proximal UIV and postop kyphosis value close to patients' PI decreases the risk of PJK
Vishal Sarwahi1, Sayyida Hasan2, Jesse Galina2
1Department of Pediatric Orthopaedics, Cohen Children's Medical Center, Lake Success, NY, USA. Vsarwahi@northwell.edu.

Purpose:
Prevalence of proximal junctional kyphosis (PJK) in Scheuermann's kyphosis (SK) varies between 24 and 40%. Multiple factors have been implicated, including kyphosis overcorrection, failure to include proximal end vertebra, and implant choice. This study aimed to determine the goal correction parameters based upon patients' pelvic incidence, and UIV to decrease PJK in Scheuermann's kyphosis.
Methods:
X-ray and chart review of SK patients operated with all pedicle screw (PS), hybrid fixation (HF), and anterior/posterior fusions with hybrid fixation (AP). T1/T2 were grouped together as proximal fusion groups compared to T3 and distal groups.
Results:
96 total patients: PS (n = 41), HF (n = 24), and AP (n = 31). Overall, at early postop 12 (12.5%) patients had PJK. At final follow-up, 33 (34.4%) had PJK. There was no significant difference between groups at early postop (p = 0.86) or final follow-up (p = 0.67). When correcting kyphosis-PI to > - 10.0° and UIV was chosen to be T1 or T2, PJK developed in 6.1% of patients at final follow-up; when fusing to T1/T2 but with kyphosis-PI < - 10.0°, 38.9% of patients developed PJK. With kyphosis-PI > - 10.0° and UIV at T3 or below, 37.0% of patients developed PJK at final follow-up. When fusing to T3 or below but failing to correct kyphosis-PI to > - 10.0°, 77.8% of patients developed PJK.
Conclusion:
Selecting proximal UIV and avoiding kyphosis-PI mismatch can significantly decrease the prevalence of PJK rather than surgical technique or implant choice. Surgeons treating SK should, therefore, aim to correct kyphosis closer to the patient's pelvic incidence and choose T2/T1 as UIV.
More Related Videos

Related Concept Videos
 01:16
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:27
Mitral Valve Prolapse I: Introduction
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...