Related Experiment Video
Updated: Sep 27, 2025
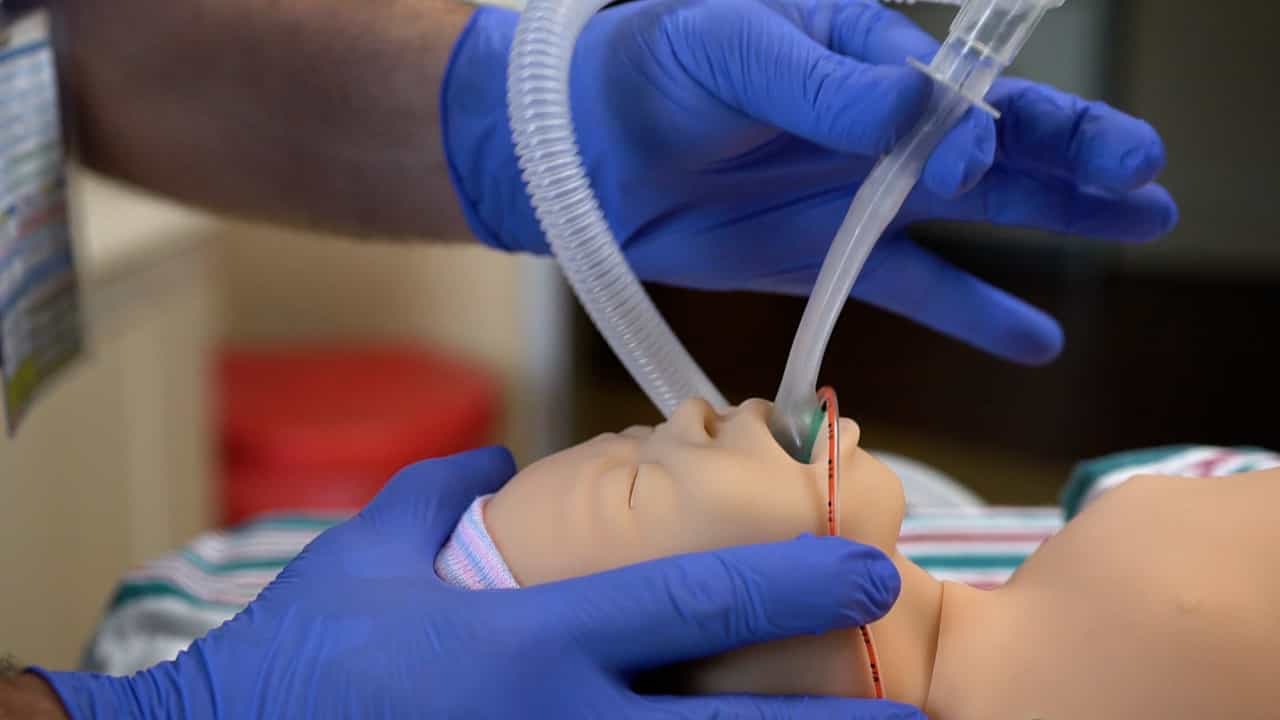

Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Respiratory support of infants born at 22-24 weeks of gestational age
Mikael Norman1, Baldvin Jonsson2, Linda Wallström3
1Department of Clinical Science, Intervention and Technology, Karolinska Institutet, Stockholm, Sweden; Department of Neonatal Medicine, S3:03 Norrbacka, Karolinska University Hospital, SE-171 76, Stockholm, Sweden.

Insights
Respiratory support for extremely preterm infants (22-24 weeks gestational age) remains challenging. Optimizing ventilation strategies is crucial to prevent lung damage and bronchopulmonary dysplasia in these vulnerable newborns.
Area of Science:
- Neonatology
- Pediatric Pulmonology
- Perinatal Medicine
Background:
- Extremely preterm infants (22-24 weeks gestational age) face significant challenges with lung immaturity and acute respiratory failure.
- Mechanical ventilation and prolonged respiratory support are frequently required, highlighting a critical care gap.
- Established respiratory support strategies for mature infants are often unsuitable for this population due to developmental differences.
Purpose of the Study:
- To review current knowledge and challenges in respiratory management for extremely preterm infants.
- To identify optimal respiratory support strategies tailored to the unique physiology of immature lungs.
- To address the need for improved methods to prevent lung injury and promote lung development in this cohort.
Main Methods:
- This review synthesizes existing literature on respiratory care for infants born at 22-24 weeks gestational age.
- It focuses on the complexities of mechanical ventilation and non-invasive respiratory support.
- The review examines strategies aimed at minimizing lung damage and fostering lung growth.
Main Results:
- Lung immaturity in extremely preterm infants necessitates specialized respiratory support.
- Current evidence suggests a knowledge gap in optimal ventilation strategies for this population.
- Increased survival rates correlate with rising incidence of bronchopulmonary dysplasia and long-term lung function deficits.
Conclusions:
- There is a critical need for evidence-based strategies for respiratory support in extremely preterm infants.
- Avoiding lung injury and promoting lung development are paramount to improving outcomes.
- Further research is warranted to refine respiratory care for this vulnerable group.
Abstract:
Lung immaturity and acute respiratory failure are the major problems in the care of extremely preterm infants. Most infants with gestational age (GA) 22-24 weeks will need mechanical ventilation and many will depend on some type of respiratory support, invasive and non-invasive for extended periods. There is ongoing gap in knowledge regarding optimal respiratory support and applying strategies that are effective in more mature populations is not easy or even suitable because lung maturation differs in smaller infants. Better strategies on how to avoid lung damage and to promote growth and development of the immature lung are warranted since increased survival is accompanied by increasing rates of bronchopulmonary dysplasia and concerns over long-standing reductions in lung function. This review focuses on some aspects of respiratory care of infants born at 22-24 weeks of GA.

Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:05
Breathing
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: