Related Experiment Video
Updated: Sep 25, 2025


Mouse Model of Surgical Uterine Injury and Subsequent Pregnancy Outcomes
Published on: June 27, 2025
Placenta accreta spectrum: a non-oncologic challenge for gynecologic oncologists
Omar Touhami1, Lisa Allen2, Homero Flores Mendoza2
1Gynecologic Oncology Division, Department of Obstetrics and Gynecology, Centre Intégré Universitaire de Santé et Services Sociaux CIUSSS du Saguenay-Lac-Saint-Jean, Sherbrooke University, Sherbrooke, Quebec, Canada touhamiomar@yahoo.fr.

Placenta accreta spectrum disorders are a major risk factor for severe postpartum hemorrhage and maternal death worldwide, with a rapidly growing incidence in recent decades due to increasing rates of cesarean section. Placenta accreta spectrum disorders represent a complex surgical challenge, with the primary concern of massive obstetrical hemorrhagic sequelae and organ damage, occurring in the context of potentially significant anatomical and physiological changes of pregnancy. Most international obstetrical organizations have published guidelines on placenta accreta spectrum, embracing the creation of regionalized 'Centers of Excellence' in the diagnosis and management of placenta accreta spectrum, which includes a dedicated multidisciplinary surgical team. One mandatory criterion for these Centers of Excellence is the presence of a surgeon experienced in complex pelvic surgeries. Indeed, many institutions in the United States and worldwide rely on gynecologic oncologists in the surgical management of placenta accreta spectrum due to their experience and skills in complex pelvic surgery. Surgical management of placenta accreta spectrum frequently includes challenging pelvic dissection in regions with distortion of anatomy alongside large aberrant neovascularization. With a goal of definitive management through cesarean hysterectomy, surgeons require a systematic and thoughtful approach to promote prevention of urologic injuries, embrace measures to secure challenging hemostasis and, in selected cases, employ conservative management where indicated or desired. In this review recommendations are made for gynecologic oncologists regarding the management and important considerations in the successful care of placenta accreta spectrum disorders. Where required, gynecologic oncologists are encouraged to be proactively involved in the management of placenta accreta spectrum, not only intra-operatively, but also in the development of clinical protocols, guidelines, and pre-operative counseling of patients, as a 'call if needed' approach is suboptimal for this potentially major and life-threatening condition.
Placenta accreta spectrum disorders are a major risk factor for severe postpartum hemorrhage and maternal death worldwide, with a rapidly growing incidence in recent decades due to increasing rates of cesarean section. Placenta accreta spectrum disorders represent a complex surgical challenge, with the primary concern of massive obstetrical hemorrhagic sequelae and organ damage, occurring in the context of potentially significant anatomical and physiological changes of pregnancy. Most international obstetrical organizations have published guidelines on placenta accreta spectrum, embracing the creation of regionalized 'Centers of Excellence' in the diagnosis and management of placenta accreta spectrum, which includes a dedicated multidisciplinary surgical team. One mandatory criterion for these Centers of Excellence is the presence of a surgeon experienced in complex pelvic surgeries. Indeed, many institutions in the United States and worldwide rely on gynecologic oncologists in the surgical management of placenta accreta spectrum due to their experience and skills in complex pelvic surgery. Surgical management of placenta accreta spectrum frequently includes challenging pelvic dissection in regions with distortion of anatomy alongside large aberrant neovascularization. With a goal of definitive management through cesarean hysterectomy, surgeons require a systematic and thoughtful approach to promote prevention of urologic injuries, embrace measures to secure challenging hemostasis and, in selected cases, employ conservative management where indicated or desired. In this review recommendations are made for gynecologic oncologists regarding the management and important considerations in the successful care of placenta accreta spectrum disorders. Where required, gynecologic oncologists are encouraged to be proactively involved in the management of placenta accreta spectrum, not only intra-operatively, but also in the development of clinical protocols, guidelines, and pre-operative counseling of patients, as a 'call if needed' approach is suboptimal for this potentially major and life-threatening condition.
More Related Videos
 09:04
Comprehensive Evaluation of the Effectiveness and Safety of Placenta-Targeted Drug Delivery Using Three Complementary Methods
Published on: September 10, 2018
 09:51
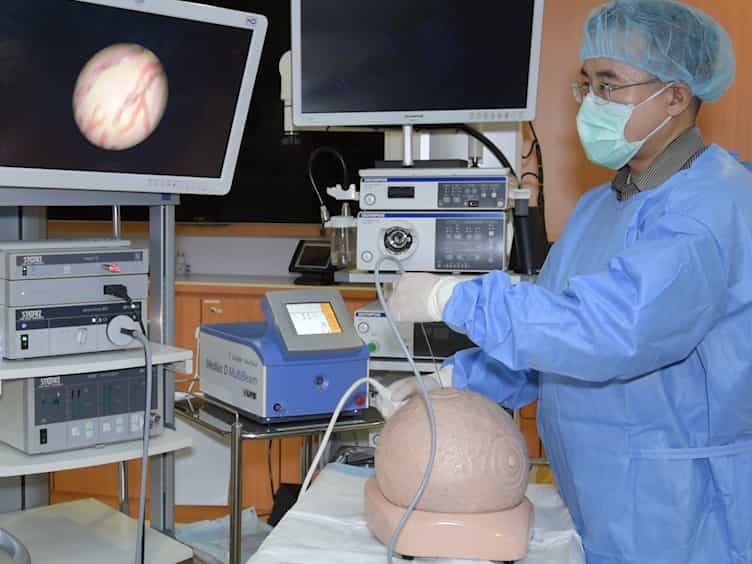
Model Surgical Training: Skills Acquisition in Fetoscopic Laser Photocoagulation of Monochorionic Diamniotic Twin Placenta Using Realistic Simulators
Published on: March 21, 2018
