Related Experiment Video
Updated: Sep 24, 2025
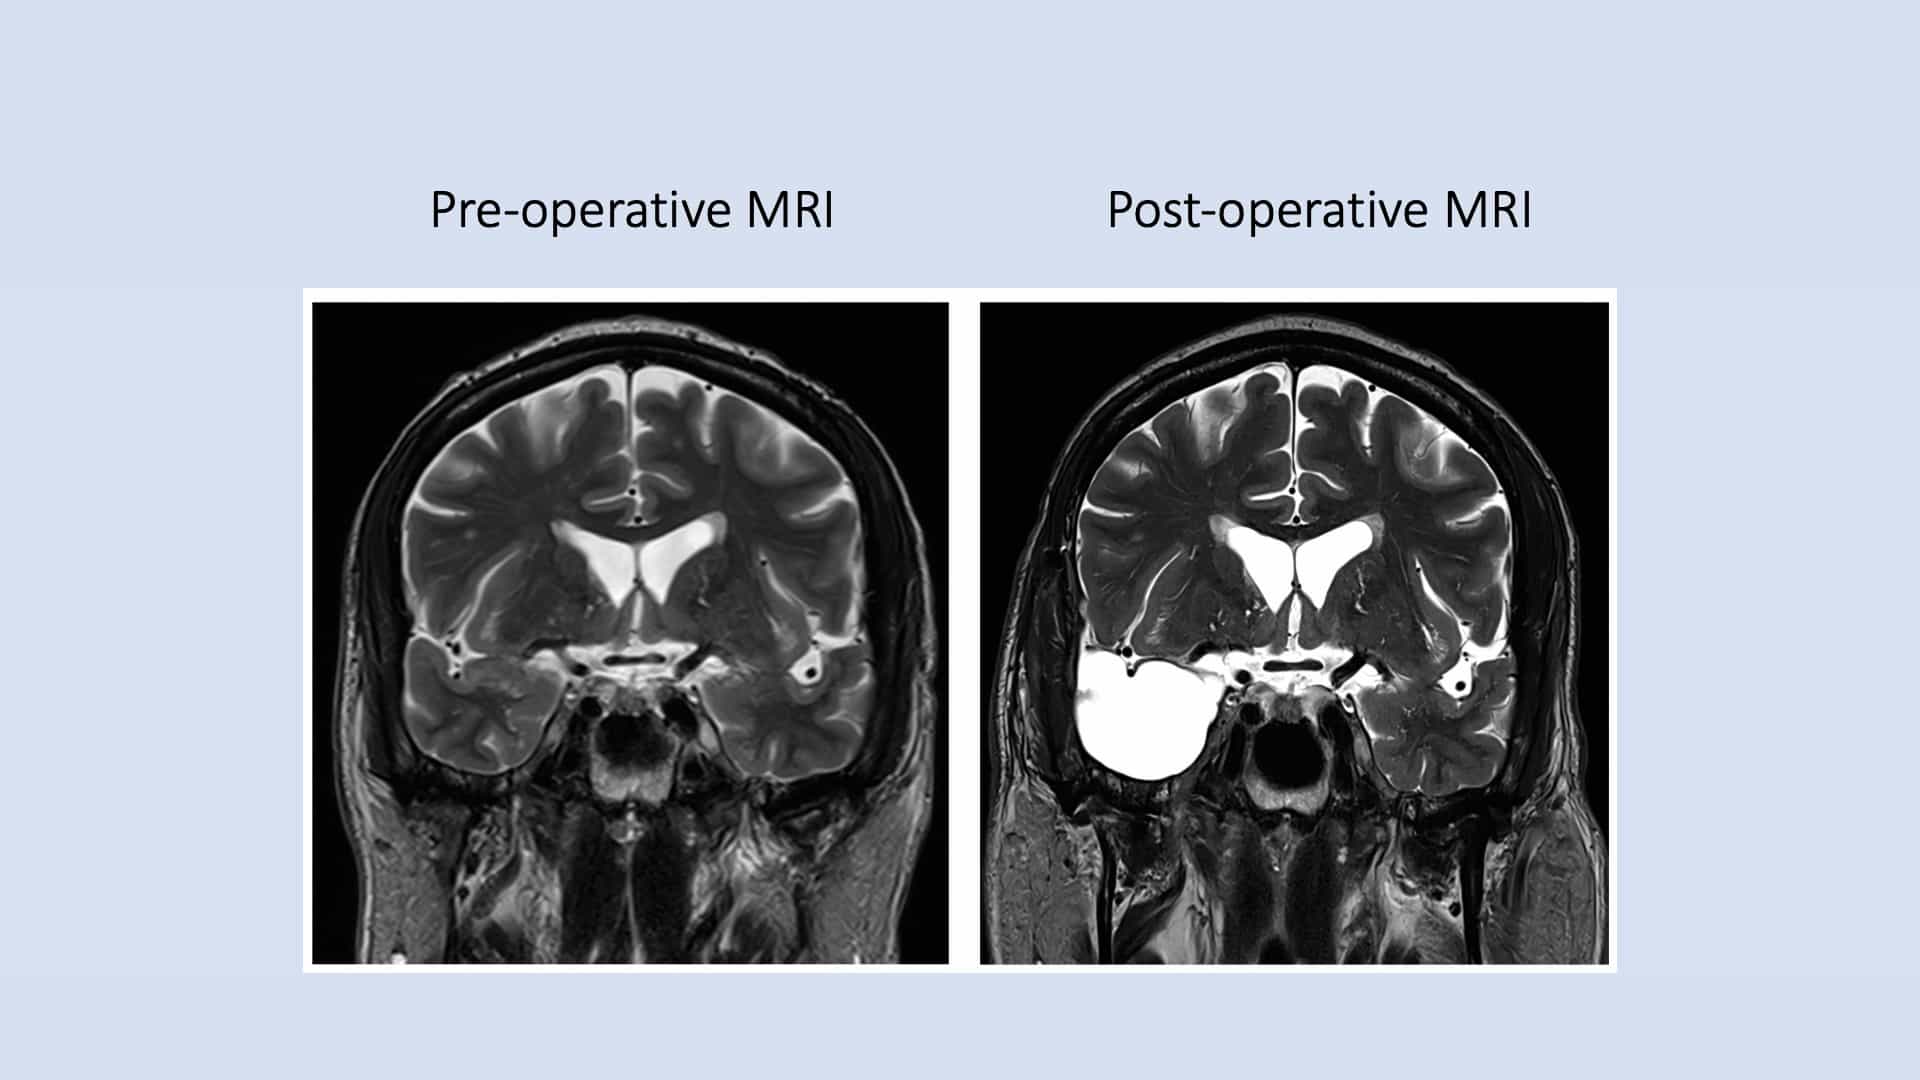

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Decompressive craniectomy combined with temporal pole resection in the treatment of massive cerebral infarction
Wenchao Lu1, Dong Jia1, Yanchang Qin2
1Department of Neurosurgery, the Xi'an Daxing Hospital, No. 353 Laodong North Road, Xi'an, 710000, Shaanxi Province, China.

Insights
Decompressive craniectomy with temporal pole resection improves outcomes for massive cerebral infarction patients. This combined approach offers better decompression, controlled intracranial pressure, and reduced mortality compared to standard decompressive craniectomy.
Area of Science:
- Neurosurgery
- Neurology
- Critical Care Medicine
Background:
- Massive cerebral infarction poses significant mortality risks.
- Effective surgical interventions are crucial for managing intracranial pressure and improving patient prognosis.
Purpose of the Study:
- To evaluate the efficacy and prognosis of decompressive craniectomy combined with temporal pole resection for massive cerebral infarction.
- To provide evidence-based guidance for treatment selection in such cases.
Main Methods:
- Retrospective analysis of clinical data from January 2015 to December 2018.
- Comparison between a control group (decompressive craniectomy) and a study group (decompressive craniectomy + temporal pole resection).
- Monitoring of intracranial pressure, NIHSS scores, length of stay, mortality, and modified Rankin Scale (mRS).
Main Results:
- The study group showed significantly lower NIHSS scores and intracranial pressure post-operation compared to the control group.
- One-year mortality was significantly reduced in the study group (21.7%) versus the control group (38.8%).
- Improved modified Rankin Scale scores were observed in the study group post-treatment.
Conclusions:
- Decompressive craniectomy with temporal pole resection demonstrates superior efficacy in treating massive cerebral infarction.
- This combined surgical approach provides effective decompression, better intracranial pressure control, and reduced mortality.
- The combined technique holds significant clinical value for managing massive cerebral infarction.
Objective:
To evaluate the efficacy and prognosis of decompressive craniectomy combined with temporal pole resection in the treatment of massive cerebral infarction, in order to provide basis for treatment selection.
Methods:
The clinical data of the patient with massive cerebral infarction treated in our hospital from January 2015 to December 2018 were analyzed retrospectively. According to the surgical methods, the patients were divided into control group (decompressive craniectomy) and study group (decompressive craniectomy + temporal pole resection). Intracranial pressure monitoring devices were placed in both groups. The NIHSS scores of the two groups before and 14 days after operation, the changes of intracranial pressure, length of hospital stay, length of NICU, mortality and modified Rankin scale before and after treatment were compared between the two groups.
Results:
The NIHSS score of the two groups after operation was lower than that before operation, and the NIHSS score of the study group was significantly lower than that of the control group (P < 0.05); The intracranial pressure in the study group was significantly lower than that in the control group (P < 0.05); One month after operation, the mortality of the study group (13.0%) was lower than that of the control group (27.8%). After one year of follow-up, the mortality of the study group (21.7%) was significantly lower than that of the control group (38.8%) (P < 0.05); The scores of mRS in the two groups were significantly improved compared with those before treatment (P < 0.05), and the scores of mRS in the study group were better than those in the control group (P < 0.05).
Conclusion:
Decompressive craniectomy combined with temporal pole resection has a better effect in the treatment of patients with massive cerebral infarction. It has good decompression effect, the postoperative intracranial pressure is well controlled, and significantly reduced the mortality. So it has better clinical application value.

