Related Experiment Video
Updated: Sep 24, 2025
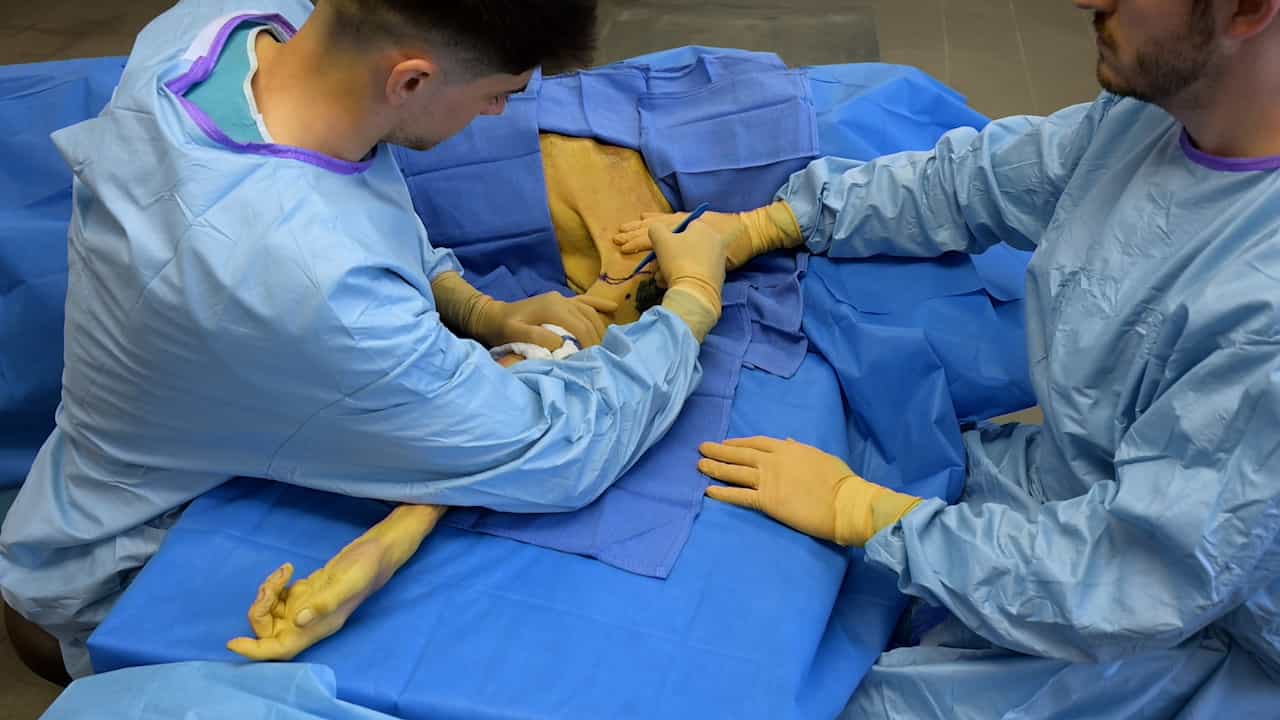

Vascularized Composite Upper Limb Allograft Harvesting for Proximal Arm Allotransplantation
Published on: June 13, 2025
Upper Extremity Infections in the Transplant Population
Rachel E Aliotta1, DeAsia D Jacob1, Sayf Al-Deen Said1
1Department of Plastic & Reconstructive Surgery, Dermatology & Plastic Surgery Institute, Cleveland Clinic Foundation, Cleveland, OH.

Purpose:
As the duration of lifetime survival after organ transplantation continues to increase, the consequences of long-term immunosuppression, such as opportunistic and rare infections, are a high-risk reality. This study examined upper extremity infections in the transplant population to determine the current clinical risk profile, management, and outcomes.
Methods:
An institutional database of 16,640 patients who underwent transplantation was queried for upper extremity infections from 2005 to 2017, defined as the presence of infection from the shoulder to the fingertips. The resulting data were analyzed using multivariable linear and logistic regression modeling.
Results:
A total of 230 eligible patients experienced upper extremity infections at a mean age of 54.1 ± 15.3 years, occurring, on average, 7.9 ± 8.6 years after transplantation. The most commonly transplanted organ was the kidney (51.3%), followed by the liver (20%). The most common location of infection was the forearm (31.7%), digits (27.4%), and upper arm (17%). The most common types of infection were cellulitis (69.1%), abscess (33.5%), joint sepsis (6.5%), infectious tenosynovitis (3.9%), and osteomyelitis (1.3%). Patients taking an antifungal medication, those who had a joint infection, or those who had undergone lung transplantation had an approximately 2.5-day longer stay in the hospital. For every 1-year increase in age at the time of transplantation, the time from transplantation to infection decreased by 0.21 years. Those who had undergone bone marrow transplantation or those who were taking tacrolimus were expected to have approximately 8- and 6-year decreases, respectively, in the time from transplantation to infection.
Conclusions:
Upper extremity infections should be individually evaluated and treated because of the heterogeneity of transplant type, immunosuppression medications, the age of the patient, and infection characteristics.
Type Of Study/Level Of Evidence:
Prognostic IV.
More Related Videos
Related Concept Videos
 01:16
Kidney Transplant III: Nursing Management
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy...
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:25
Endocarditis I: Introduction