Related Experiment Video
Updated: Sep 22, 2025


Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Conduction system pacing vs. biventricular pacing in patients with ventricular dysfunction and AV block
Margarida Pujol-López1,2, Rafael Jiménez Arjona1, Eduard Guasch1,2,3,4
1Institut Clínic Cardiovascular (ICCV), Hospital Clínic, Universitat de Barcelona, Catalonia, Spain.

Insights
His-Purkinje conduction system pacing (HPCSP) is a viable alternative to biventricular CRT for patients with left ventricular dysfunction. HPCSP demonstrated similar LVEF improvement and response rates, with significant enhancements in mitral regurgitation and NYHA class.
Area of Science:
- Cardiology
- Electrophysiology
- Heart Failure Management
Background:
- Cardiac resynchronization therapy (CRT) is standard for heart failure with reduced ejection fraction.
- The efficacy of His-Purkinje conduction system pacing (HPCSP) as an alternative to biventricular CRT (BiVCRT) is not well-established.
- Left ventricular dysfunction often necessitates ventricular pacing due to atrioventricular block.
Purpose of the Study:
- To compare echocardiographic and clinical outcomes of HPCSP versus BiVCRT.
- To evaluate HPCSP as a potential alternative to BiVCRT in patients with left ventricular dysfunction and atrioventricular block.
Main Methods:
- Retrospective comparison of consecutive HPCSP patients with a historical BiVCRT cohort.
- 1:1 matching based on age, LVEF, atrial fibrillation, renal function, and cardiomyopathy type.
- Responders defined by survival, no heart transplant, and LVEF increase ≥5 points at 6 months.
Main Results:
- HPCSP achieved 92.5% success rate; 76% responders vs. 64% in BiVCRT (p=0.33).
- Similar LVEF improvement (10% vs. 7%, p=0.24) between HPCSP and BiVCRT.
- HPCSP significantly improved mitral regurgitation (82% vs. 25%, p=0.02) and NYHA class (1 point vs. 0.5, p=0.02).
Conclusions:
- HPCSP is a promising alternative to BiVCRT for patients with LVEF ≤45% and atrioventricular block.
- HPCSP significantly improves LVEF, mitral regurgitation, and functional status.
- HPCSP offers comparable efficacy to BiVCRT with potential advantages in specific patient groups.
Background:
It is unknown whether His-Purkinje conduction system pacing (HPCSP), as either His bundle or left bundle branch pacing, could be an alternative to cardiac resynchronization therapy (BiVCRT) for patients with left ventricular dysfunction needing ventricular pacing due to atrioventricular block. The aim of the study is to compare the echocardiographic response and clinical improvement between HPCSP and BiVCRT.
Methods:
Consecutive patients who successfully received HPCSP were compared with a historical cohort of BiVCRT patients. Patients were 1:1 matched by age, LVEF, atrial fibrillation, renal function and cardiomyopathy type. Responders were defined as patients who survived, did not require heart transplantation and increased LVEF ≥5 points at 6-month follow-up.
Results:
HPCSP was successfully achieved in 92.5% (25/27) of patients. During follow-up, 8% (2/25) of HPCSP patients died and 4% (1/25) received a heart transplant, whereas 4% (1/25) of those in the BiVCRT cohort died. LVEF improvement was 10% ± 8% HPCSP versus 7% ± 5% BiVCRT (p = .24), and the percentage of responders was 76% (19/25) HPCSP versus 64% (16/25) BiVCRT (p = .33). Among survivors, the percentage of patients who improved from baseline II-IV mitral regurgitation (MR) to 0-I MR was 9/11 (82%) versus 2/8 (25%) (p = .02). Compared to those with BiVCRT, patients with HPCSP achieved better NYHA improvement: 1 point versus 0.5 (OR 0.34; p = .02).
Conclusion:
HPCSP in patients with LVEF ≤45% and atrioventricular block improved the LVEF and induced a response similar to that of BiVCRT. HPCSP significantly improved MR and NYHA functional class. HPCSP may be an alternative to BiVCRT in these patients. (Figure 1. Central Illustration). [Figure: see text].
More Related Videos
 08:05
Optimization of Transesophageal Atrial Pacing to Assess Atrial Fibrillation Susceptibility in Mice
Published on: June 29, 2022
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Related Concept Videos
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:19
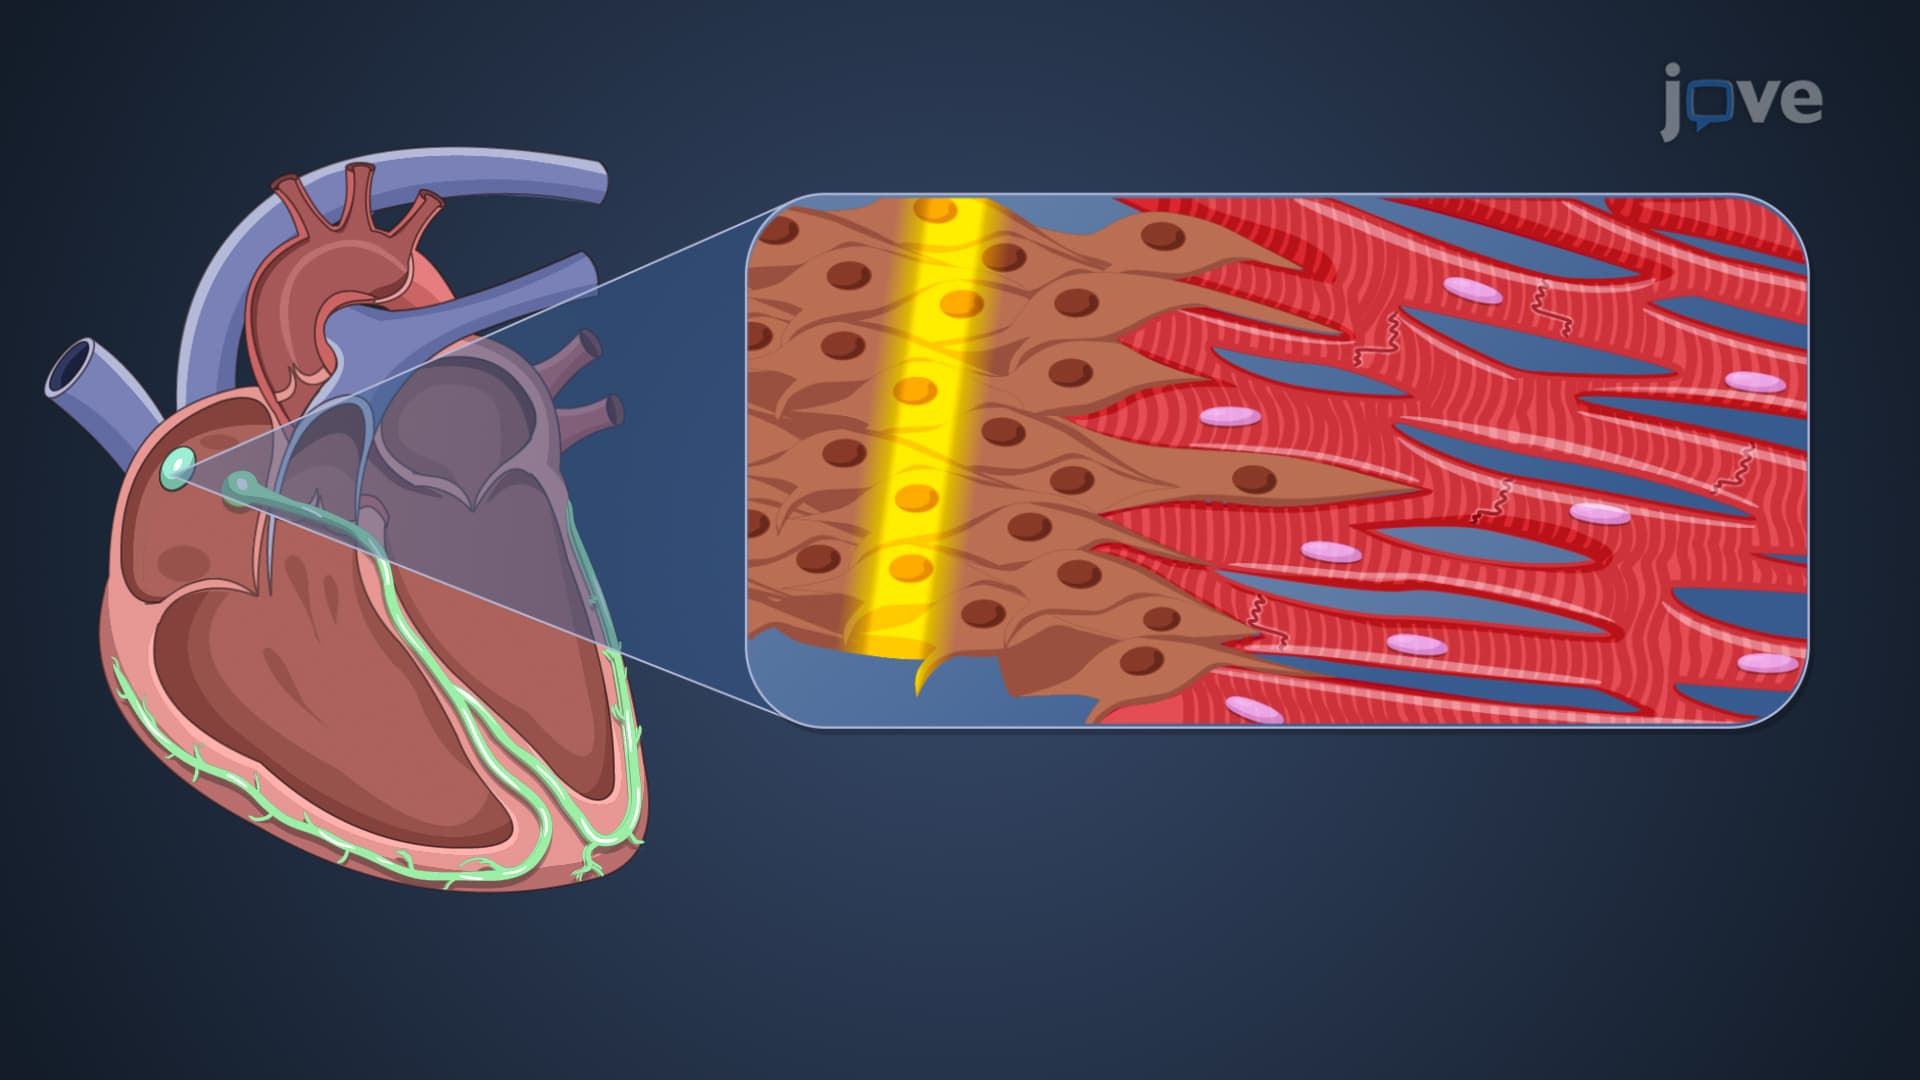
Conduction System of the Heart
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:19
Electrophysiology of Normal Cardiac Rhythm