Related Experiment Video
Updated: Sep 22, 2025


An Oncogenic Hepatocyte-Induced Orthotopic Mouse Model of Hepatocellular Cancer Arising in the Setting of Hepatic Inflammation and Fibrosis
Published on: September 12, 2019
Impact of lenvatinib on renal function compared to sorafenib for unresectable hepatocellular carcinoma
Ryu Sasaki1, Masanori Fukushima, Masafumi Haraguchi
1Department of Gastroenterology and Hepatology, Nagasaki University Graduate School of Biomedical Sciences, 1-7-1 Sakamoto, Nagasaki City, Nagasaki, Japan.

Abstract:
Anti-VEGF drugs, such as tyrosine kinase inhibitors, play an important role in systemic therapy for unresectable hepatocellular carcinoma (uHCC). We examined the effects of sorafenib and lenvatinib on proteinuria and renal function.Patients who were administered sorafenib (n = 85) or lenvatinib (n = 52) as first line treatment for uHCC from July 2009 to October 2020, were enrolled in this retrospective observational study. A propensity score analysis including 13 baseline characteristics was performed. Eighty four patients were selected (sorafenib, n = 42; lenvatinib, n = 42) by propensity score matching (one-to-one nearest neighbor matching within a caliper of 0.2). We analyzed changes in estimated glomerular filtration rate (eGFR) during tyrosine kinase inhibitor treatment, as well as the development of proteinuria in both groups. A multivariate analysis was performed to identify predictors of a deterioration of eGFR.At 4, 8, 12, and 16 weeks, ΔeGFR was significantly lower in the lenvatinib group than in the sorafenib group (P < .05). The lenvatinib group showed a significantly higher frequency of proteinuria than the sorafenib group (30.9% vs 7.1%, P = .005) and had a higher rate of decrease in eGFR than the sorafenib group (P < .05). Multivariate analysis revealed that lenvatinib use was the only predictive factor of eGFR deterioration (odds ratio 2.547 [95% CI 1.028-6.315], P = .043). In cases of proteinuria ≤1+ during lenvatinib treatment, eGFR did not decrease. However, eGFR decreased in the long term (>24 weeks) in patients who have proteinuria ≥2+.Lenvatinib has a greater effect on proteinuria and renal function than sorafenib. In performing multi-molecular targeted agent sequential therapy for uHCC, proteinuria and renal function are important factors associated with drug selection after atezolizumab-bevacizumab combination therapy currently used as the first-line treatment.
Insights
Lenvatinib significantly impacts proteinuria and renal function more than sorafenib in unresectable hepatocellular carcinoma (uHCC) treatment. Monitoring proteinuria is crucial for managing kidney function during tyrosine kinase inhibitor therapy.
Area of Science:
- Hepatology
- Nephrology
- Pharmacology
Background:
- Anti-VEGF tyrosine kinase inhibitors (TKIs) are vital for unresectable hepatocellular carcinoma (uHCC).
- Sorafenib and lenvatinib are commonly used first-line TKIs for uHCC.
- Understanding their differential effects on renal function is critical for patient management.
Purpose of the Study:
- To compare the effects of sorafenib and lenvatinib on proteinuria and renal function in uHCC patients.
- To identify predictors of renal function deterioration during TKI therapy.
- To inform sequential targeted therapy decisions in uHCC.
Main Methods:
- Retrospective observational study of 137 uHCC patients treated with sorafenib or lenvatinib.
- Propensity score matching (1:1) created a cohort of 84 patients (42 per group).
- Analysis of changes in estimated glomerular filtration rate (eGFR) and proteinuria development.
Main Results:
- Lenvatinib group showed significantly lower ΔeGFR at 4, 8, 12, and 16 weeks compared to sorafenib.
- Higher incidence of proteinuria (30.9% vs 7.1%) and greater eGFR decrease in the lenvatinib group.
- Lenvatinib use was the sole predictor of eGFR deterioration (OR 2.547).
- Proteinuria ≤1+ with lenvatinib did not decrease eGFR; ≥2+ led to long-term decrease.
Conclusions:
- Lenvatinib exerts a greater impact on proteinuria and renal function compared to sorafenib.
- Proteinuria and renal function are key considerations for selecting subsequent targeted therapies in uHCC.
- Close monitoring of renal function and proteinuria is essential during lenvatinib treatment.
Related Concept Videos
 01:15
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:06
Renal Drug Clearance: Overview
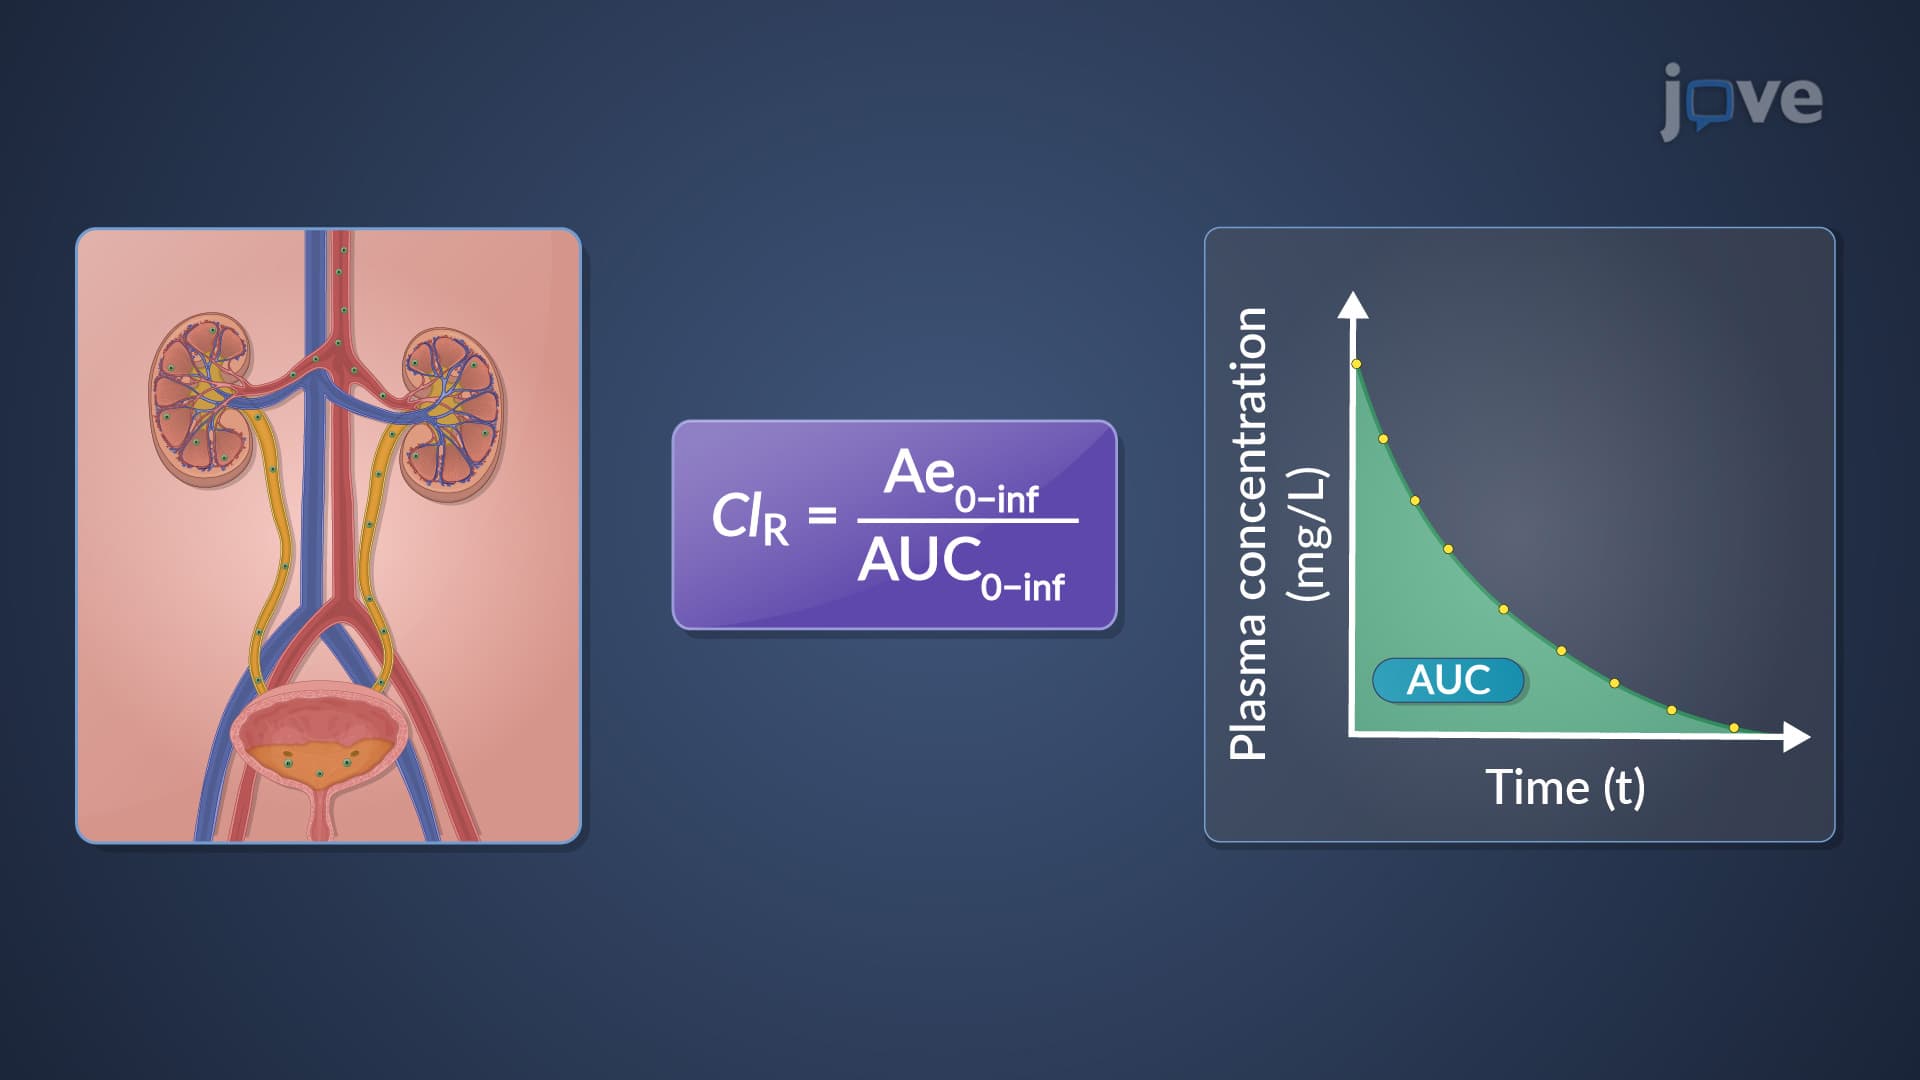
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:16
Hepatic Drug Excretion: Influencing Factors
 01:28
Renal Drug Excretion: Tubular Secretion
 01:08
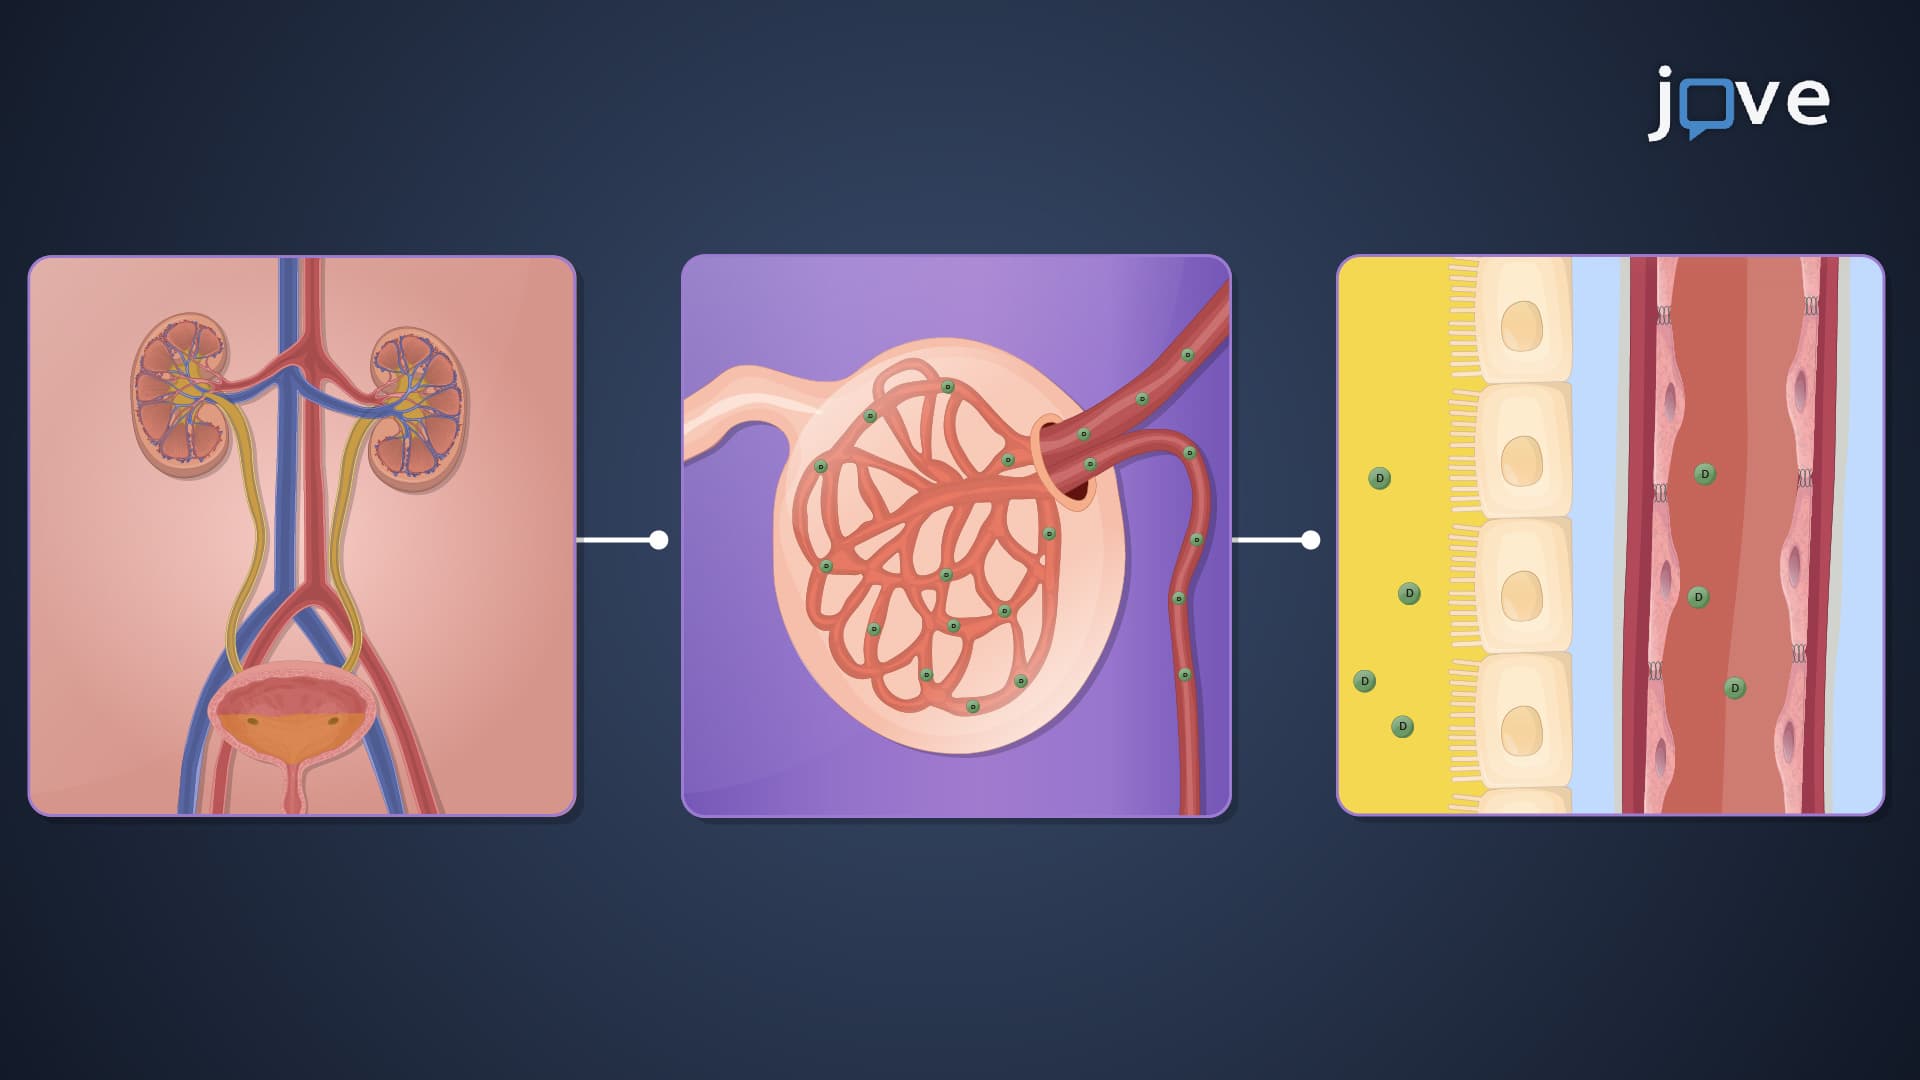
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...