Related Experiment Video
Updated: Sep 21, 2025

Ultrasound-guided Botulinum Toxin-A Injections: A Method of Treating Sialorrhea
Published on: November 9, 2016
Evaluating intramuscular neural distribution in the cricopharyngeus muscle for injecting botulinum toxin
Bo Hae Kim1, Do Hyung Kim2, Ji-Hyun Lee3
1Department of Otorhinolaryngology-Head and Neck Surgery, Dongguk university Ilsan Hospital, College of Medicine, Goyang, South Korea; Sensory Organ Research Institute, College of Medicine, Dongguk University, Gyengju, South Korea.

Objectives:
The objective of this study was to determine the area in the cricopharyngeus muscle (CPM) where botulinum neurotoxin (BoNT) can be injected safely and effectively by evaluating neural distribution in the CPM.
Methods:
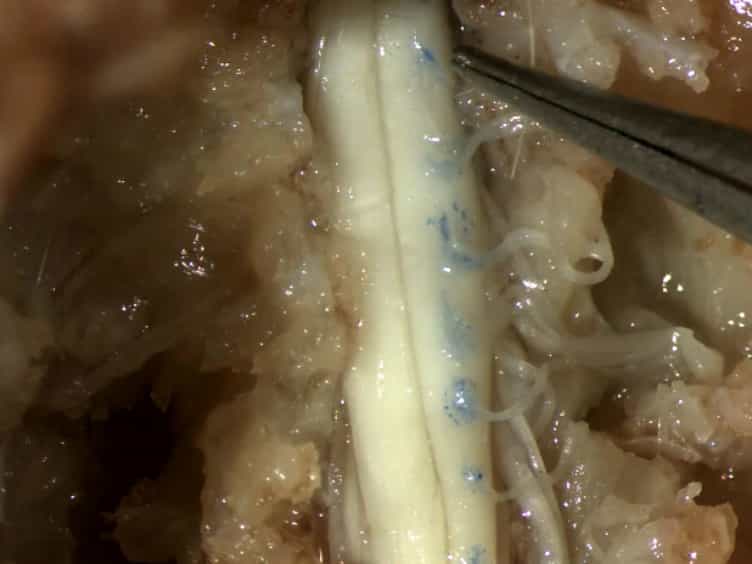
Eleven specimens of the CPM were gathered from human cadavers. The anatomical relationship between the posterior cricoarytenoid muscle (PCAM) and the CPM was evaluated. Myelinated nerve fibers in the CPM were stained using modified Sihler's method. The CPM was classified into five zones according to the area accessible within the CPM via transcutaneous and transluminal approaches for BoNT injection as follows: i) lateral area including upper area (zone 1) and lower area (zone 2); ii) posterolateral area including upper area (zone 3) and lower area (zone 4); and iii) posterior area (zone 5). Neural distribution originating from the pharyngeal plexus and the extralaryngeal branches of recurrent laryngeal nerve (EBRLN) within each classified zone in stained specimens was determined.
Results:
Six specimens (12 lateral areas, 12 posterolateral areas, and 6 posterior areas) were suitable for evaluating neural distribution within the CPM. Zone 1 was adjacent to the PCAM the most in all specimens. Nerve endings originating from the EBRLN were observed on four sides of zone 2 (33.3%, 4/12 sides) in three specimens (3/6, 50%). Neural distribution originating from the pharyngeal plexus was found on ten sides (83.3%, 10/12 sides) of zone 3 in five specimens (83.3%, 5/6 specimens) and on nine sides (75.0%, 9/12 sides) of zone 4 in five specimens (83.3%, 5/6 specimens).
Conclusion:
The posterolateral area (zone 3 and zone 4) is thought to be the most suitable area for alleviating the spasticity of CPM with a minimum dose of BoNT.
More Related Videos
 10:57
Intramuscular Injections Along the Motor End Plates: A Minimally Invasive Approach to Shuttle Tracers Directly into Motor Neurons
Published on: July 13, 2015
 07:09
Subcutaneous Administration of Muscarinic Antagonists and Triple-Immunostaining of the Levator Auris Longus Muscle in Mice
Published on: September 8, 2011
