Sagittal morphology of the cervical spine in adolescent idiopathic scoliosis: a retrospective case-control study
Related Experiment Video
Updated: Sep 21, 2025
Cell-based Assay Protocol for the Prognostic Prediction of Idiopathic Scoliosis Using Cellular Dielectric Spectroscopy
Published on: October 16, 2013
Shu-Man Han1, Jin-Xu Wen1, Lei Cao1
1Department of Radiology, The Third Hospital of Hebei Medical University, Shijiazhuang, China.

Background:
To investigate the relationship between sagittal alignment and coronal deformity in patients with adolescent idiopathic scoliosis (AIS) through analysis of the spinal imaging data.
Methods:
Four hundred and fifty-four AIS patients who underwent anteroposterior and lateral radiography of the while spine were enrolled, and the spinal parameters of Cobb angle, cervical lordosis, C1-C2 angle, T1 slope, thoracic kyphosis, lumbar lordosis, sacral slope, pelvic tilt (PT), pelvic incidence (PI), cervical sagittal vertical axis (SVA), and spinal SVA were analyzed.
Results:
The patients were divided into two groups according to the size of the Cobb angle: group A (Cobb angle ≤45°, n=414) and group B (Cobb angle >45°, n=40). In group A, the Cobb angle was in a medium negative correlation with the cervical lordosis angle (r=-0.637, P<0.001), a weak positive correlation (|r|<0.3, P<0.05) with C1-C2 angle, T1 slope and thoracic kyphosis. In group B, the Cobb angle was in a mild positive correlation (P<0.05) with PT (r=0.398) and PI (r=0.360). The cervical lordosis angle was significantly (P<0.05) different between male and female patients in both groups. In Group A, the cervical lordosis angle was in a significantly (P<0.01) positive correlation with the T1 slope (r=0.586), thoracic kyphosis (r=0.490), and sagittal vertical axis (r=0.135), and a significantly (P<0.01) negative correlation with cervical sagittal vertical axis (r=-0.128) and C1-C2 angle (r=-0.155). In group B, the cervical lordosis angle was in a significantly (P<0.05) positive correlation with T1 slope (r=0.661), thoracic kyphosis (r=0.608), lumbar lordosis (r=0.425), sacral slope (r=0.434), and sagittal vertical axis (r=0.335).
Conclusions:
In AIS patients with the Cobb angle ≤45º, a significant negative correlation exists between the cervical lordosis and the Cobb angle. The sagittal morphology of the cervical spine in AIS patients is affected by the spinal coronal deformity, which plays an important role in the treatment of AIS.


Related Concept Videos
 01:16
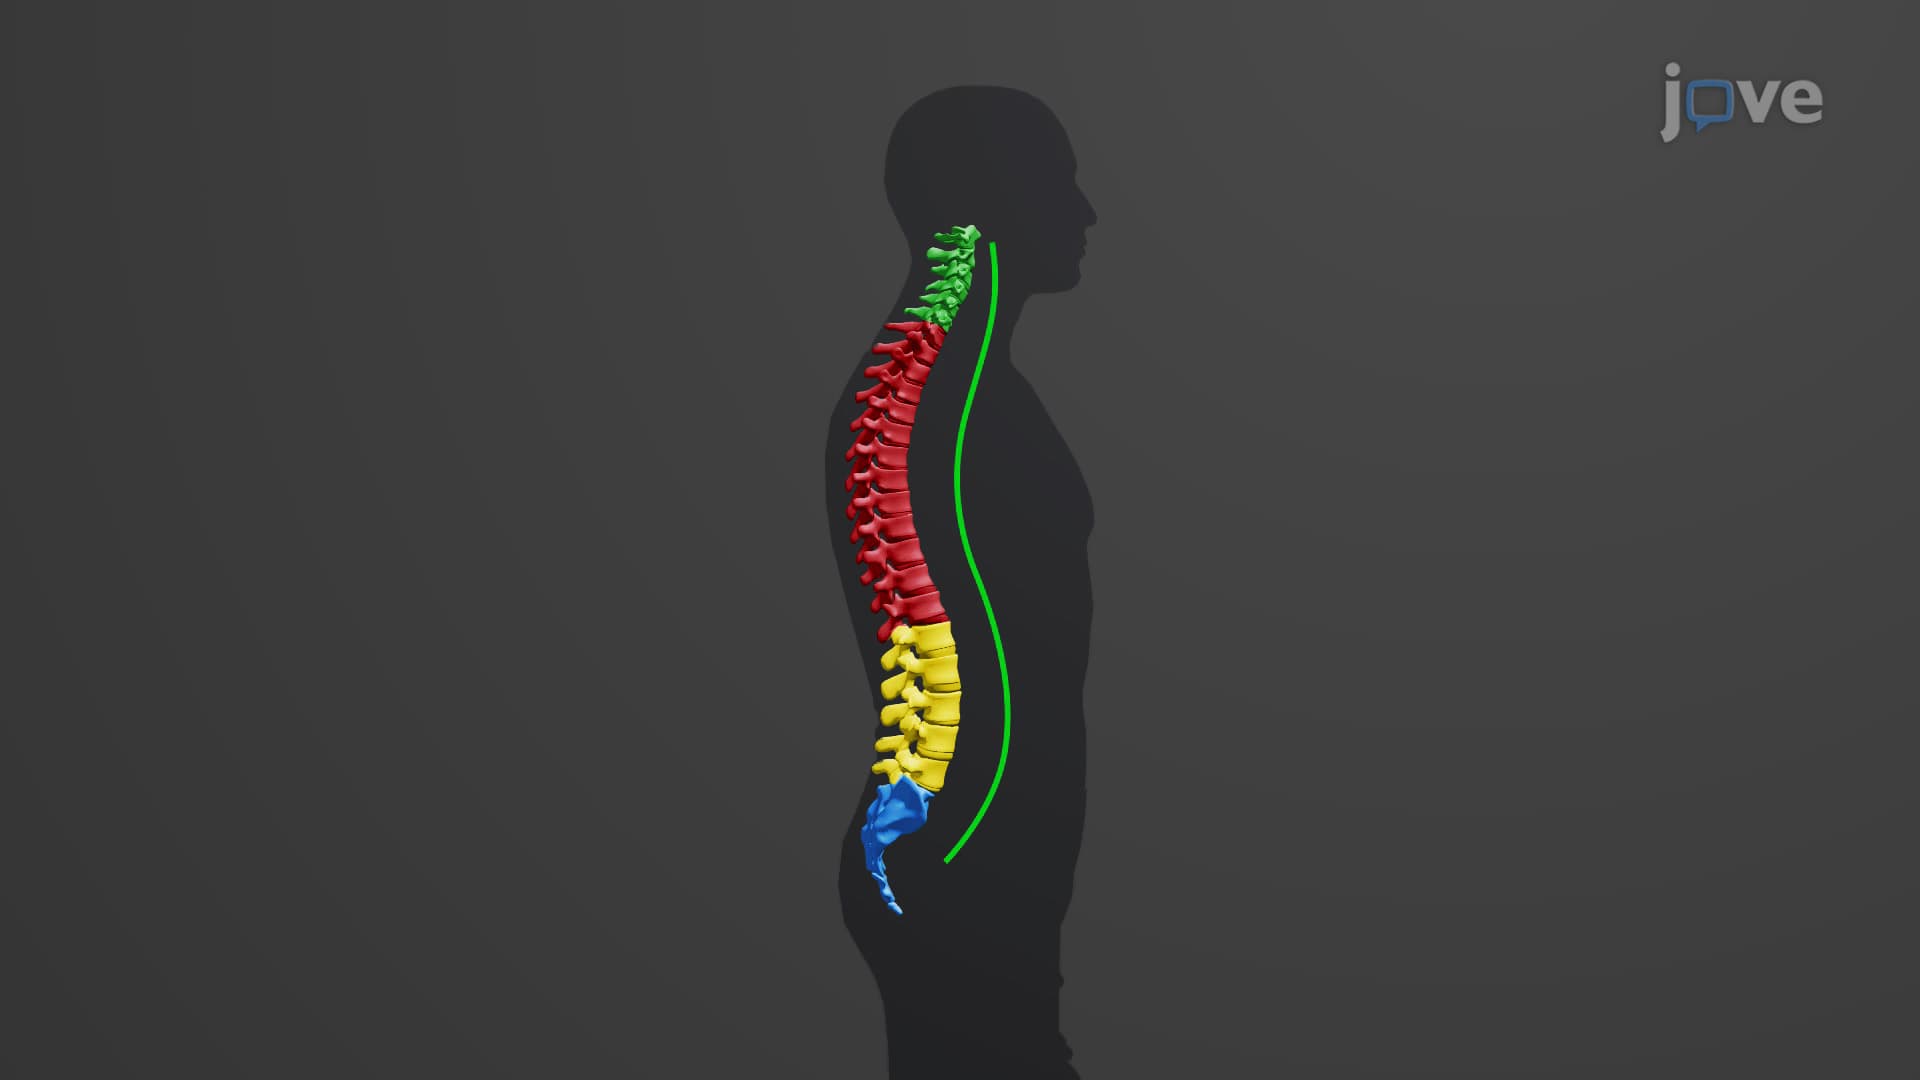
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:12
General Case of Eccentric Axial Loading
Consider a member subjected to equal and opposite forces that are applied along a line that does not coincide with the member's neutral axis. In unsymmetrical...
 01:16
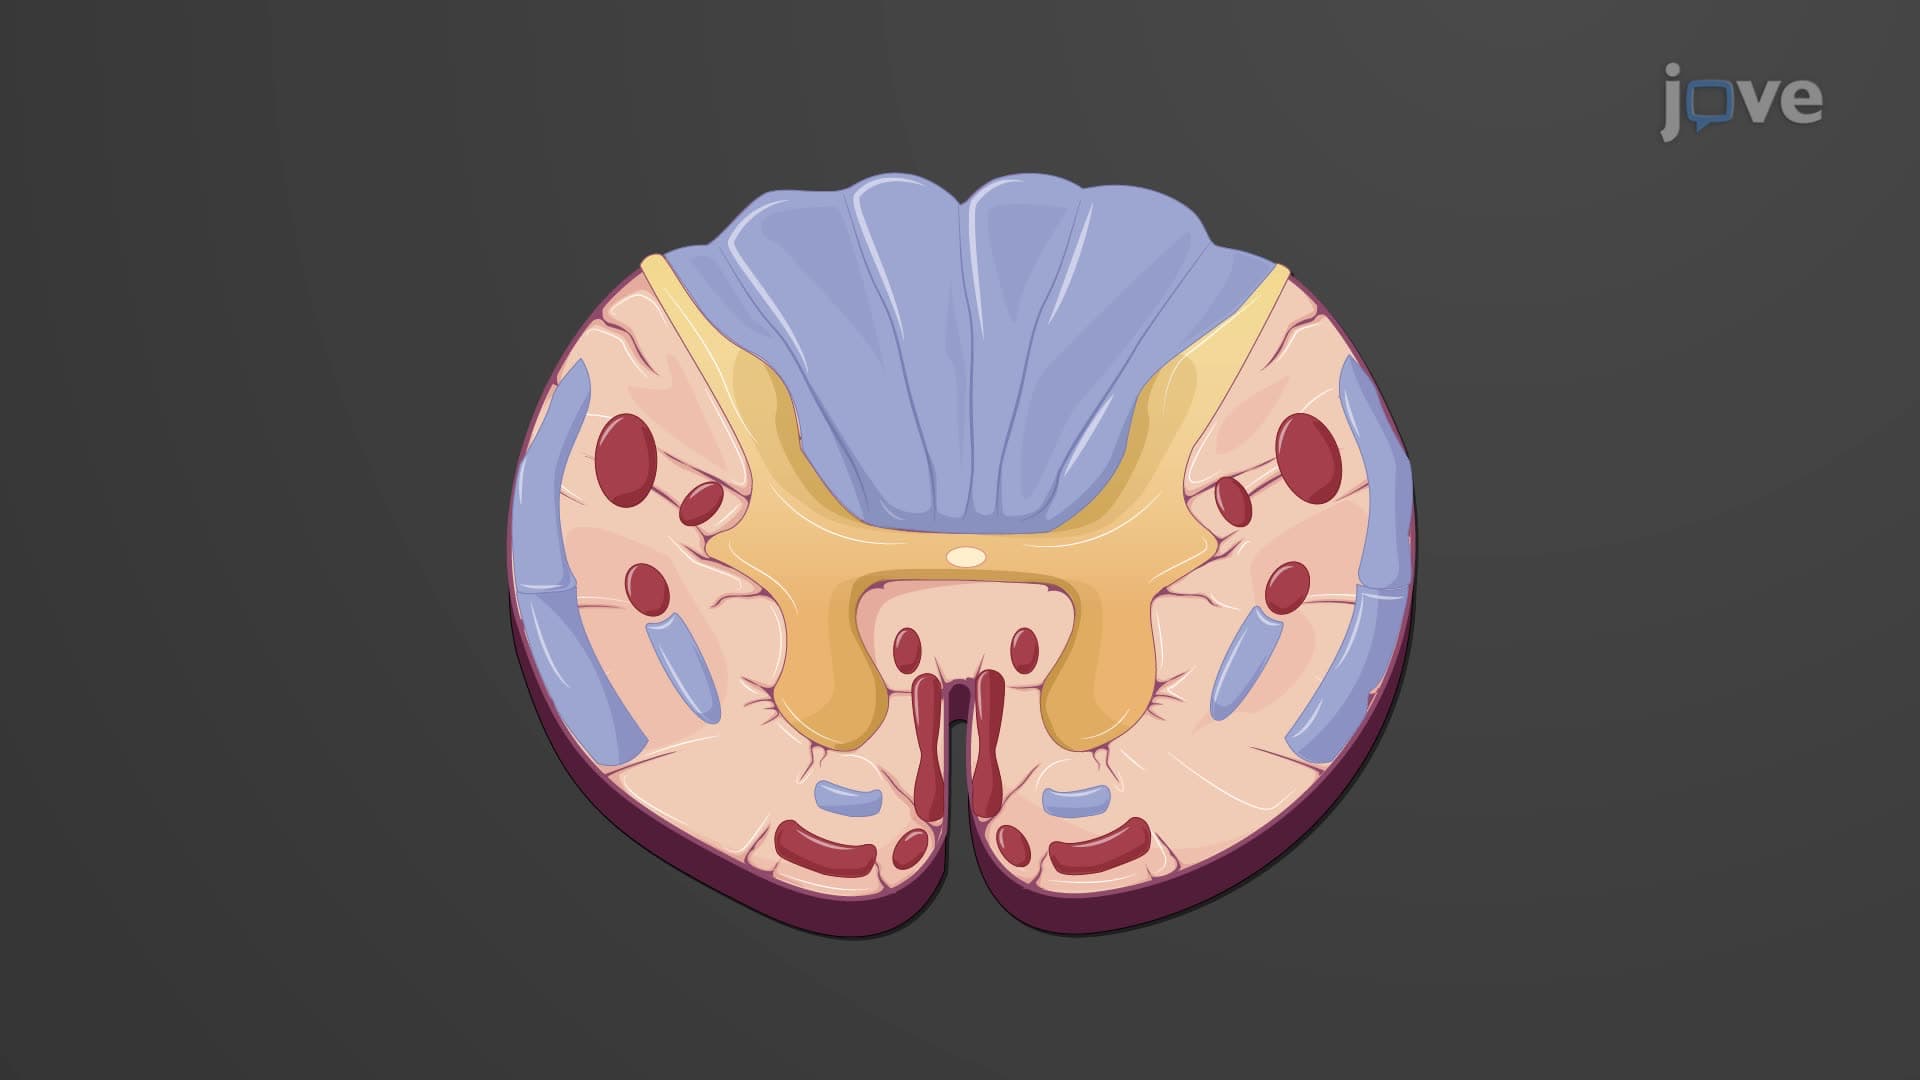
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:09
Overview of the Axial Skeleton
The axial skeleton of the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...