Related Experiment Video
Updated: Sep 8, 2025
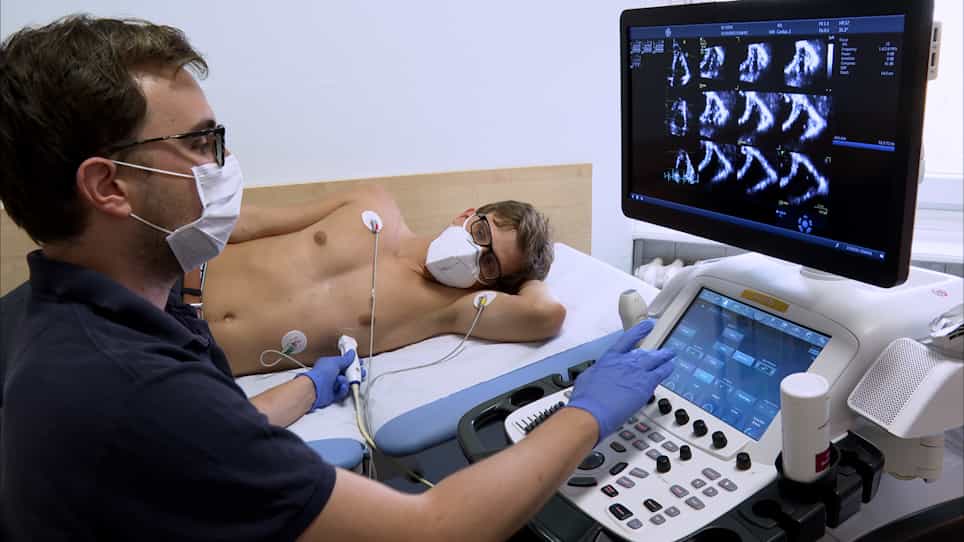

Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Right ventricular function declines prior to left ventricular ejection fraction in hypertrophic cardiomyopathy
Masliza Mahmod1, Betty Raman2, Kenneth Chan2
1Division of Cardiovascular Medicine, Radcliffe Department of Medicine, University of Oxford Centre for Clinical Magnetic Resonance Research (OCMR), University of Oxford, John Radcliffe Hospital, Headley Way, Oxford, OX3 9DU, UK. Masliza.mahmod@cardiov.ox.ac.uk.

Background:
The right ventricle (RV) in hypertrophic cardiomyopathy (HCM) tends to be neglected, as previous efforts have predominantly focused on examining the prognostic value of left ventricular (LV) abnormalities. The objectives of this study were to assess RV function in HCM, changes over time, and association with clinical outcomes.
Methods:
Two hundred and ninety HCM patients with preserved LV ejection fraction (LVEF ≥ 55%) and 30 age- and sex-matched controls underwent cardiovascular magnetic resonance (CMR). All patients were followed up for clinical events for a median duration of 4.4 years. Sixty-three patients had a follow-up CMR undertaken at a median interval of 5.4 years. Main study measures and outcomes were RV function (RV ejection fraction (RVEF) and RV strain) at baseline, temporal changes in RV function over time and prognostic value of RV dysfunction for predicting cardiovascular outcomes in HCM.
Results:
When compared to controls, HCM patients exhibited lower RV and LV peak global longitudinal systolic strains on feature-tracking analysis of cine images, while RVEF and LVEF were within the normal range. On follow-up CMR, both RV and LV strain parameters decreased over time. RVEF decreased at follow-up (65 ± 7% to 62 ± 7%, P < 0.001) but the change in LVEF was not significant (68 ± 10% to 66 ± 8%, P = 0.30). On clinical follow up, reduced RVEF was an independent predictor of non-sustained ventricular tachycardia (NSVT) [HR 1.10 (95% CI 1.06-1.15), P < 0.001] and composite cardiovascular events (NSVT, stroke, heart failure hospitalisation and cardiovascular death) [HR 1.07 (95% CI 1.03-1.10), P < 0.001]. RV longitudinal strain was an independent predictor of NSVT [HR 1.05 (95% CI 1.01-1.09), P = 0.029]. Patients with RVEF < 55% showed an increased risk of NSVT and composite cardiovascular events. In contrast, LVEF and LV global longitudinal strain were not predictive of such events on multivariable analysis.
Conclusions:
In HCM, RV function, including RV strain, and LV strain decrease over time despite preserved LVEF. Reduction in RV but not LV function is associated with adverse cardiovascular outcomes. Assessing RV function in early HCM disease might have a role in risk stratification to prevent future cardiovascular events.
More Related Videos
 08:21
Biventricular Assessment of Cardiac Function and Pressure-Volume Loops by Closed-Chest Catheterization in Mice
Published on: June 15, 2020
 07:38
Comprehensive Echocardiographic Assessment of Right Ventricle Function in a Rat Model of Pulmonary Arterial Hypertension
Published on: January 20, 2023
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Heart Failure II: Pathophysiology
 01:20
Mitral Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:17
Pathophysiology of Heart Failure
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...