Related Experiment Video
Updated: Sep 7, 2025
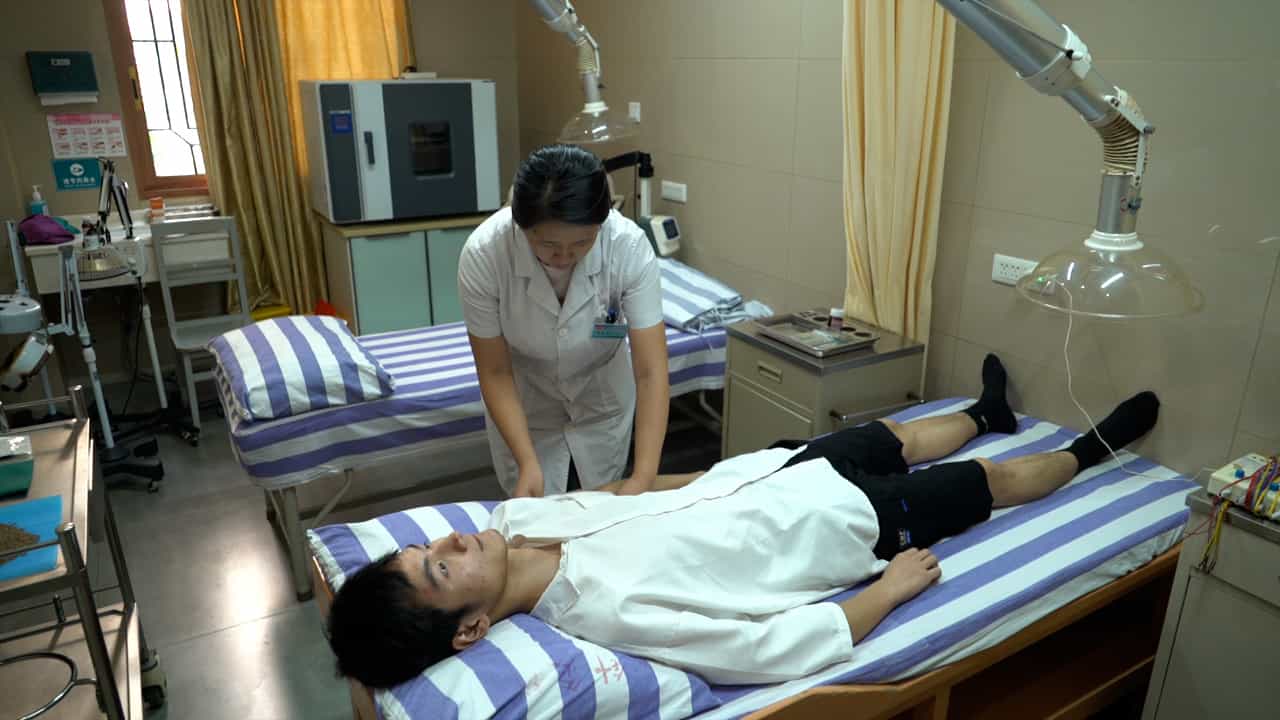

Electroacupuncture Combined with Chinese Medicine Ironing Therapy for Functional Constipation
Published on: July 5, 2024
Fecal disimpaction in children with enuresis and constipation does not make them dry at night
Malin Borgström1, Amadeus Bergsten2, Maria Tunebjer2
1Department of Women's and Children's Health, Uppsala University, Sweden; Center for Clinical Research Dalarna, Falun, Sweden.

Insights
Fecal disimpaction for constipation in children with nocturnal enuresis did not improve bedwetting. Addressing bowel issues is important, but this method alone does not cure enuresis.
Area of Science:
- Pediatric Urology
- Gastroenterology
- Sleep Medicine
Background:
- Nocturnal enuresis and constipation frequently coexist in children.
- Constipation management is crucial for daytime incontinence, but its impact on enuresis is less understood.
- The efficacy of fecal disimpaction for enuresis in constipated children remains unevaluated.
Purpose of the Study:
- To assess the effect of fecal disimpaction on nocturnal enuresis in children with co-occurring constipation.
- To determine if clearing fecal impaction can reduce enuresis frequency.
Main Methods:
- Noninvasive assessment of bladder and bowel function in children (6-10 years) with new-onset enuresis.
- Constipation diagnosed via Rome IV criteria or rectal diameter >30mm (ultrasound).
- Treatment involved mini-enemas and macrogol for at least two weeks; enuresis frequency recorded before and after.
Main Results:
- 23 out of 66 children (35%) were constipated; no baseline differences in age, sex, or bladder function.
- Enuresis frequency averaged 9.8 nights/2 weeks before and 9.3 nights/2 weeks after constipation therapy (p=0.43).
- Fecal disimpaction did not significantly alter enuresis frequency.
Conclusions:
- Fecal disimpaction alone does not resolve nocturnal enuresis in constipated children.
- While bowel issues require attention, this treatment does not guarantee nighttime dryness.
- Evidence-based enuresis therapies may require addressing underlying bowel problems first for optimal efficacy.
Background:
Constipation, daytime incontinence and nocturnal enuresis often overlap. Treatment of constipation has been shown to be an important aspect of therapy for children with daytime incontinence. However, the value of fecal disimpaction, as a part of constipation therapy, in children with enuresis has not been evaluated.
Aim:
Our aim was to evaluate the antienuretic effect of fecal disimpaction in children with enuresis and concomitant constipation.
Methods:
The bladder and bowel function was assessed noninvasively in children aged six to ten years who sought help for enuresis for the first time. If they were constipated according to the Rome IV criteria or had a rectal diameter exceeding 30 mm, as assessed by ultrasound, they were given standard evacuation with mini-enemas and macrogol therapy for at least two weeks. Enuresis frequency was documented 14 nights preceding and following therapy.
Results:
In total, 66 children (20 girls, 46 boys) were evaluated, 23 (35%) of whom were constipated. There were no differences in age, sex or baseline bladder function between the two groups. The enuresis frequency per two weeks was 9.8 ± 4.1 nights before and 9.3 ± 5.1 nights after constipation therapy (p = 0.43).
Discussion:
This study found that fecal disimpaction in children with enuresis who are also constipated did not alleviate nocturnal enuresis. Bowel problems may still need to be addressed but the child should not be given the false hope that this approach alone will make them dry at night. It might be that evidenced based therapies, such as the enuresis alarm and desmopressin, could be less efficient in children with enuresis and constipation unless their bowel disturbance is first properly addressed.
Conclusions:
Fecal disimpaction in children with enuresis and concomitant constipation will, by itself, not make the children dry at night.


Related Concept Videos
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 01:26
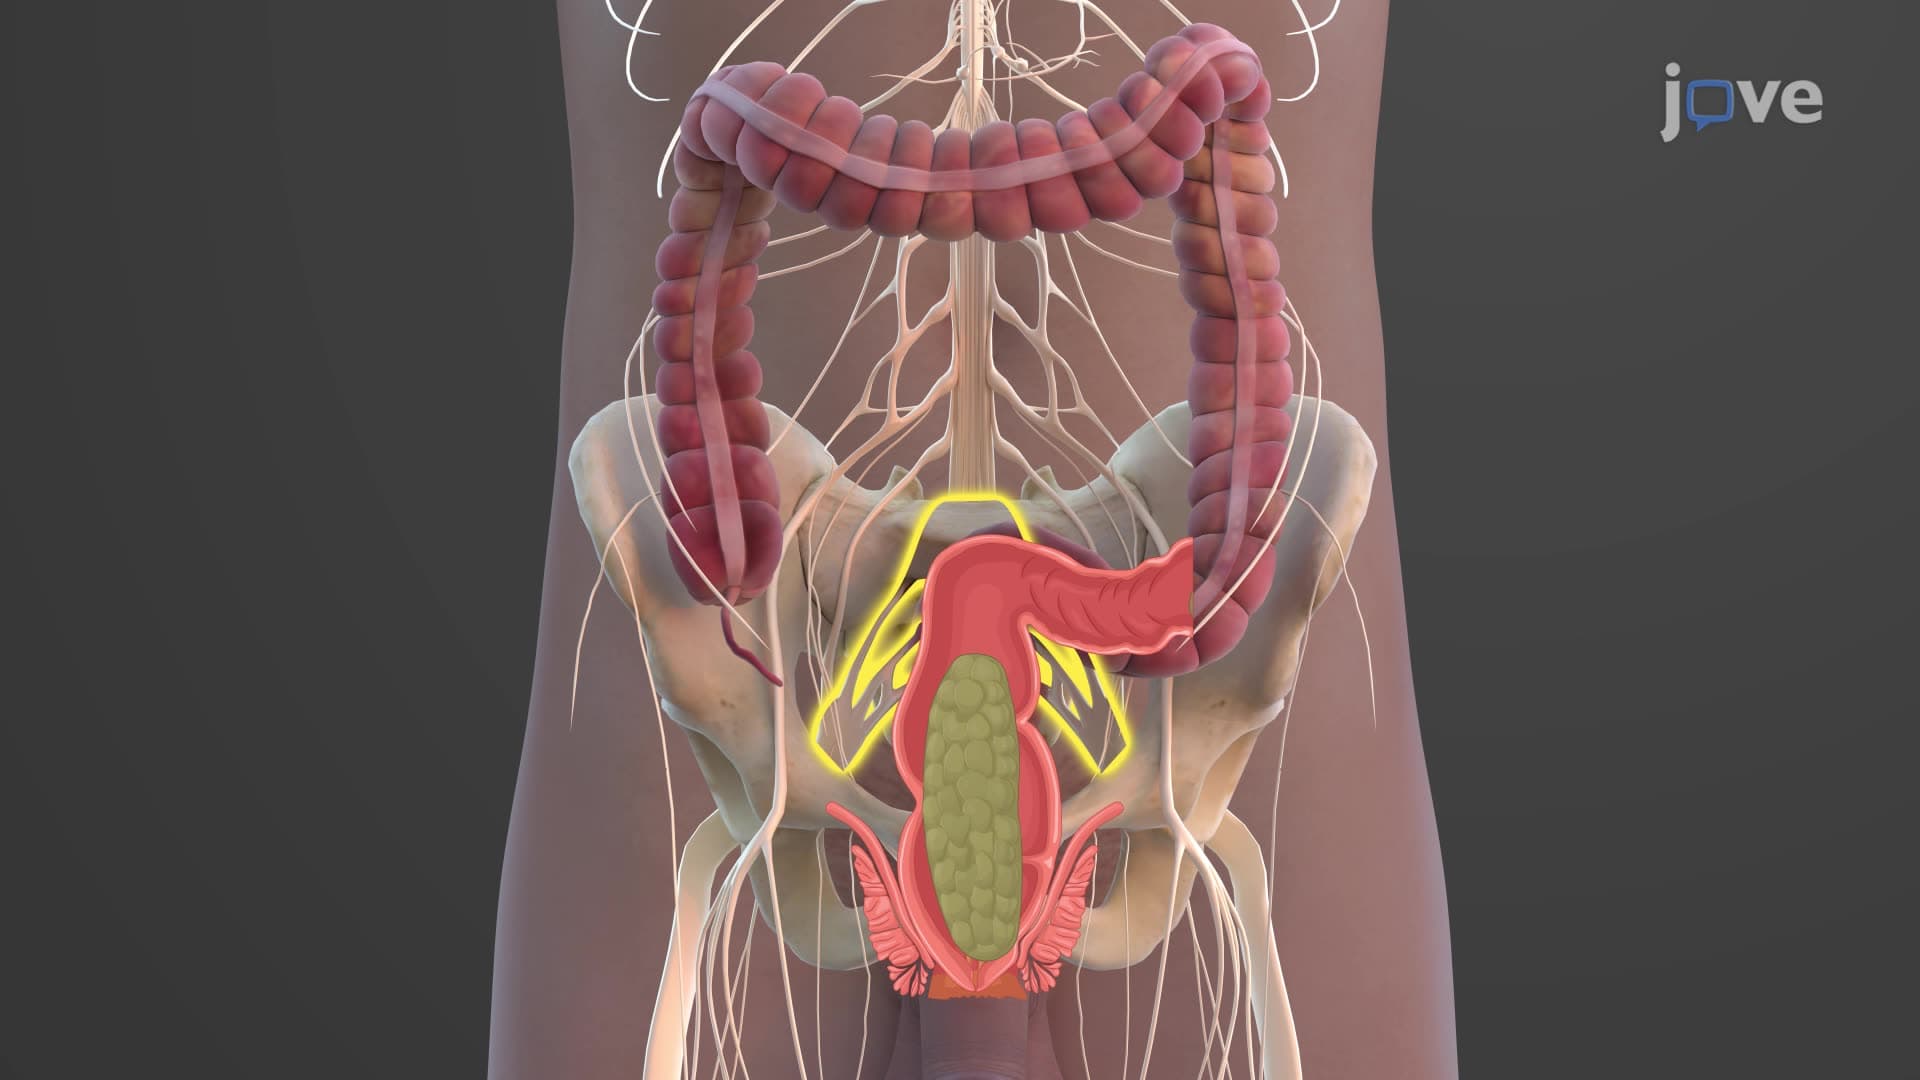
Feces Formation and Defecation
The mass peristalsis then pushes the feces into the rectum, which stretches the rectal walls to activate...
 01:20
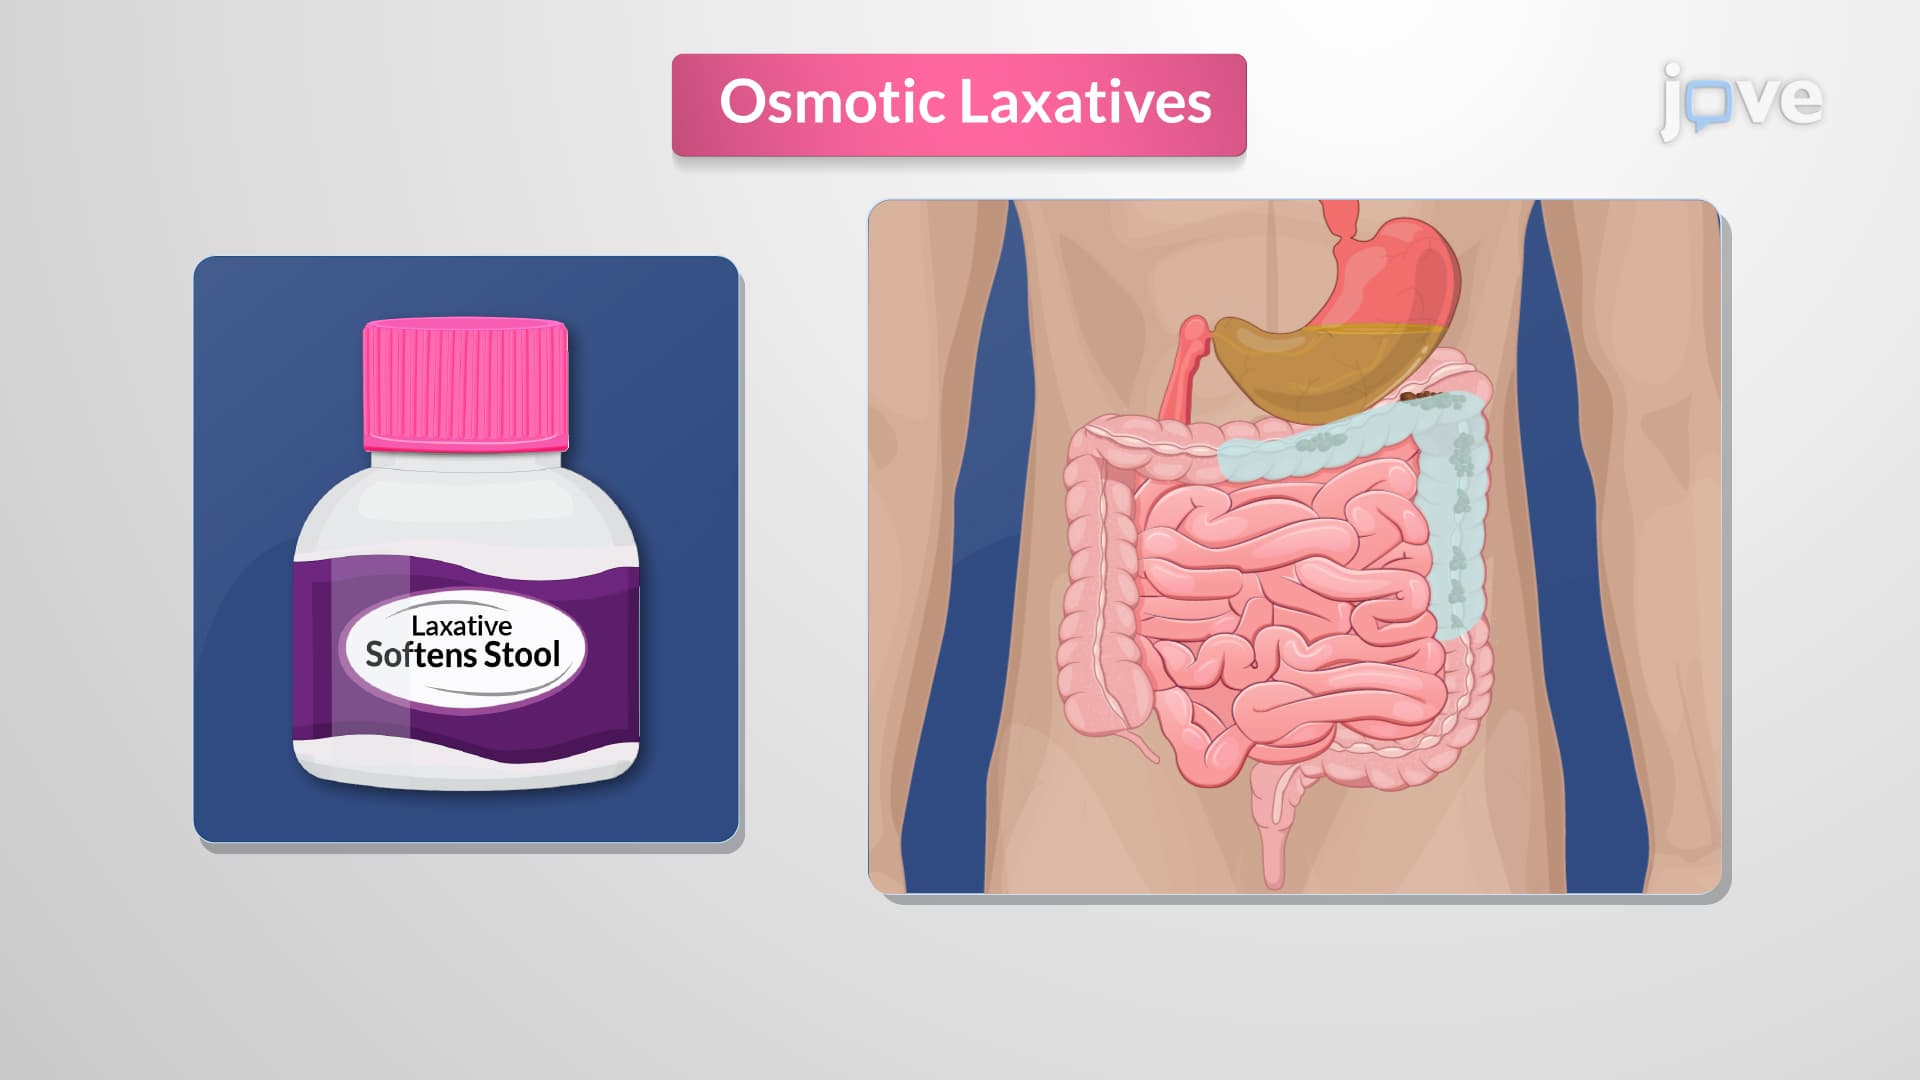
Drugs Affecting GI Tract Motility: Other Laxatives
Osmotic or saline laxatives, like magnesium hydroxide or milk of...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:22
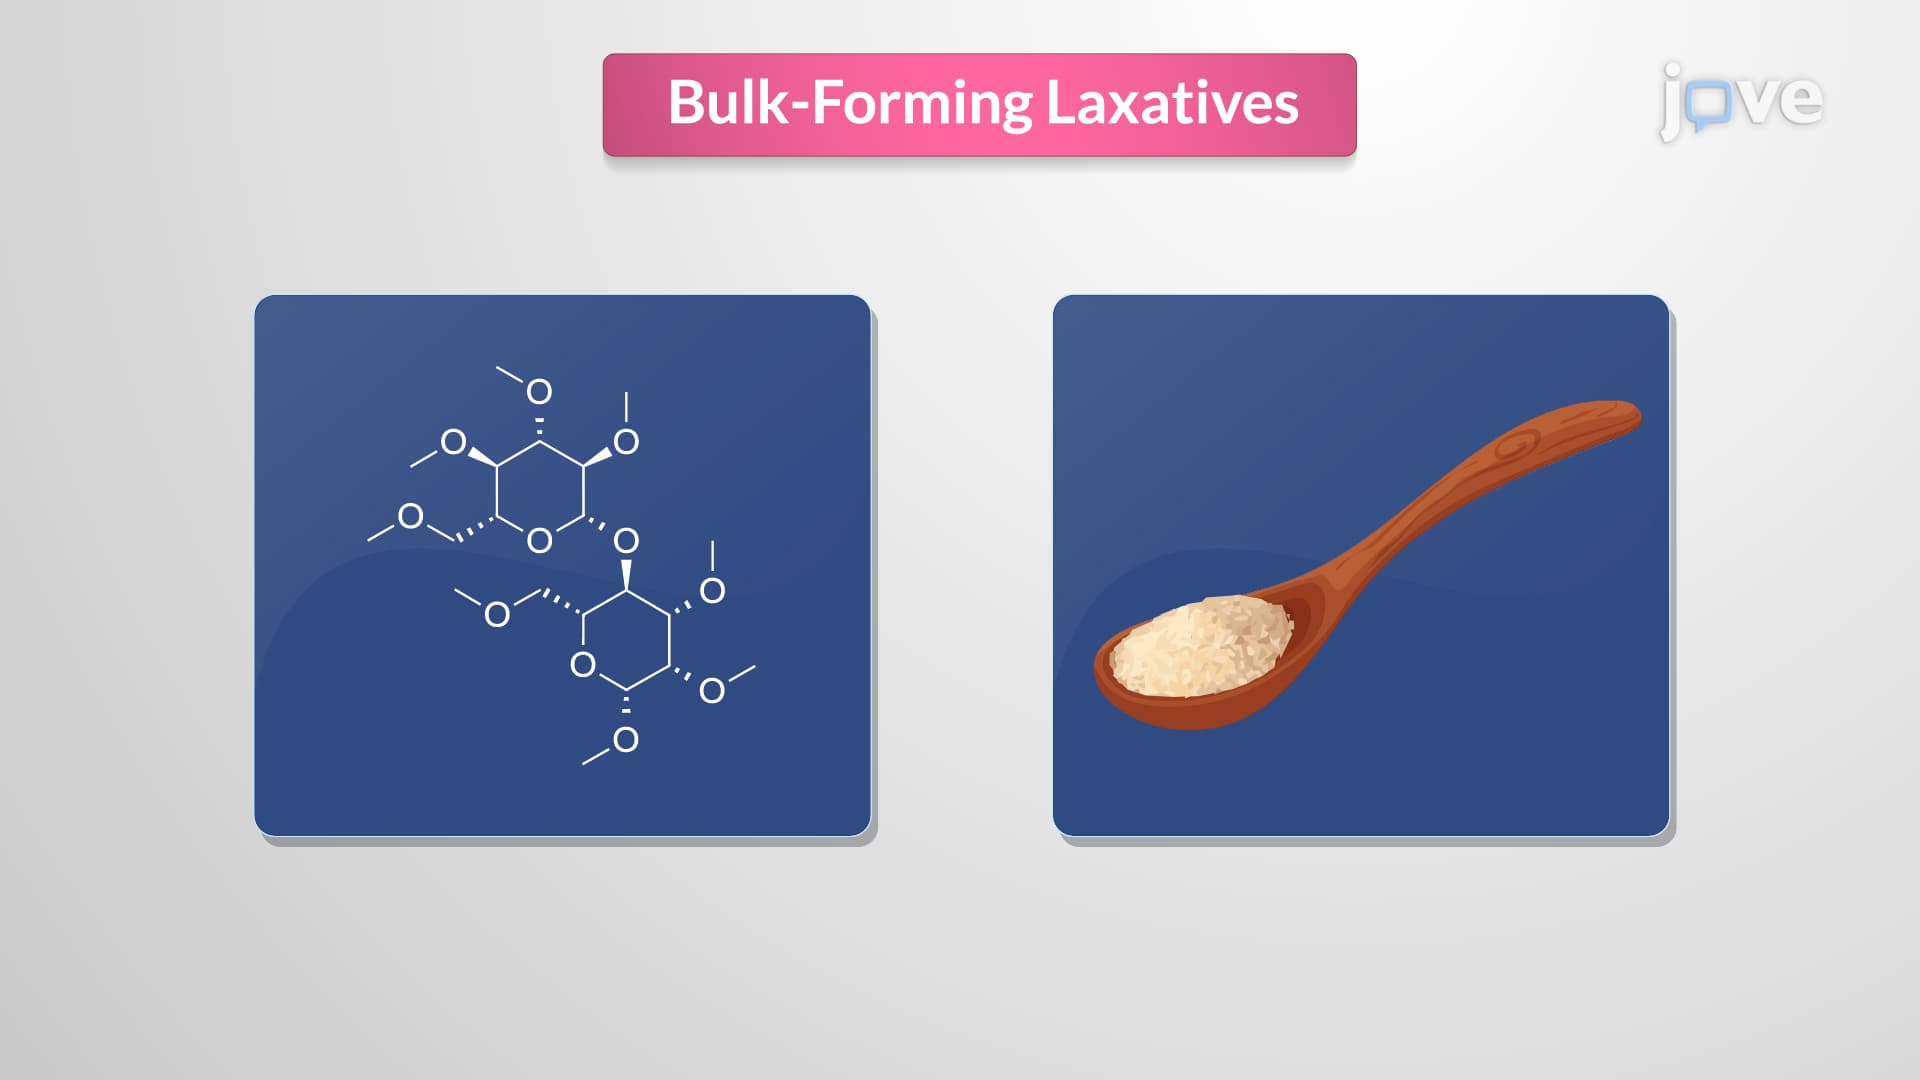
Drugs Affecting GI Tract Motility: Bulk-Forming and Stimulant Laxatives
Bulk-forming laxatives, such as psyllium, methylcellulose, and polycarbophil, absorb water in the intestine, increasing stool bulk and promoting bowel movement. This...