Related Experiment Video
Updated: Sep 6, 2025
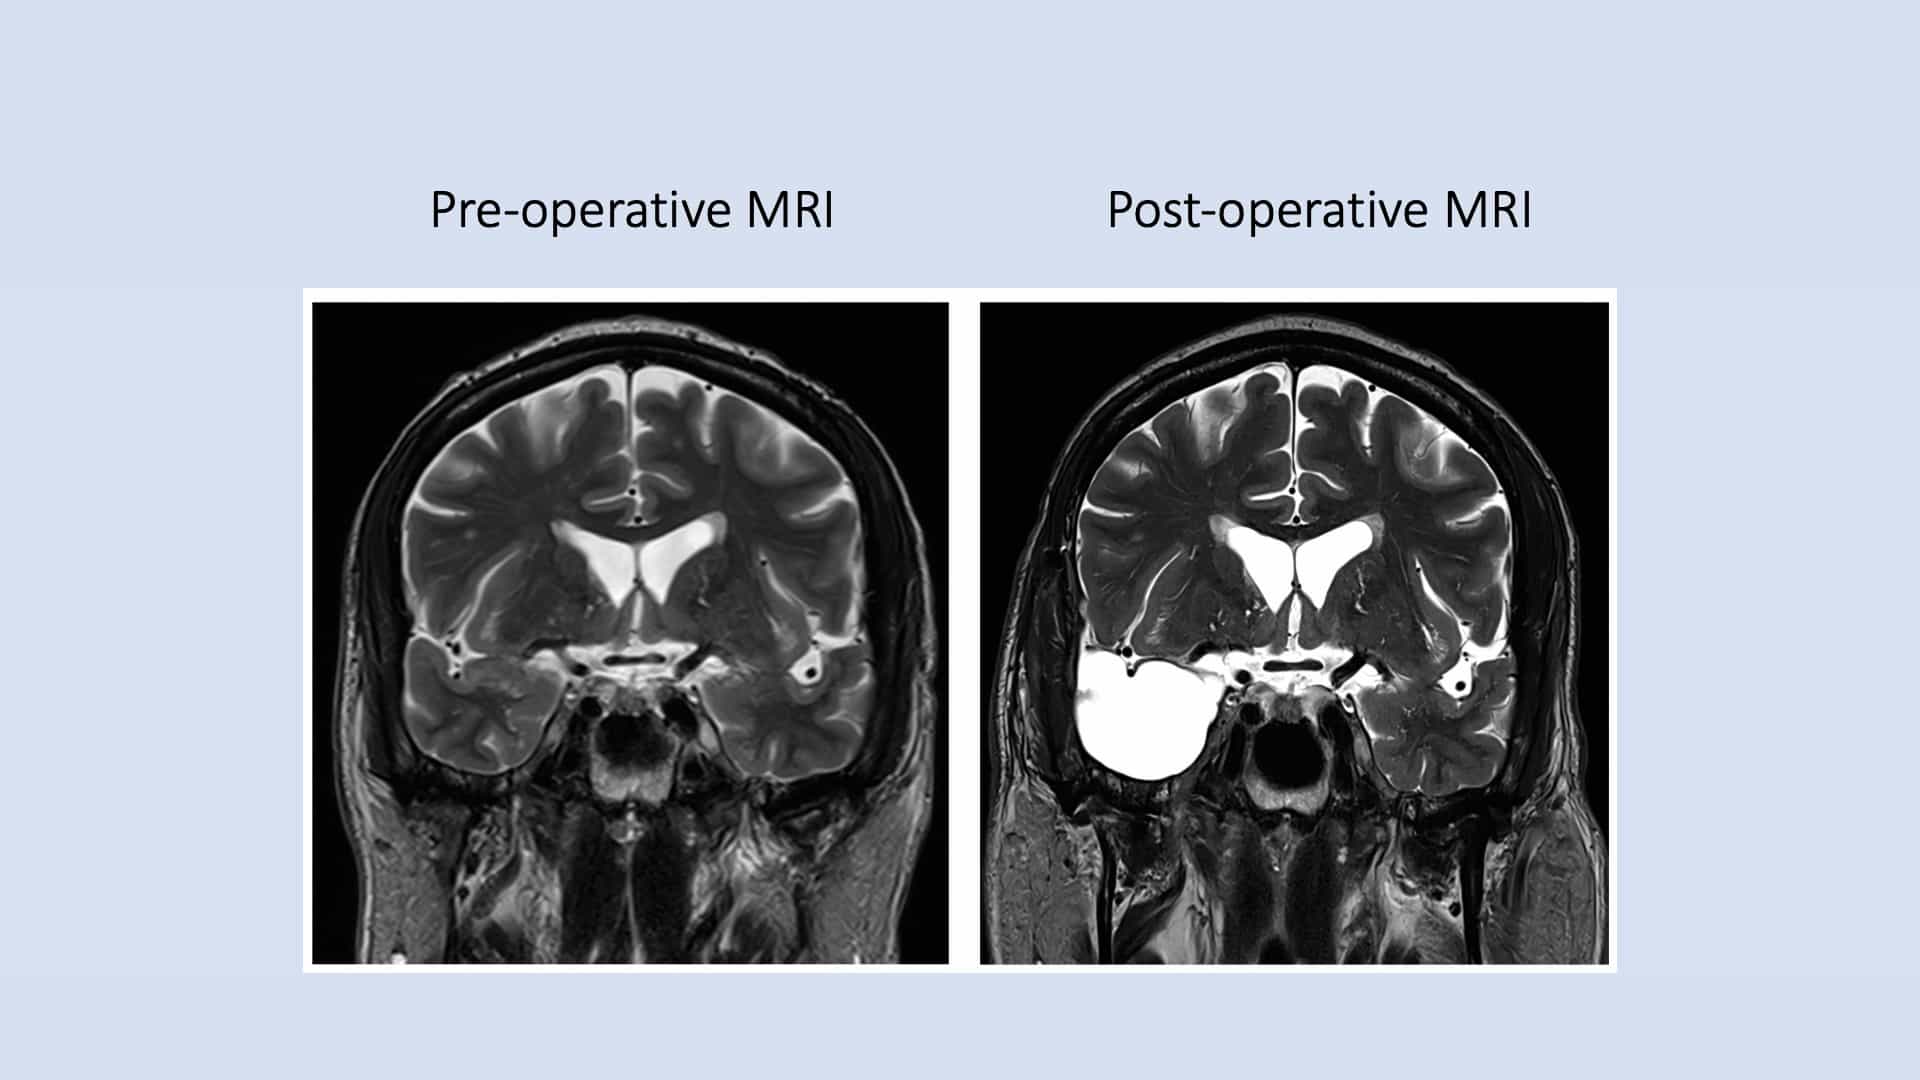

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
A Retrospective Study of Parietal Lobe Epilepsy: Functional Anatomy and Surgical Treatment

Context:
Parietal lobe epilepsy (PLE) accounts for approximately 5% of all focal epilepsies worldwide,1 and few PLE patients have undergone epilepsy surgery in the past. With the introduction of functional neuroimaging methods, such as interictal fluorodeoxyglucose-positron emission tomography (FDG-PET), stereotactic electroencephalograms (SEEGs), and high-resolution magnetic resonance imaging (MRI), more patients with intractable neocortical epilepsy have been considered for surgical treatment.
Objective:
The study intended to characterize the clinical features, aura, and presurgical evaluations of patients with PLE, by investigating their demographic and clinical characteristics, and to evaluate the prognostic value of the four diagnostic modalities-MRI, FDG-PET, scalp EEG, and SEEG-in terms of the localization of epileptogenic area.
Design:
The research team performed a retrospective analysis of outcomes for PLE patients who underwent resistive brain surgery.
Setting:
The study took place in the Neurosurgery Department of Epilepsy at the Second Hospital of Hebei Medical University in Shijiazhuang, China.
Participants:
Participants were 9 PLE patients, 4 males and 5 females, who underwent epilepsy surgery at the hospital between 2017 and 2019.
Outcome Measures:
The measures included demographic data, seizure data, electroencephalogram (EEG) recordings, magnetic resonance imaging (MRI) of the brain, positron emission tomography (PET), and stereotactic electroencephalogram (SEEG). The pathological findings were reviewed.
Results:
The five participants who had a PET all had positive results. Eight participants who had parietal lobe lesions had an MRI, and four had a stereotactic electroencephalogram (SEEG) that localized the epileptogenic zone. The interictal scalp EEG recordings for seven participants showed an abnormality, and six participants who had ictal surface EEG recordings showed parietal ictal EEG onset.
Conclusions:
Surgical excision of epileptogenic foci is the main treatment for drug-resistant PLE. Parietal functional anatomy is the basis for understanding and diagnosing PLE. Aura, semiology, interictal EEG, and PET are an important foundation for evaluation of PLE patients, and the SEEG is the most valuable tool, allowing localization of the epileptogenic zone.
More Related Videos
 09:32
Network Analysis of Foramen Ovale Electrode Recordings in Drug-resistant Temporal Lobe Epilepsy Patients
Published on: December 18, 2016
 09:00
Investigating the Function of Deep Cortical and Subcortical Structures Using Stereotactic Electroencephalography: Lessons from the Anterior Cingulate Cortex
Published on: April 15, 2015