Related Experiment Video
Updated: Sep 6, 2025


In Vivo Real-Time Study of Drug Effects on Carotid Blood Flow in the Ovine Fetus
Published on: April 28, 2023
Efficacy and Safety of Various First-Line Therapeutic Strategies for Fetal Tachycardias: A Network Meta-Analysis and
Jiangwei Qin1, Zhengrong Deng1, Changqing Tang2
1Key Laboratory of Birth Defects and Related Diseases of Women and Children of MOE, Department of Pediatrics, West China Second University Hospital, Sichuan University, Chengdu, China.

Abstract:
Background: Fetal arrhythmias are common cardiac abnormalities associated with high mortality due to ventricular dysfunction and heart failure, particularly when accompanied by hydrops. Although several types of common fetal tachycardias have been relatively identified medications, such as digoxin, flecainide, and sotalol, there is no first-line drug treatment protocol established for the treatment of various types of fetal tachycardias. Methods: We conducted a network meta-analysis using a Bayesian hierarchical framework to obtain a model for integrating both direct and indirect evidence. All tachycardia types (Total group), supraventricular tachycardia (SVT subgroup), atrial flutter (AF subgroup), hydrops subgroup, and non-hydrops subgroup fetuses were analyzed, and five first-line regimens were ranked according to treatment outcomes: digoxin monotherapy (D), flecainide monotherapy (F), sotalol monotherapy (S), digoxin plus flecainide combination therapy (DF), and digoxin plus sotalol combination therapy (DS). Effectiveness and safety were determined according to the cardioversion rate and intrauterine death rate. Results: The pooled data indicated that DF combination therapy was always superior to D monotherapy, regardless of the tachycardia type or the presence of hydrops: Total, 2.44 (95% CrI: 1.59, 3.52); SVT, 2.77 (95% CrI: 1.59, 4.07); AF, 67.85 (95% CrI: 14.25, 168.68); hydrops, 6.03 (95% CrI: 2.54, 10.68); and non-hydrops, 5.06 (95% CrI: 1.87, 9.88). DF and F had a similar effect on control of fetal tachycardias. No significant differences were observed when comparing S, DS with D therapies across the subgroup analyses for the SVT, hydrops, and non-hydrops groups. No significant differences in mortality risks were among the various treatment regimens for the total group. And no significant differences were found in rates of intrauterine death rates at the same cardioversion amount. Conclusion The flecainide monotherapy and combination of digoxin and flecainide should be considered the most superior therapeutic strategies for fetal tachycardia. Systematic Review Registration: (https://www.crd.york.ac.uk/PROSPERO/display_record.php?RecordID=288997), identifier (288997).
More Related Videos
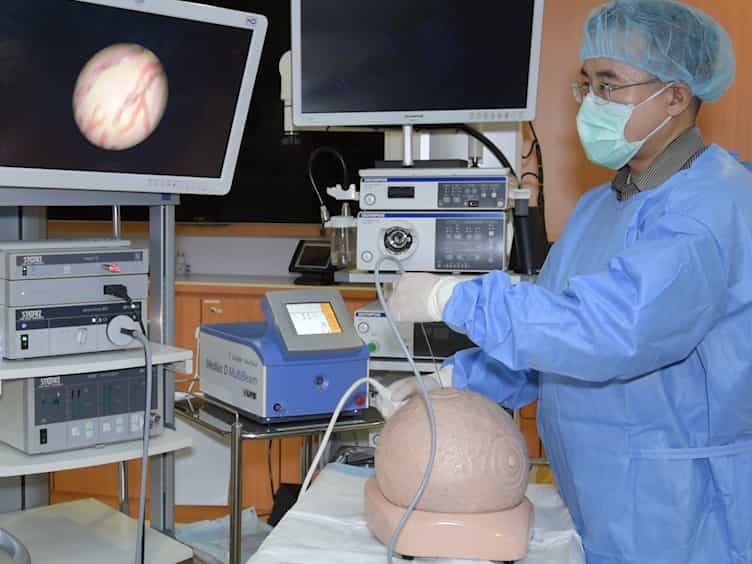 09:51
Model Surgical Training: Skills Acquisition in Fetoscopic Laser Photocoagulation of Monochorionic Diamniotic Twin Placenta Using Realistic Simulators
Published on: March 21, 2018
 07:34
Fetal Mouse Cardiovascular Imaging Using a High-frequency Ultrasound 30/45MHZ System
Published on: May 5, 2018
Related Concept Videos
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:26
Heart Failure Drugs: Inotropic Agents