Related Experiment Video
Updated: Sep 6, 2025


A Modified Sonographic Algorithm for Image Acquisition in Life-Threatening Emergencies in the Critically Ill Newborn
Published on: April 7, 2023
Determinants of mortality and intensive care requirement in pediatric thoracoabdominal injuries
Fatma Akgül1, Anıl Er1, Aykut Çağlar1
1Department of Pediatric Emergency Care, Dokuz Eylül University Faculty of Medicine, İzmir-Türkiye.

Insights
Thoracoabdominal injuries in children are serious, often caused by blunt trauma. Lower scores on the Pediatric Trauma Score (PTS) and Glasgow Coma Scale (GCS), along with multiple injuries, indicate higher mortality risk.
Area of Science:
- Pediatric Trauma Surgery
- Emergency Medicine
- Critical Care Pediatrics
Background:
- Thoracoabdominal injuries (TAI) represent a significant cause of morbidity and mortality in pediatric trauma patients.
- Prompt and accurate medical intervention is crucial for improving outcomes in children with TAI.
- This study investigates factors influencing mortality and intensive care unit (ICU) admission in pediatric TAI cases.
Purpose of the Study:
- To identify key factors associated with mortality in pediatric thoracoabdominal injuries.
- To determine predictors for the need for intensive care unit (ICU) admission in children with TAI.
- To enhance clinical awareness and management strategies for severe pediatric trauma.
Main Methods:
- A retrospective analysis of pediatric patients admitted with TAI over a six-year period.
- Data collected included demographics, injury mechanisms, clinical presentations, laboratory results, imaging findings, and treatment outcomes.
- Survival status, length of hospital stay, and ICU utilization were systematically recorded.
Main Results:
- The study included 136 children, with blunt trauma (92.7%) and motor vehicle accidents (52.2%) being the most common causes.
- Pulmonary contusion, pneumothorax, splenic, and liver injuries were prevalent diagnoses.
- Lower Glasgow Coma Scale (GCS) and Pediatric Trauma Scores (PTS), multiple injuries, pulmonary contusion, and pneumothorax were significantly associated with increased ICU admission and mortality.
Conclusions:
- TAI, though less common in children, contributes significantly to pediatric trauma mortality.
- Physicians should maintain high vigilance for serious injuries indicated by multiple traumas, pulmonary contusion, pneumothorax, and low GCS/PTS scores.
- Early recognition of these indicators is vital for timely and effective management of pediatric thoracoabdominal trauma.
Background:
Thoracoabdominal injuries (TAI) are an important cause of trauma-related morbidity in children. Early and correct intervention is essential to reduce mortality. We aimed to determine factors associated with mortality and the need for intensive care in TAI.
Methods:
The children admitted to the pediatric emergency department of a tertiary care hospital with TAI in a 6-year-period were enrolled. Demographic data; mechanism of injuries; clinical, laboratory and imaging findings; length of hospital and intensive care unit (ICU) stay; invasive procedures and medical treatments; surgical interventions; and survival outcomes were recorded.
Results:
The median age of the 136 children was 9 (IQR: 5-14) years and 72.8% were male. The vast majority of injuries were caused by blunt trauma (92.7%). Pulmonary contusion, pneumothorax, splenic, and liver injuries were the most common diagnoses. Motor vehicle accidents were seen in more than half of the cases (52.2%). The median length of hospital stay was 5 (IQR: 2-8) days; 21 patients were hospitalized in the ICU (15.4%). The need for intensive care was higher in patients with lower Glasgow Coma Scale (GCS) scores and lower Pediatric Trauma Scores (PTSs), in the presence of multiple injuries, pulmonary contusion, and pneumothorax (p<0.001). Mortality was seen in nine patients, eight of whom had multiple injuries. The mortality rate was higher in patients with pulmonary contusion and pneumothorax (p=0.002 and p=0.003, respectively). The PTS and GCS were found to be lower in patients who died in hospital (p<0.001). Prolongation of coagulation parameters and hyperglycemia was more common in the non-survivor group (p=0.005 and p=0.004, respectively).
Conclusion:
Although thoracoabdominal trauma is not common in childhood, it is an important part of trauma-associated mortality. Multiple injuries, pulmonary contusion, pneumothorax, lower GCS, and PTSs can be a sign of serious injuries to which physicians must be alert.


Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
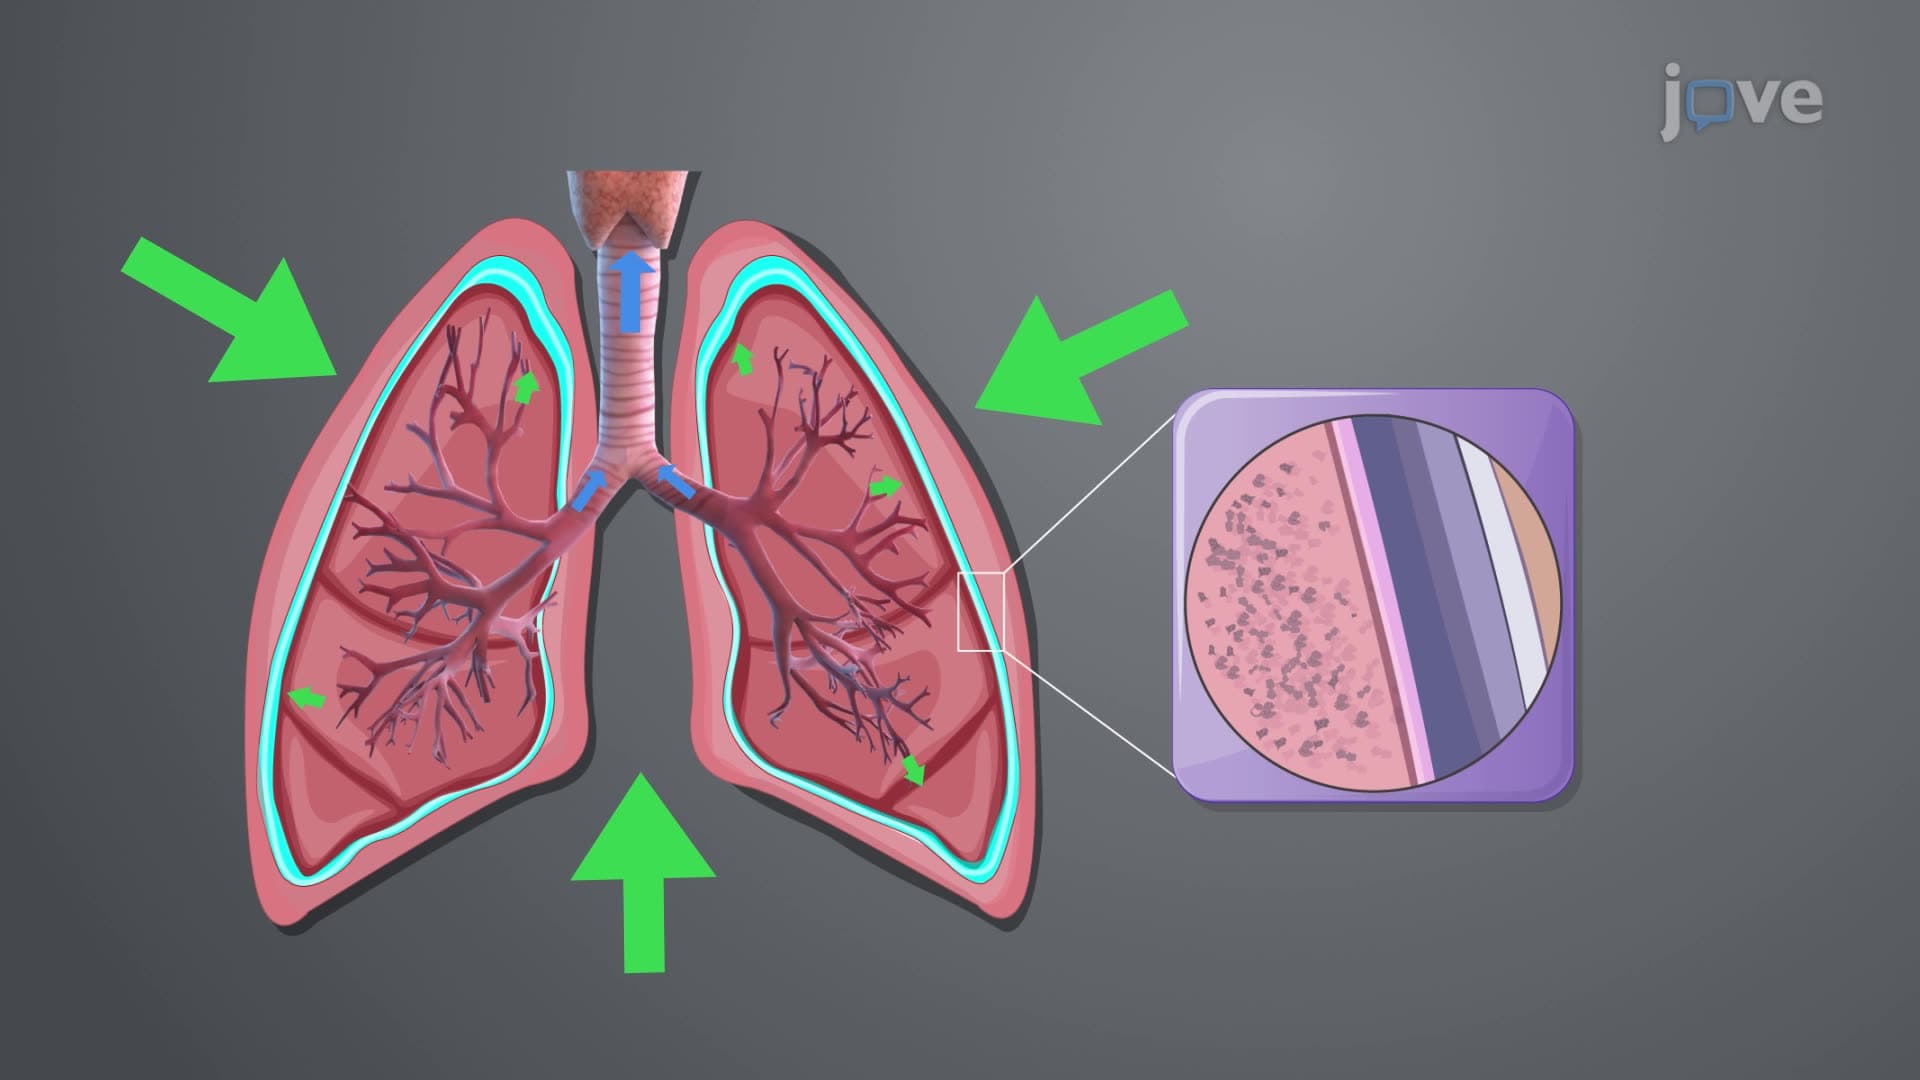 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...