Related Experiment Video
Updated: Sep 5, 2025
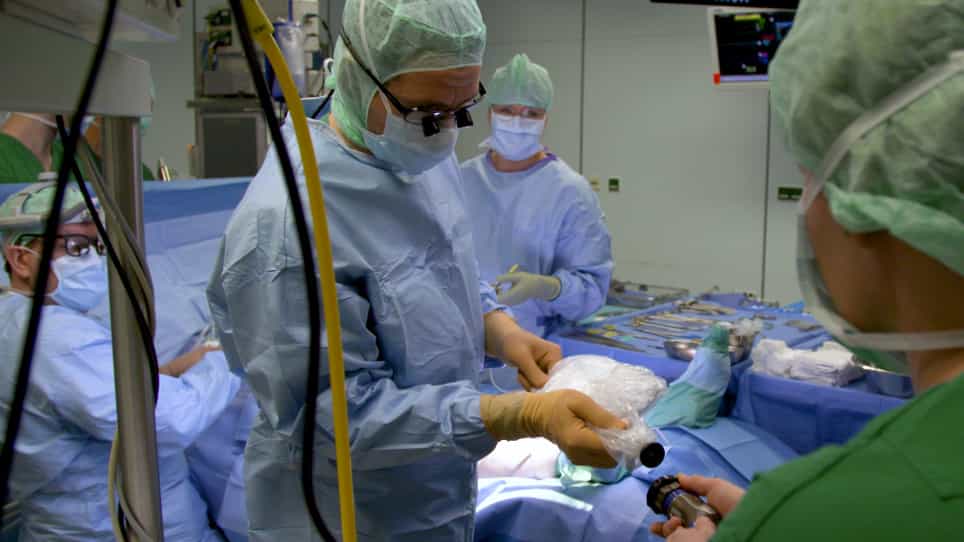

Synergizing Antegrade Endoscopic with Bridging Vein Harvesting for Improvement of Great Saphenous Vein Graft Quality from the Lower Leg
Published on: November 19, 2019
Utilizing a lower extremity vein graft for immediate lymphatic reconstruction
Rosie Friedman1, Valeria P Bustos1, Tanya Postian1
1Division of Plastic and Reconstructive Surgery, Beth Israel Deaconess Medical Center, Harvard Medical School, Boston, MA, USA.

Immediate lymphatic reconstruction (ILR) is targeted at preventing breast cancer related lymphedema (BCRL) by anastomosing disrupted arm lymphatic channels to axillary vein tributaries. Inadequate vein length and venous back-bleeding are two technical reasons that lead to ILR procedures being aborted intraoperatively. Recently, our team began routinely harvesting a lower extremity vein graft (LEVG) for all ILR procedures to reduce our abort rate. We describe the surgical approach of an LEVG and evaluate the effects on aborted case rates and intraoperative time. A retrospective review of our institutional lymphatic database was conducted. Two hundred and forty-seven breast cancer patients were taken to the operating room for attempted ILR in the past 5 years. Prior to the use of an LEVG (n = 205), our abort rate was 14%. Since routinely performing an LEVG with ILR (n = 42), we have not aborted a single case. Despite an LEVG requiring one additional anastomosis to connect the vein graft to the native axillary vein tributary, this technique has not changed the intraoperative time for ILR procedures. In this technical contribution, we describe our early experience performing immediate lymphatic reconstruction utilizing a lower extremity vein graft. Implementation of this technique appears to have promising effects on aborted case rates without affecting intraoperative time, and greatly facilitates the lymphovenous anastomosis.
Immediate lymphatic reconstruction (ILR) is targeted at preventing breast cancer related lymphedema (BCRL) by anastomosing disrupted arm lymphatic channels to axillary vein tributaries. Inadequate vein length and venous back-bleeding are two technical reasons that lead to ILR procedures being aborted intraoperatively. Recently, our team began routinely harvesting a lower extremity vein graft (LEVG) for all ILR procedures to reduce our abort rate. We describe the surgical approach of an LEVG and evaluate the effects on aborted case rates and intraoperative time. A retrospective review of our institutional lymphatic database was conducted. Two hundred and forty-seven breast cancer patients were taken to the operating room for attempted ILR in the past 5 years. Prior to the use of an LEVG (n = 205), our abort rate was 14%. Since routinely performing an LEVG with ILR (n = 42), we have not aborted a single case. Despite an LEVG requiring one additional anastomosis to connect the vein graft to the native axillary vein tributary, this technique has not changed the intraoperative time for ILR procedures. In this technical contribution, we describe our early experience performing immediate lymphatic reconstruction utilizing a lower extremity vein graft. Implementation of this technique appears to have promising effects on aborted case rates without affecting intraoperative time, and greatly facilitates the lymphovenous anastomosis.


Related Concept Videos
 01:15
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:25
Hemodialysis I: Introduction
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...