Related Experiment Video
Updated: Sep 3, 2025
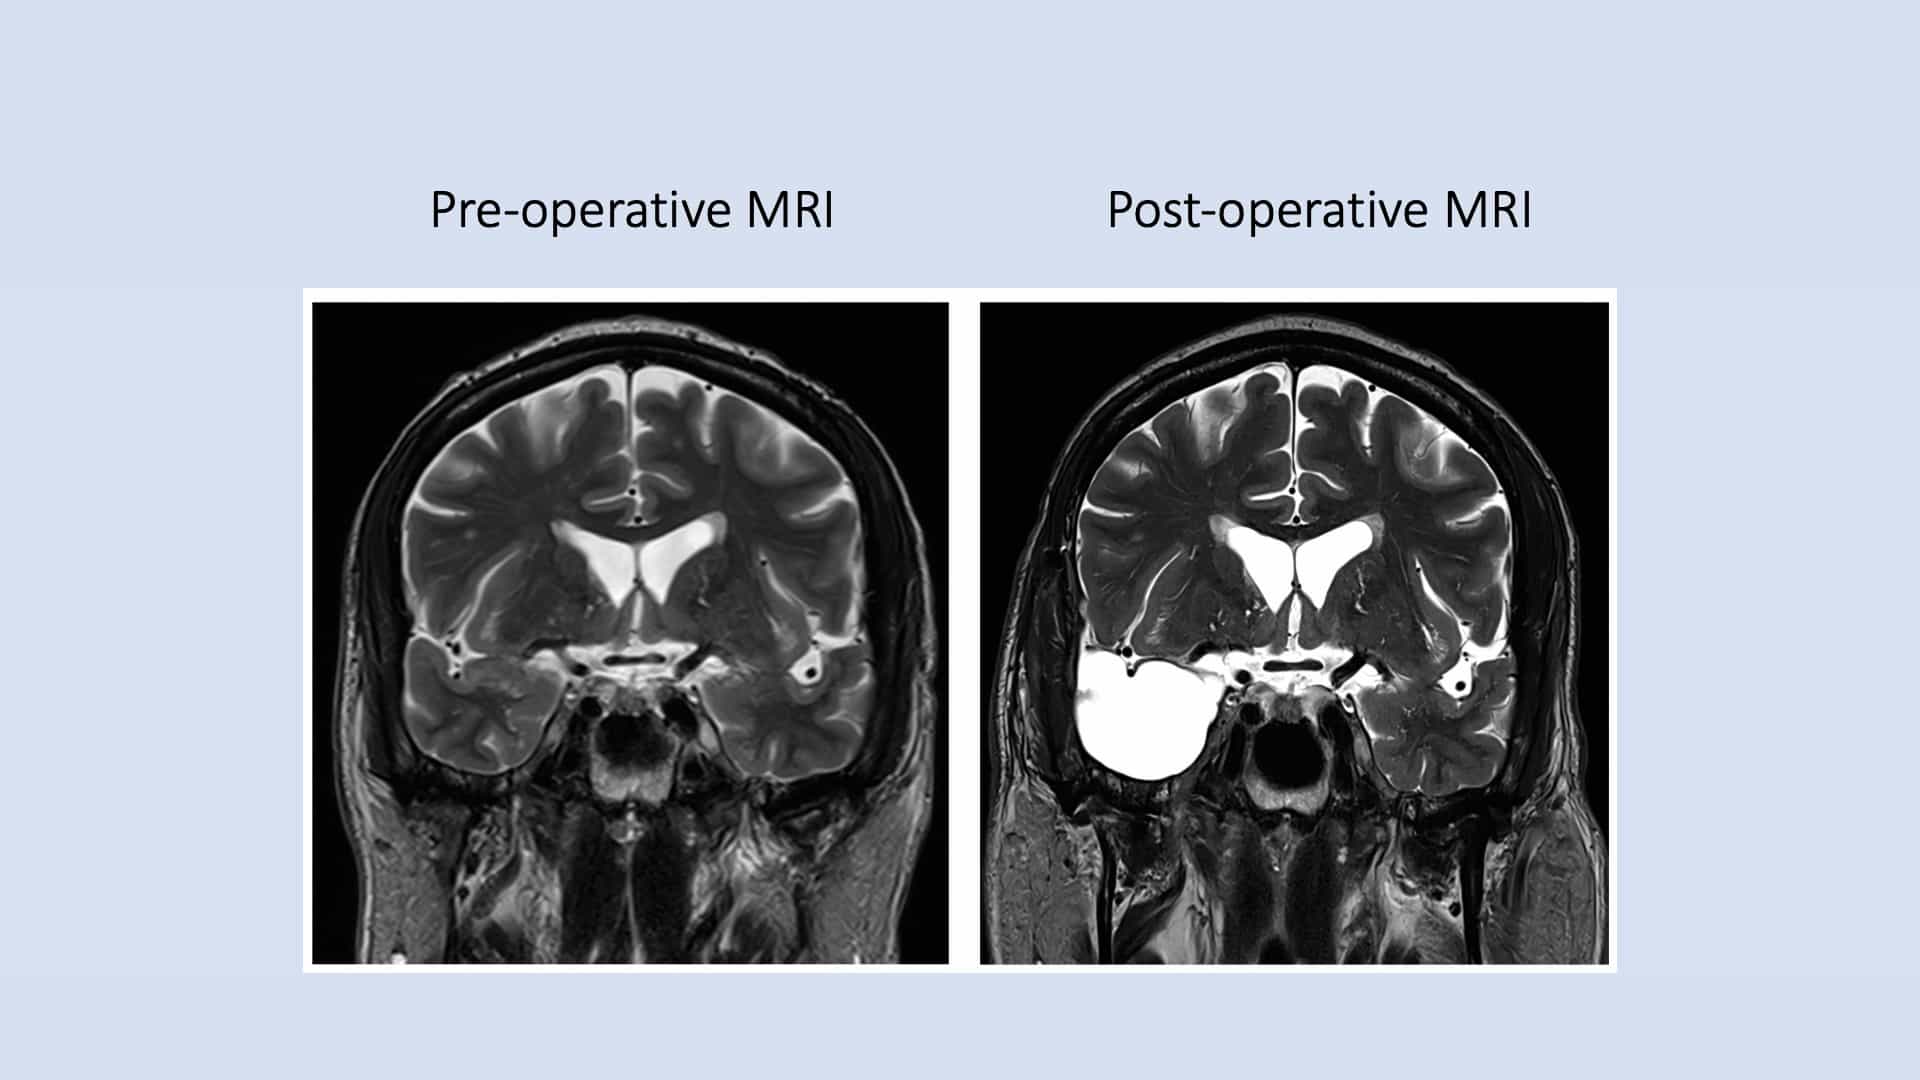
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Seizure-free outcome and safety of repeated epilepsy surgery for persistent or recurrent seizures
Mathias Kunz1, Philipp Karschnia1, Ingo Borggraefe2
11Department of Neurosurgery, University Hospital of the Ludwig-Maximilians-University of Munich.

Objective:
Reoperation may be an option for select patients with unsatisfactory seizure control after their first epilepsy surgery. The aim of this study was to describe the seizure-free outcome and safety of repeated epilepsy surgery in our tertiary referral center.
Methods:
Thirty-eight patients with focal refractory epilepsy, who underwent repeated epilepsy surgeries and had a minimum follow-up time of 12 months after reoperation, were included. Systematic reevaluation, including comprehensive neuroimaging and noninvasive (n = 38) and invasive (n = 25, 66%) video-electroencephalography monitoring, was performed. Multimodal 3D resection maps were created for individual patients to allow personalized reoperation.
Results:
The median time between the first operation and reoperation was 74 months (range 5-324 months). The median age at reoperation was 34 years (range 1-74 years), and the median follow-up was 38 months (range 13-142 months). Repeat MRI after the first epilepsy surgery showed an epileptogenic lesion in 24 patients (63%). The reoperation was temporal in 18 patients (47%), extratemporal in 9 (24%), and multilobar in 11 (29%). The reoperation was left hemispheric in 24 patients (63%), close to eloquent cortex in 19 (50%), and distant from the initial resection in 8 (21%). Following reoperation, 27 patients (71%) became seizure free (Engel class I), while 11 (29%) continued to have seizures. There were trends toward better outcome in temporal lobe epilepsy and for unilobar resections adjacent to the initial surgery, but there was no difference between MRI lesional and nonlesional patients. In all subgroups, Engel class I outcome was at least 50%. Perioperative complications occurred in 4 patients (11%), with no fatalities.
Conclusions:
Reoperation for refractory focal epilepsy is an effective and safe option in patients with persistent or recurrent seizures after initial epilepsy surgery. A thorough presurgical reevaluation is essential for favorable outcome.
More Related Videos
 05:54
Stereo-Electro-Encephalo-Graphy SEEG With Robotic Assistance in the Presurgical Evaluation of Medical Refractory Epilepsy: A Technical Note
Published on: June 13, 2016
 04:50
Operative Technique and Nuances for the Stereoelectroencephalographic SEEG Methodology Utilizing a Robotic Stereotactic Guidance System
Published on: June 9, 2023
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types:
 01:20
Antiepileptic Drugs: Potassium Channel Activators
Ezogabine has gained approval as an adjunctive treatment...
 01:20
Antiepileptic Drugs: Modulators of Neurotransmitter Release Mediated by SV2A Protein
SV2A is a transmembrane glycoprotein located predominantly in the brain, modulating the release of neurotransmitters for neuronal communication. Both levetiracetam and brivaracetam exhibit a high affinity for...
 01:30
Electroconvulsive Therapy
 01:08
Antiepileptic Drugs: Sodium Channel Blockers
Sodium channel blockers modulate ion channels, particularly voltage-gated sodium channels. They block only sodium ion movement.
Among the most commonly prescribed antiepileptic drugs are...