Related Experiment Video
Updated: Sep 2, 2025


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Laparoscopic-Assisted Modified Posterior Sagittal Anorectoplasty for Rectobulbar Urethral Fistula of Anorectal
Vikesh Agrawal1, Saurabh Gupta2, Nguyễn Thanh Liêm3
1Department of Surgery, Division of Pediatric Surgery, Netaji Subhash Chandra Bose Government Medical College, Jabalpur, Madhya Pradesh, India.

Introduction:
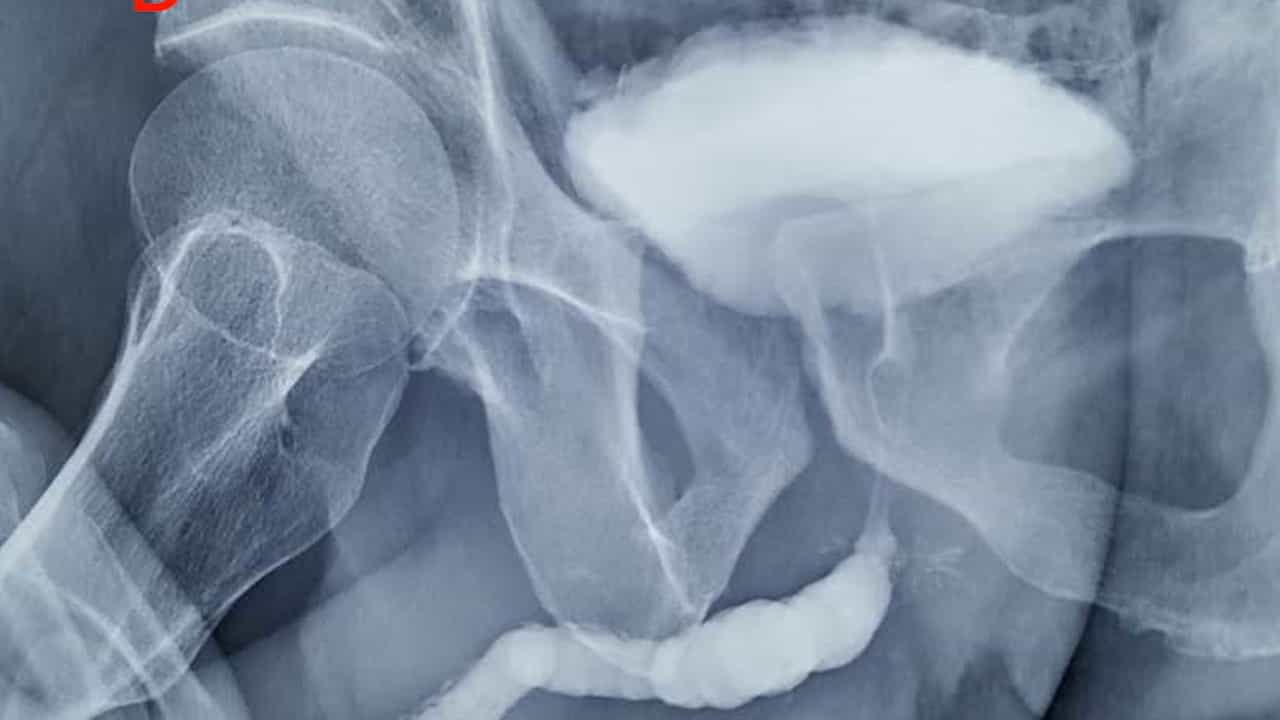
Laparoscopic anorectoplasty (LAARP) is useful for the management of rectoprostatic urethral fistula (RPUF), due to easier rectal mobilization, avoidance of posterior sagittal muscular incision, and shorter hospital stay. However, its role in rectobulbar urethral fistula (RBUF) is still debated as there is a chance of urethral diverticulum (UD), due to incomplete dissection. Laparoscopy-assisted modified posterior sagittal anorectoplasty (LAMPSARP) utilizes advantages of LAARP combined with fistula dissection using small sagittal incision preserving puborectalis. The present study compares the results of LAMPSARP with LAARP for correction of RBUF associated with anorectal malformations (ARMs).
Materials And Methods:
All male ARM with RBUF presenting in a tertiary center in Central India (January 2014-January 2016) were included. Low male ARM, RPUF, rectovesical fistula, and congenital pouch colon were excluded. They were randomized into LAARP and LAMPSARP groups. Complications were assessed in terms of anal stenosis, mucosal prolapse, and UD. Kelly's scoring and Krickenbeck scoring were used to assess continence, and visible anal cosmesis scale (VACS) was used to assess wanal cosmesis. Results were statistically analyzed using a comparison of means and 2 × 2 contingency tables.
Results:
Fifty-six colostomized patients with RBUF (26 LAARP, 30 LAMPSARP) were included. Mean operative duration in the LAARP group and LAMPSARP group was 42 ± 10 min and 56 ± 12 min, respectively (P < 0.0001). On mean follow-up of 4.5 years, mucosal prolapse (53.9%) and UD (15.38%) were significantly higher in LAARP group, while anal stenosis was similar. All three, Kelly's score, Krickenbeck score, and VACS, were better (P < 0.05) in the LAMPSARP group.
Conclusion:
Laparoscopy-assisted modified posterior sagittal approach is better for RBUF and offers better surgical outcome.
More Related Videos
 03:55
Urethroplasty with Pedicled Tunica Vaginalis for the Treatment of Long-segment Anterior Urethral Stricture Caused by Lichen Sclerosus of Glans Penis
Published on: October 18, 2024
 05:09
Urethral Stricture Induction Followed by Buccal Mucosa Graft Urethroplasty in a Rat Model
Published on: April 28, 2023
