Adaptive Support Ventilation and Lung-Protective Ventilation in ARDS
Related Experiment Video
Updated: Sep 1, 2025
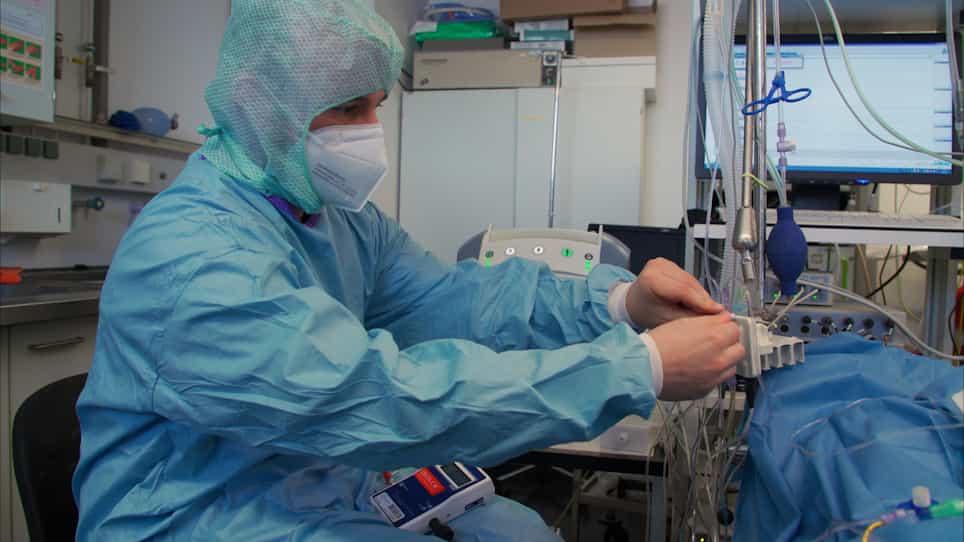
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
Elias N Baedorf Kassis1, Andres Brenes Bastos2, Maximillian S Schaefer3
1Division of Pulmonary, Critical Care and Sleep Medicine, Beth Israel Deaconess Medical Center, Harvard Medical School, Boston, Massachusetts; and Department of Anesthesia, Critical Care and Pain Medicine, Beth Israel Deaconess Medical Center, Harvard Medical School, Boston, Massachusetts. enbaedor@bidmc.harvard.edu.

Background:
Adaptive support ventilation (ASV) is a partially closed-loop ventilation mode that adjusts tidal volume (VT) and breathing frequency (f) to minimize mechanical work and driving pressure. ASV is routinely used but has not been widely studied in ARDS.
Methods:
The study was a crossover study with randomization to intervention comparing a pressure-regulated, volume-targeted ventilation mode (adaptive pressure ventilation [APV], standard of care at Beth Israel Deaconess Medical Center) set to VT 6 mL/kg in comparison with ASV mode where VT adjustment is automated. Subjects received standard of care (APV) or ASV and then crossed over to the alternate mode, maintaining consistent minute ventilation with 1-2 h in each mode. The primary outcome was VT corrected for ideal body weight (IBW) before and after crossover. Secondary outcomes included driving pressure, mechanics, gas exchange, mechanical power, and other parameters measured after crossover and longitudinally.
Results:
Twenty subjects with ARDS were consented, with 17 randomized and completing the study (median PaO /FIO 146.6 [128.3-204.8] mm Hg) and were mostly passive without spontaneous breathing. ASV mode produced marginally larger VT corrected for IBW (6.3 [5.9-7.0] mL/kg IBW vs 6.04 [6.0-6.1] mL/kg IBW, P = .035). Frequency was lower with patients in ASV mode (25 [22-26] breaths/min vs 27 [22-30)] breaths/min, P = .01). In ASV, lower respiratory-system compliance correlated with smaller delivered VT/IBW (R2 = 0.4936, P = .002). Plateau (24.7 [22.6-27.6] cm H2O vs 25.3 [23.5-26.8] cm H2O, P = .14) and driving pressures (12.8 [9.0-15.8] cm H2O vs 11.7 [10.7-15.1] cm H2O, P = .29) were comparable between conventional ventilation and ASV. No adverse events were noted in either ASV or conventional group related to mode of ventilation.
Conclusions:
ASV targeted similar settings as standard of care consistent with lung-protective ventilation strategies in mostly passive subjects with ARDS. ASV delivered VT based upon respiratory mechanics, with lower VT and mechanical power in subjects with stiffer lungs.

Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:14
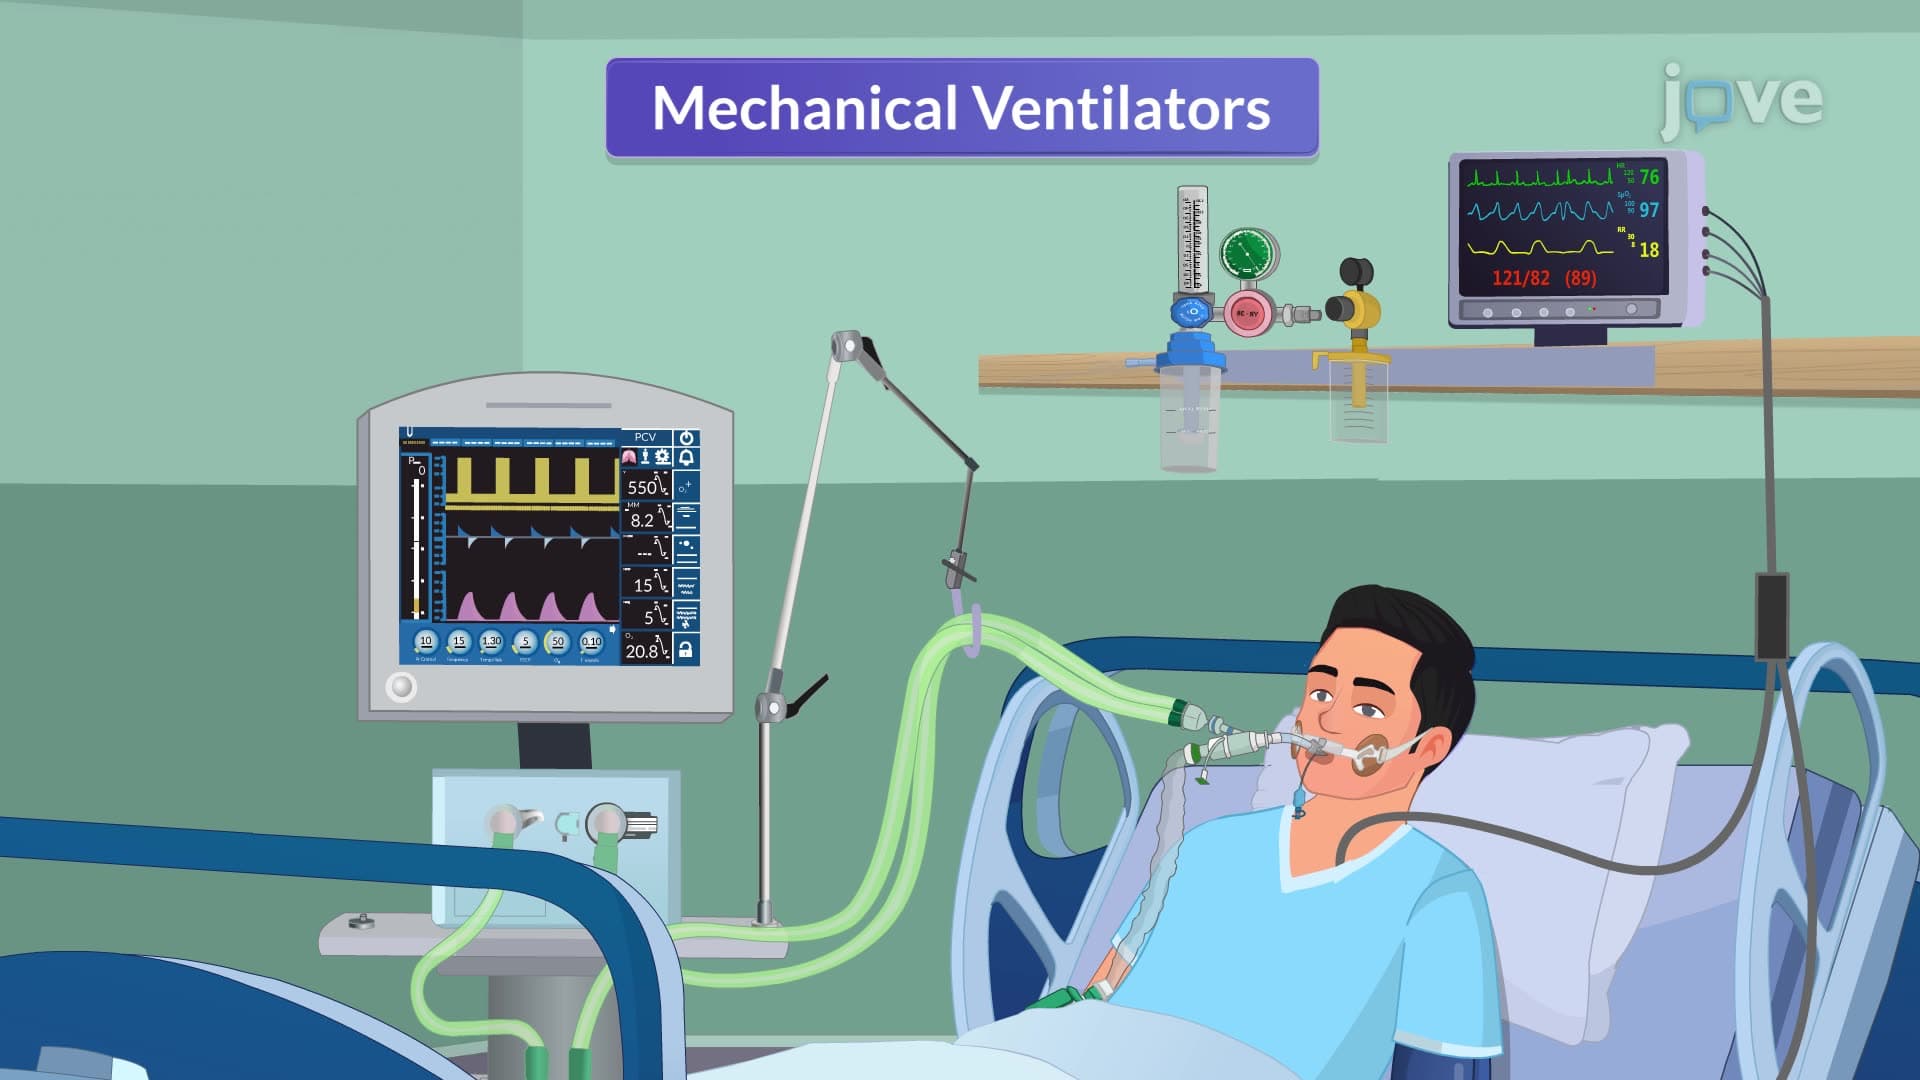
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...