Related Experiment Video
Updated: Aug 31, 2025
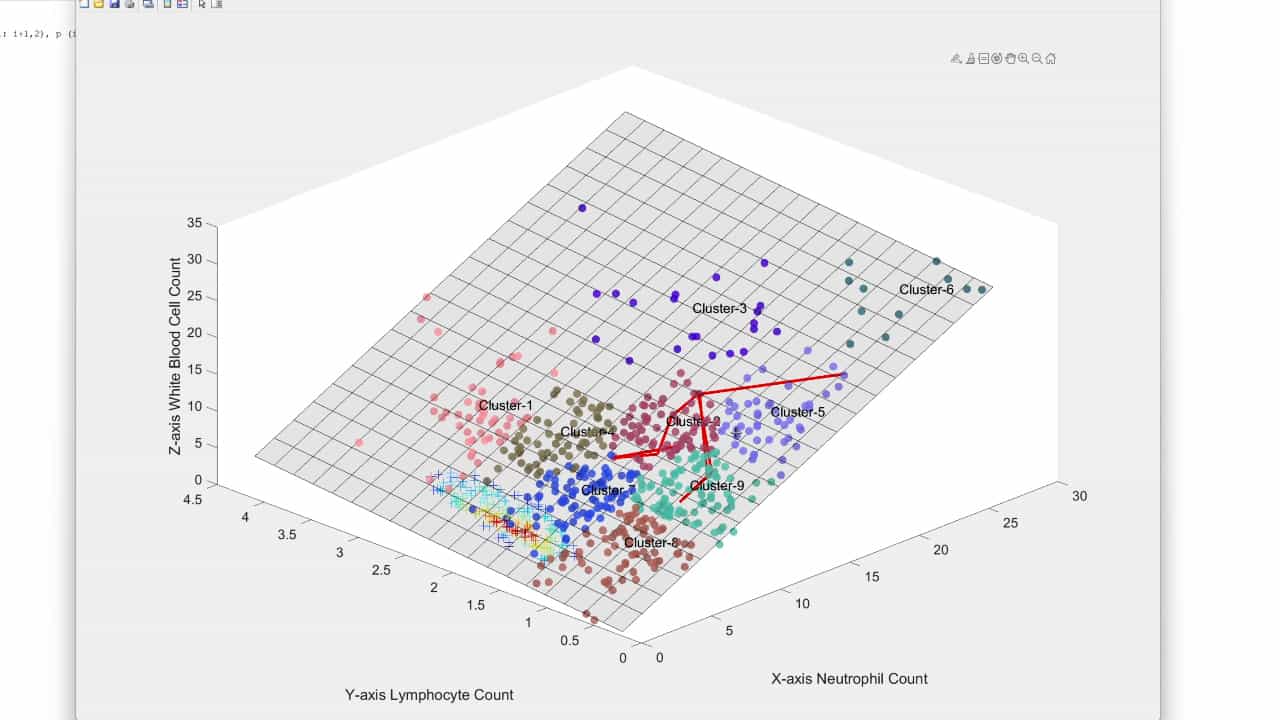

A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
SOFA Score in relation to Sepsis: Clinical Implications in Diagnosis, Treatment, and Prognostic Assessment
Changbo Liu1, Shuzhen Suo1, Liya Luo1
1Department of Critical Medicine, The Fourth Affiliated Hospital of Guangzhou Medical University, Guangzhou, Guangdong, China.

Purpose:
To analyze the clinical significance of the sequential organ failure assessment (SOFA) score in the diagnosis, treatment, and prognostic assessment of sepsis.
Methods:
140 patients with sepsis from January 2020 to January 2021 were selected as the observation group, and 40 healthy people were selected as the control group. The observation group was divided into mild group, severe group, and septic shock group by single blind grouping according to the condition of the disease, and they were also divided into survival group and death group according to the prognosis. Collect the fasting venous blood of the subjects in each group in the morning, compare the levels of total bilirubin (TBIL), blood creatinine (CR), and platelet count (PLT) in each group, and record and compare the patients' respiratory system oxygen partial pressure/inhaled oxygen concentration (po2/fio2), acute physiology and chronic health scoring system II (APACHE II), sequential organ failure assessment (sofa) score, q-SOFA score, and △SOFA score; Pearson analysis was used to analyze the correlation between SOFA score and other indicators; multivariate logistic regression was used to analyze the prognostic risk factors of patients with sepsis; receiver-operating characteristic curve (ROC) was used to analyze the value of SOFA score alone and in combination in the diagnosis, condition, and prognosis of sepsis.
Results:
There were significant differences in Apache II score, SOFA score, q-SOFA score map, po2/fio2, PLT, GCS, TBIL, and serum creatinine (SCR) between the control group and the observation group (P < 0.05). There were significant differences in Apache II score, SOFA score, q-SOFA score, mean arterial pressure (map) po2/fio2, PLT, Glasgow Coma Score (GCS), TBIL, SCR, and △SOFA score among patients in mild, severe, and septic shock groups (P < 0.05). There were significant differences in age, Apache II score, SOFA score, q-SOFA score, map, po2/fio2, PLT, GCS, TBIL, SCR, and △SOFA score between survival group and death group (P < 0.05). SOFA score and q-SOFA score were significantly positively correlated with TBIL and SCR and significantly negatively correlated with po2/fio2 and PLT; △SOFA score was significantly negatively correlated with TBIL and SCR and significantly positively correlated with map, po2/fio2, PLT, and GCS. Apache II score, SOFA score, and q-SOFA score were independent risk factors for sepsis patients, and △SOFA score, po2/fio2, and GCS score were protective factors (P < 0.05). ROC curve analysis showed that the AUC of sepsis combined with SOFA score and q-SOFA score was 0.880; the AUC of sepsis assessed by SOFA score, q-SOFA score, and △SOFA score was 0.929; the AUC of sepsis prognosis assessed by SOFA score, q-SOFA score, and △SOFA score was 0.900.
Conclusion:
SOFA score, q-SOFA score, and △SOFA score were abnormally expressed in patients with sepsis and were risk factors for the severity of the patient's condition and prognosis. The SOFA score, q-SOFA score, and △SOFA score were risk factors for the severity and prognosis of patients with sepsis and had some value in diagnosing sepsis and assessing the condition and prognosis, of which the combined value of the three was higher.


Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...