Related Experiment Video
Updated: Jul 28, 2026


Isolation of Peritoneum-derived Mast Cells and Their Functional Characterization with Ca2+-imaging and Degranulation Assays
Published on: July 4, 2018
Acute abdomen due to anaphylactic intestinal edema associated with systematic mastocytosis: a case report
Tomoko Takagishi1, Katsuhiko Miki2, Shinsaku Imashuku3
1Department of Surgery, Ikoma City Hospital, Ikoma, Nara, 630-0213, Japan. tomokobe0502@gmail.com.

Background:
Among various anaphylactic conditions resulting in acute abdomen, mast cell activation disorders, although rare, are included in the differential diagnosis.
Case Presentation:
This report describes a 63-year-old Caucasian man who was brought to the emergency room with sudden onset abdominal pain, vomiting, and diarrhea, with breathing difficulty, and with facial swelling after quarrelling with an acquaintance. Computed tomography showed edematous and swollen intestines, consistent with splenomegaly. Physical findings included maculopapular cutaneous mastocytosis. He also had a long history of repeated episodes of anaphylaxis requiring occasional epinephrine auto-injector administration; however, the precise cause of anaphylaxis was previously undetermined. Blood tests showed high serum concentrations of soluble IL-2R and tryptase, suggesting mast cell-related disease. Subsequent biopsies of his bone marrow and cutaneous rash confirmed the diagnosis of systemic mastocytosis (SM).
Conclusion:
SM was diagnosed in a patient with acute abdomen who visited the emergency room.
More Related Videos
 04:34
Mouse Body Temperature Measurement Using Infrared Thermometer During Passive Systemic Anaphylaxis and Food Allergy Evaluation
Published on: September 14, 2018
 08:25
An Ex vivo Mast Cell Degranulation Assay using Crude Peritoneal Exudate Cells and Natural Antigen Stimulation
Published on: April 27, 2021
Related Concept Videos
 02:06
Allergic Reactions
 01:28
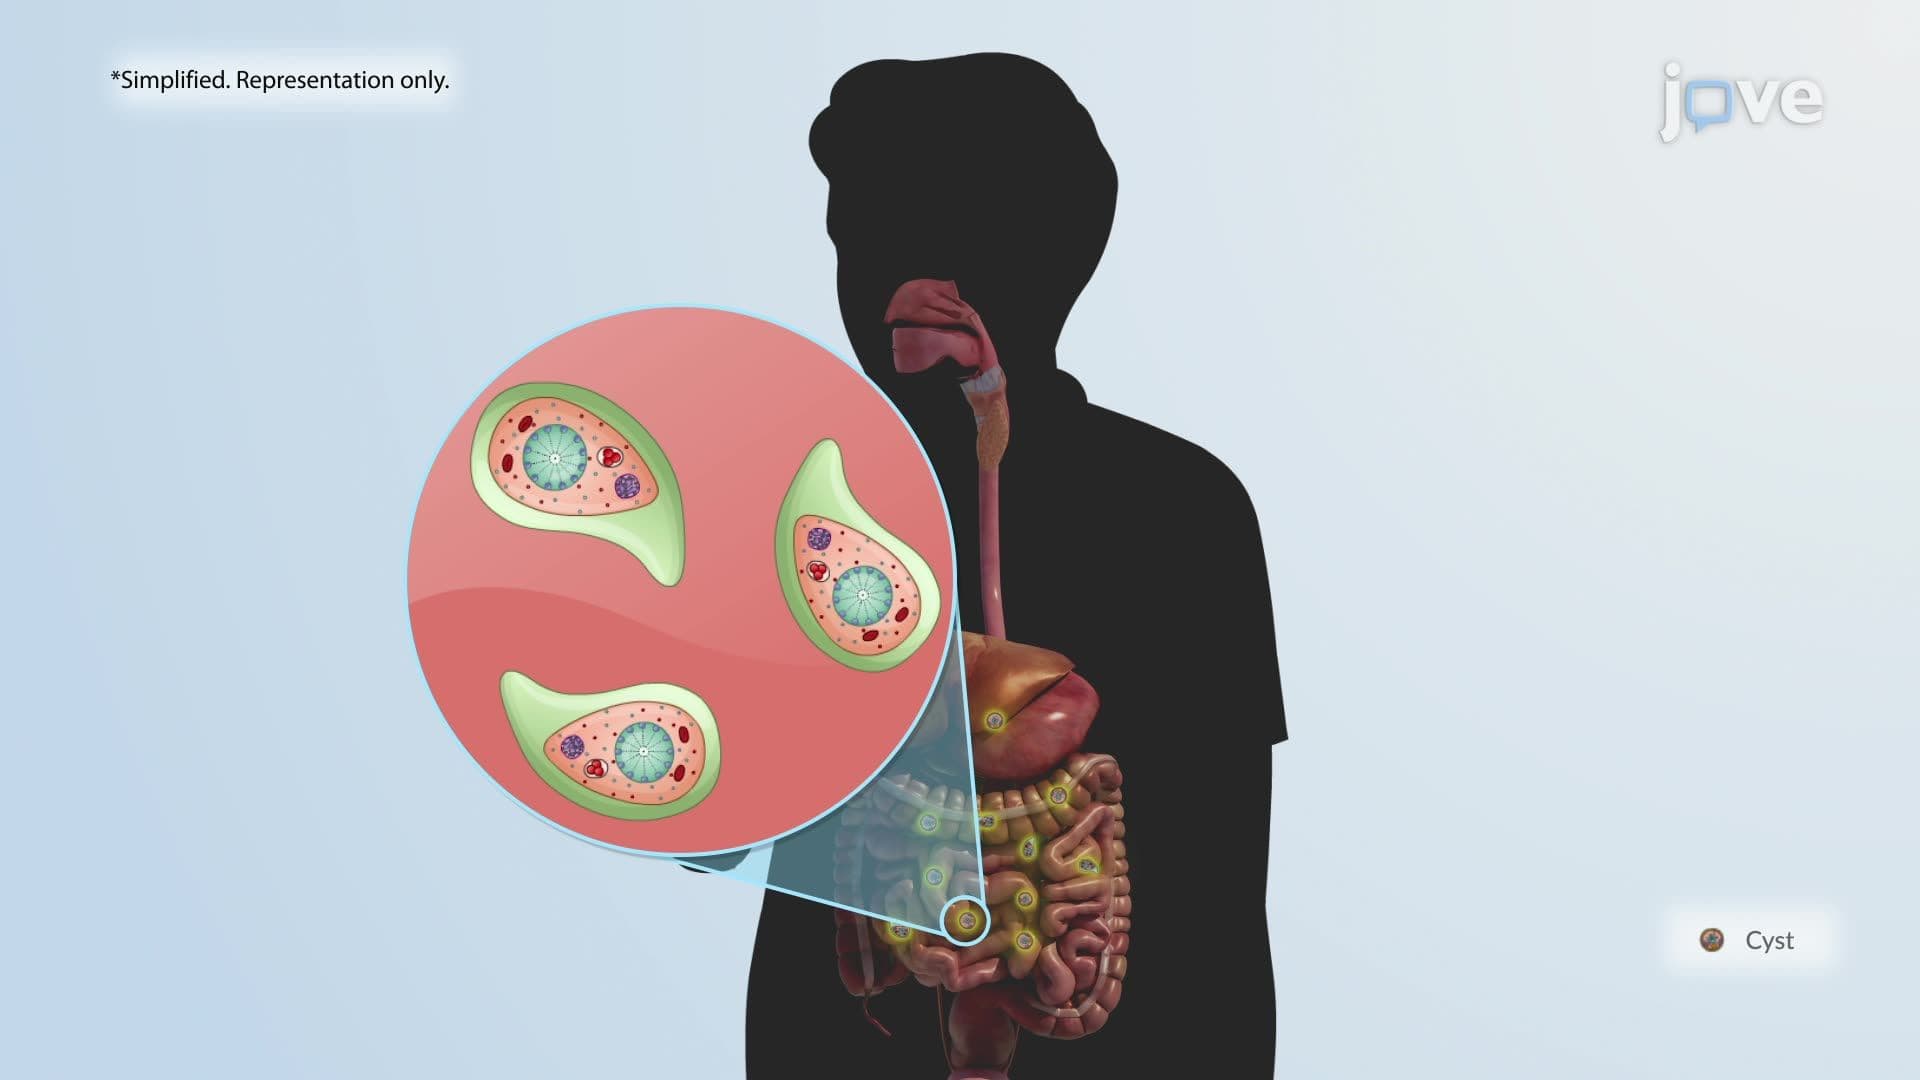
Amebiasis
 01:27
Esophageal Achalasia
 01:07
Intestinal Obstruction II: Pathophysiology
 01:25
Acute Pancreatitis I: Introduction
 01:21
Acute Pancreatitis II: Pathophysiology